Blueprint Medicines — EORTC-NCI-AACR Molecular Targets and Cancer Therapeutics Symposium 2016
17 slides from Blueprint Medicines's conference presentation, Dec 1, 2016

Slide 1: Preliminary safety and activity in a first-in-human Phase 1 study of BLU-285 in advanced GIST
Preliminary safety and activity in a first-in-human Phase 1 study of BLU-285, a potent, highly selective inhibitor of KIT and PDGFR activation loop mutants in advanced gastrointestinal stromal tumor (GIST) Michael Heinrich1, Robin Jones2, Patrick Schoffski3, Sebastian Bauer4, Margaret von Mehren5,

Slide 2: Disclosures
BLU-285 is an investigational agent currently in development by Blueprint Medicines Corporation (Blueprint Medicines) Dr. Michael Heinrich is an investigator for Blueprint Medicines’ ongoing Phase 1 study in unresectable gastrointestinal stromal tumor Dr. Michael Heinrich has the following disclosur
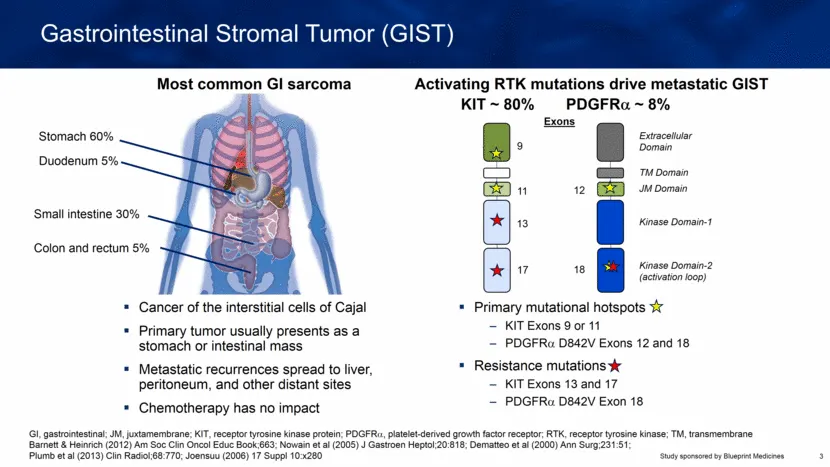
Slide 3: Gastrointestinal Stromal Tumor (GIST): activating RTK mutations drive metastatic GIST
Cancer of the interstitial cells of Cajal Primary tumor usually presents as a stomach or intestinal mass Metastatic recurrences spread to liver, peritoneum, and other distant sites Chemotherapy has no impact Gastrointestinal Stromal Tumor (GIST) Most common GI sarcoma Primary mutational hotspots KIT
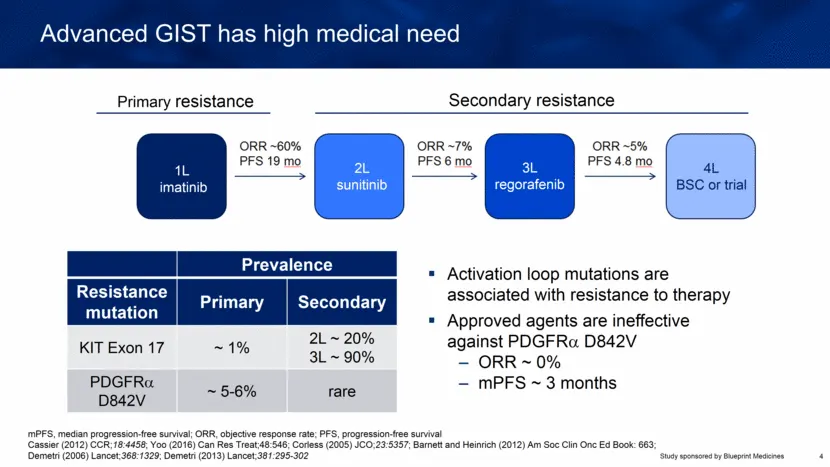
Slide 4: Advanced GIST has high medical need
Advanced GIST has high medical need Activation loop mutations are associated with resistance to therapy Approved agents are ineffective against PDGFR D842V ORR ~ 0% mPFS ~ 3 months Primary resistance Secondary resistance Prevalence Resistance mutation Primary Secondary KIT Exon 17 ~ 1% 2L ~ 20% 3L
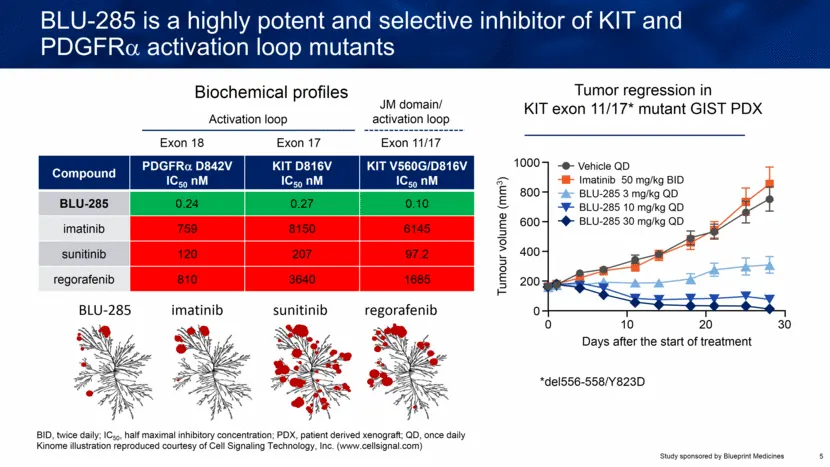
Slide 5: BLU-285 is a highly potent and selective inhibitor of KIT and PDGFR activation loop mutants
BLU-285 imatinib sunitinib regorafenib BLU-285 is a highly potent and selective inhibitor of KIT and PDGFR activation loop mutants Tumor regression in KIT exon 11/17* mutant GIST PDX Biochemical profiles Compound PDGFR D842V IC50 nM KIT D816V IC50 nM KIT V560G/D816V IC50 nM BLU-285 0.24 0.27 0.10
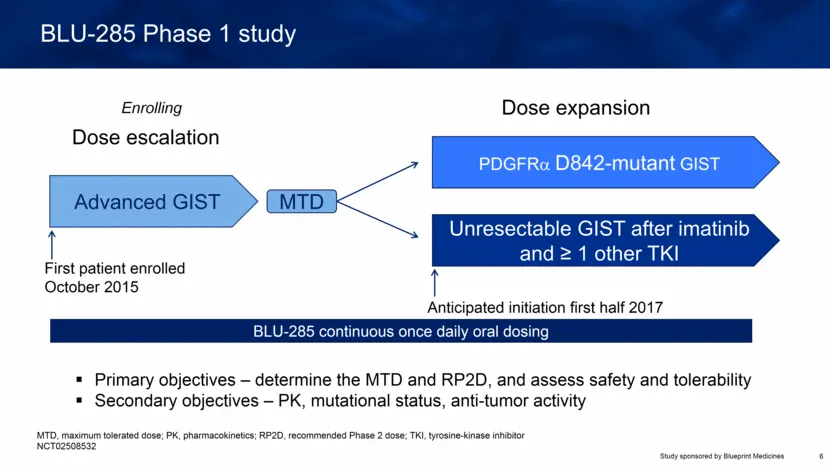
Slide 6: BLU-285 Phase 1 study design
BLU-285 Phase 1 study Advanced GIST MTD Dose expansion Unresectable GIST after imatinib and ≥ 1 other TKI PDGFR D842-mutant GIST BLU-285 continuous once daily oral dosing Dose escalation Primary objectives – determine the MTD and RP2D, and assess safety and tolerability Secondary objectives – PK, m
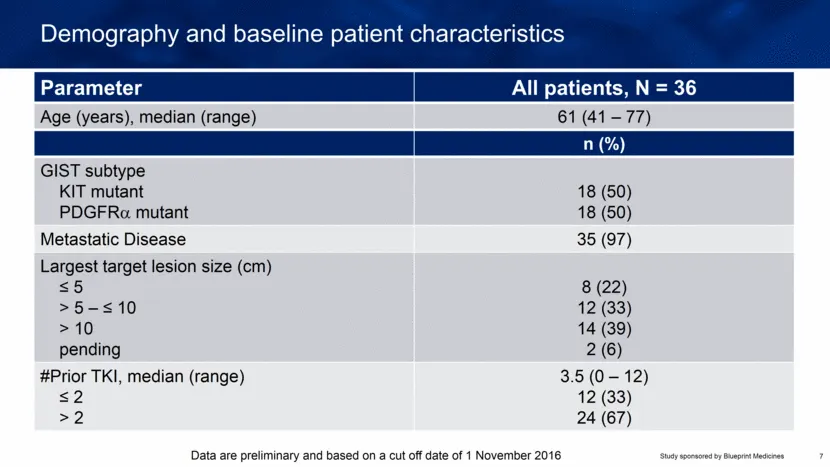
Slide 7: Demography and baseline patient characteristics
Parameter All patients, N = 36 Age (years), median (range) 61 (41 – 77) n (%) GIST subtype KIT mutant PDGFR mutant 18 (50) 18 (50) Metastatic Disease 35 (97) Largest target lesion size (cm) ≤ 5 > 5 – ≤ 10 > 10 pending 8 (22) 12 (33) 14 (39) 2 (6) #Prior TKI, median (range) ≤ 2 > 2 3.5 (0 – 12) 12 (
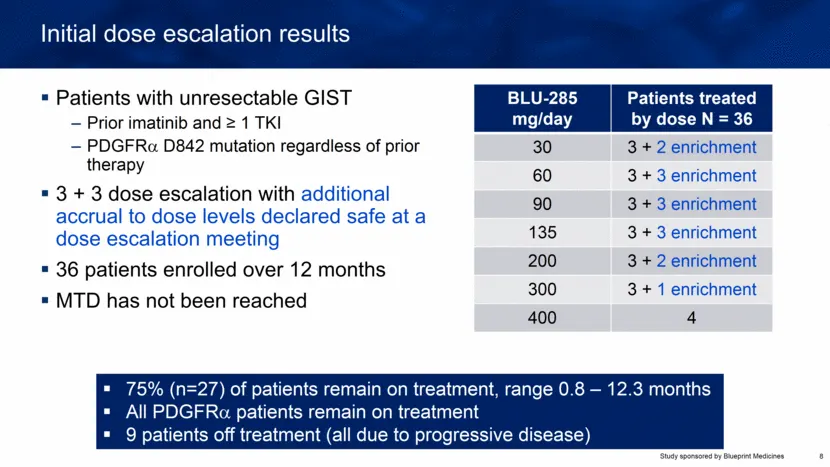
Slide 8: Initial dose escalation results
Patients with unresectable GIST Prior imatinib and ≥ 1 TKI PDGFR D842 mutation regardless of prior therapy 3 + 3 dose escalation with additional accrual to dose levels declared safe at a dose escalation meeting 36 patients enrolled over 12 months MTD has not been reached Initial dose escalation res
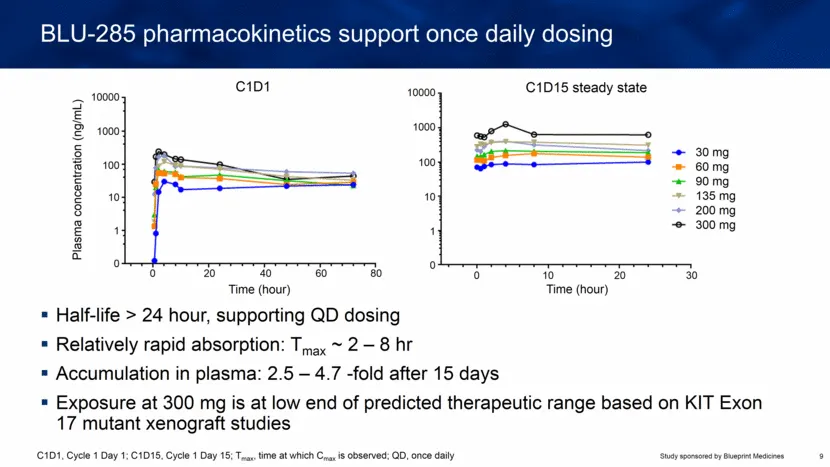
Slide 9: BLU-285 pharmacokinetics support once daily dosing
10000 1000 100 10 1 0 30 mg 60 mg 90 mg 135 mg 200 mg 300 mg Time (hour) 0 10 20 30 10000 1000 100 10 1 0 Plasma concentration (ng/mL) Time (hour) Half-life > 24 hour, supporting QD dosing Relatively rapid absorption: Tmax ~ 2 – 8 hr Accumulation in plasma: 2.5 – 4.7 -fold after 15 days Exposure at
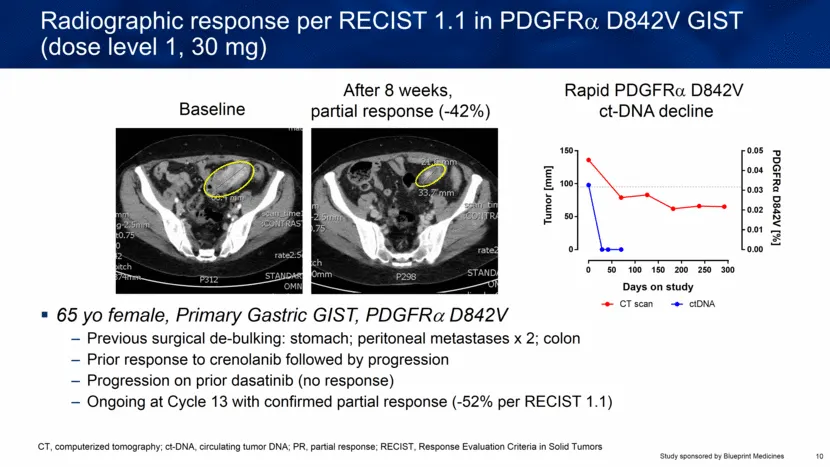
Slide 10: Radiographic response in PDGFR D842V GIST
65 yo female, Primary Gastric GIST, PDGFR D842V Previous surgical de-bulking: stomach; peritoneal metastases x 2; colon Prior response to crenolanib followed by progression Progression on prior dasatinib (no response) Ongoing at Cycle 13 with confirmed partial response (-52% per RECIST 1.1) Radiogr
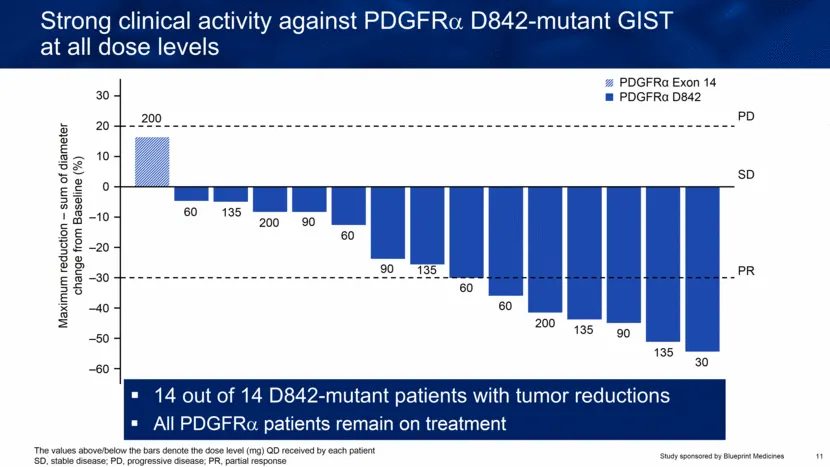
Slide 11: Strong clinical activity against PDGFR D842-mutant GIST at all dose levels
Strong clinical activity against PDGFR D842-mutant GIST at all dose levels Maximum reduction – sum of diameter change from Baseline (%) 30 PDGFRα Exon 14 PDGFRα D842 20 10 0 –10 –20 –30 –40 –50 –60 200 60 60 60 60 135 200 90 90 135 200 135 90 135 30 PR SD PD 14 out of 14 D842-mutant patients with t
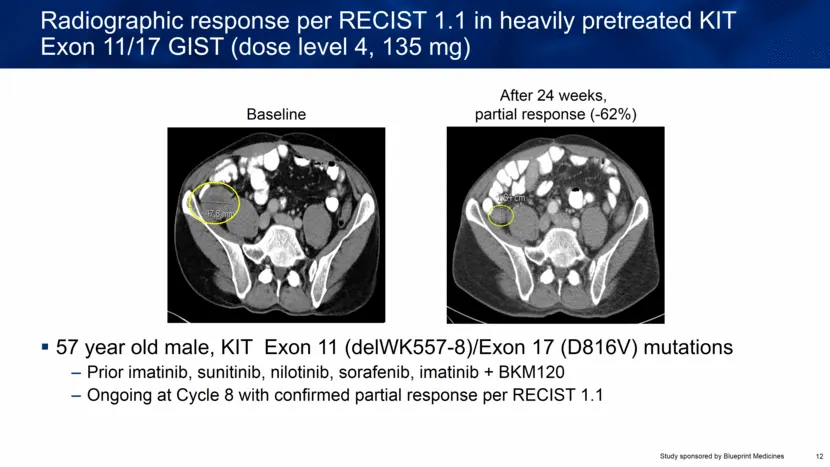
Slide 12: Radiographic response in heavily pretreated KIT Exon 11/17 GIST
57 year old male, KIT Exon 11 (delWK557-8)/Exon 17 (D816V) mutations Prior imatinib, sunitinib, nilotinib, sorafenib, imatinib + BKM120 Ongoing at Cycle 8 with confirmed partial response per RECIST 1.1 Radiographic response per RECIST 1.1 in heavily pretreated KIT Exon 11/17 GIST (dose level 4, 135
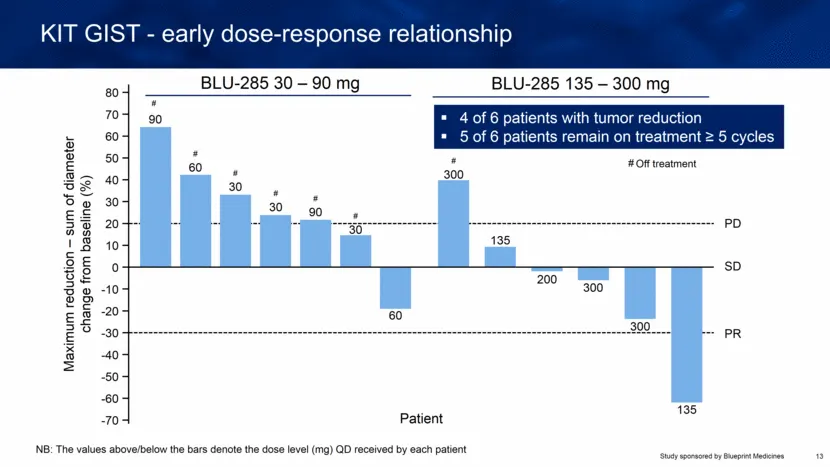
Slide 13: KIT GIST - early dose-response relationship
KIT GIST - early dose-response relationship Maximum reduction – sum of diameter change from baseline (%) 80 70 60 50 40 30 20 10 0 -10 -20 -30 -40 -50 -60 -70 Off treatment # BLU-285 30 – 90 mg BLU-285 135 – 300 mg 90 60 30 30 90 30 60 300 135 200 300 300 135 PD SD PR # # # # # # Patient # NB: The v
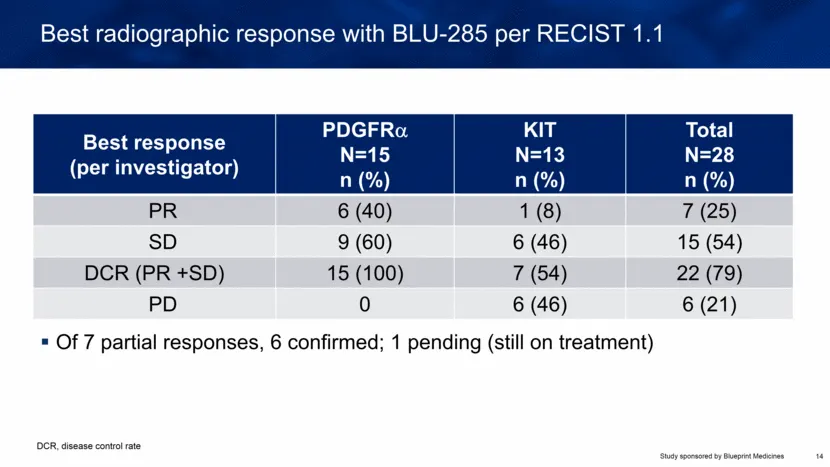
Slide 14: Best radiographic response with BLU-285 per RECIST 1.1
Best radiographic response with BLU-285 per RECIST 1.1 Of 7 partial responses, 6 confirmed; 1 pending (still on treatment) DCR, disease control rate Best response (per investigator) PDGFR N=15 n (%) KIT N=13 n (%) Total N=28 n (%) PR 6 (40) 1 (8) 7 (25) SD 9 (60) 6 (46) 15 (54) DCR (PR +SD) 15 (100
Slide 15: Adverse events associated with BLU-285
No DLTs or treatment-related Grade 4 – 5 AEs No patient discontinued BLU-285 due to treatment-related toxicity 11 (31%) patients had Grade 3 or higher AEs; of these, 3 were considered treatment-related: 1 patient with Grade 3 nausea and vomiting 1 patient with Grade 3 anemia and intratumoral hemorrh

Slide 16: Summary
BLU-285 has been well tolerated on a QD schedule at doses of 30 – 400 mg Half-life > 24 hours, supports QD dosing BLU-285 demonstrates strong clinical activity in PDGFR D842-mutant GIST at all dose levels Significant anti-tumor activity in TKI-resistant, KIT-mutant GIST observed at doses ≥ 135 mg w

Slide 17: Acknowledgments
We thank the participating patients, their families, all study co-investigators, and research coordinators at the following institutions: Oregon Health & Sciences University Royal Marsden Hospital/Institute for Cancer Research Leuven Cancer Institute University of Essen Fox Chase Cancer Center Erasm
Source: SEC EDGAR · 8-K filed Dec 1, 2016
More decks from Blueprint Medicines Corp
 Q1 2025 Earnings Presentation14 slides · May 1, 2025
 Q4 2024 Earnings Presentation12 slides · Feb 13, 2025
 J.P. Morgan Healthcare Conference 202525 slides · Jan 13, 2025
 Technical Presentation (April 2024)19 slides · Apr 25, 2024
 J.P. Morgan Healthcare Conference 202425 slides · Jan 8, 2024
 AAAAI 2023 Annual Meeting35 slides · Feb 27, 2023