Cidara Therapeutics — Investor Day (April 2017)
174 slides from Cidara Therapeutics's investor day presentation, Apr 6, 2017

Slide 1: New Hope for Serious Infections Analyst Day
New Hope for Serious Infections Analyst Day April 6, 2017

Slide 2: Forward-Looking Statements
2 Forward-Looking Statements These slides and the accompanying oral presentation (the “Presentation”) contain forward-looking statements within the meaning of the Private Securities Litigation Reform Act of 1995. Because such statements are subject to risks and uncertainties, actual results may diff
Slide 3: Cidara's Platform Technologies
3 Cidara’s Platform Technologies Prophylaxis Candidemia/Invasive Candidiasis CD101 IV Echinocandin Antifungal Development Fungal pathogens MDR Gram-negative bacteria V o lk e r B rinkman n , W ik im e d ia .o rg Cloudbreak™ Immunotherapy Preclinical/Discovery

Slide 4: Agenda
4 Agenda Unmet need for new and effective antifungal therapies CD101 IV Efficacy, tissue penetration and safety PK properties of CD101 IV “Shape Matters” STRIVE update (Study design, expected timing) Unmet need for new antifungal prophylaxis Market opportunity for CD101 IV CD101 Update Q&A MDR Patho

Slide 5: Speaker Introductions
Speaker Introductions TTT

Slide 6: Andrew Shorr, M.D.
6 Professor & Critical Care Physician, Georgetown University What is lacking in current antifungal treatment options for my patients? Andrew Shorr, M.D.

Slide 7: David Perlin, Ph.D.
7 Executive Director & Professor, Public Health Research Institute Rutgers University Is CD101 poised to become a best- in-class echinocandin? David Perlin, Ph.D.

Slide 8: Paul Ambrose, Pharm.D.
8 President, Institute of Clinical Pharmacodynamics Will the PK/PD of CD101 predict its differentiation and “success”? Paul Ambrose, Pharm.D.

Slide 9: Kieren Marr, M.D.
9 Professor of Medicine & Oncology, Johns Hopkins Medical School As medical paradigms are shifting in immunocompromised patients, could CD101 be the over-arching antifungal prophylaxis treatment of the future? Kieren Marr, M.D.

Slide 10: Neil Clancy, M.D.
10 Chief of Infectious Diseases VA Pittsburgh Healthcare System Is there a need for new approaches to treat resistant Gram-negative bacterial pathogens? Neil Clancy, M.D.

Slide 11: Introducing Dr. Andy Shorr
11 Introducing Dr. Andy Shorr Andrew F. Shorr, MD, MPH, FCCP, FACP Washington Hospital Center Professor, Georgetown University, Washington, DC

Slide 12: Candida: A Growing Issue in Hospitalized Patients
Candida: A Growing Issue in Hospitalized Patients
Slide 13: Case Study: Candidiasis?
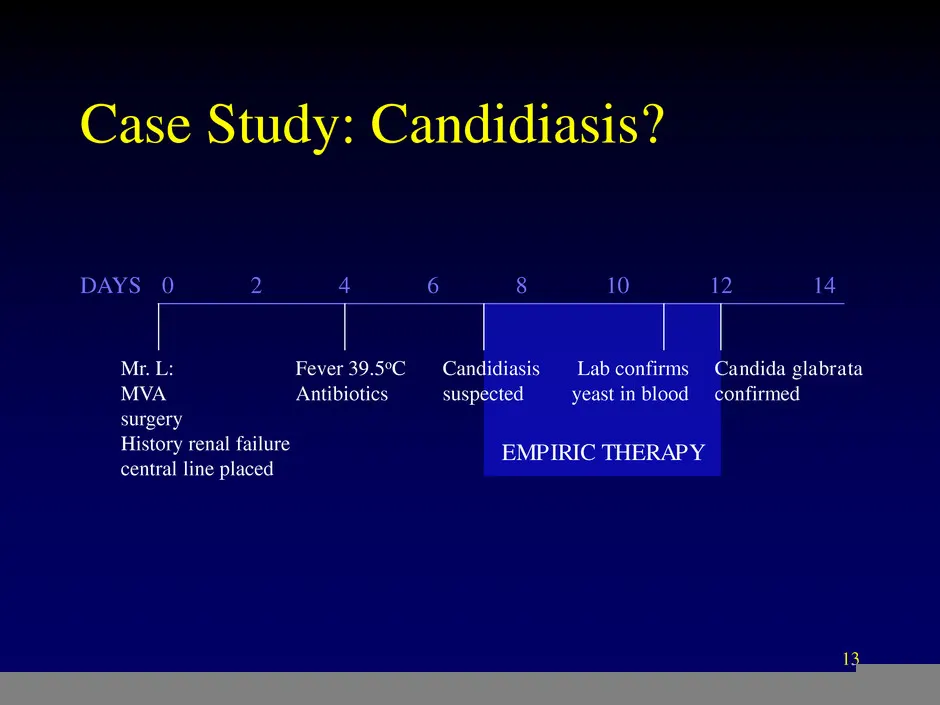
Case Study: Candidiasis? Mr. L: MVA surgery History renal failure central line placed DAYS 0 4 6 8 10 14122 Fever 39.5oC Antibiotics Candidiasis suspected Lab confirms yeast in blood Candida glabrata confirmed EMPIRIC THERAPY 13

Slide 14: What worries me about this patient?
What worries me about this patient? 14
Slide 15: Candidiasis: most common IFI
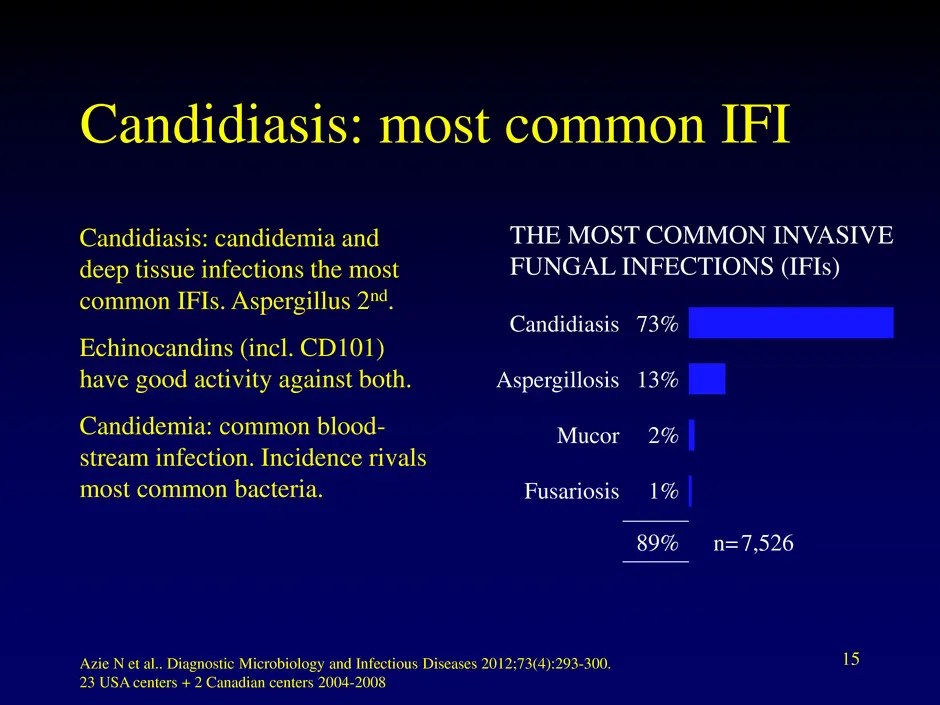
Candidiasis: most common IFI 13% 73% 2% 1% Aspergillosis Candidiasis Mucor Fusariosis 89% n=7,526 Azie N et al.. Diagnostic Microbiology and Infectious Diseases 2012;73(4):293-300. 23 USA centers + 2 Canadian centers 2004-2008 Candidiasis: candidemia and deep tissue infections the most common IFIs.

Slide 16: Candida Causes the Majority of Deaths due to IFIs
Candida Causes the Majority of Deaths due to IFIs 2,500 4,500 22,500 67,500 Rare fungi Cryptococcus Aspergillus Candida U.S. 12-Week Mortality per Annum by Species 16

Slide 17: Mortality Rates are High
Mortality Rates are High Kullberg and Arendrup, NEJM, 2015 Invasive Candidiasis Candidemia • Crude mortality 40-60% • Attributable mortality ~10-15% • 50% severe sepsis • Hospital mortality 2x higher than mortality for other bloodstream infections 17

Slide 18: Rising resistance to azoles
Rising resistance to azoles • Mostly due to non-albicans Candida species • C. krusei is always resistant to fluconazole • C. glabrata most common non-albicans species (US & EU)- & the main species developing resistance. • IDSA recommends to avoid azole therapy for C. glabrata and C. krusei 18

Slide 19: Non-albicans infections rising
Non-albicans infections rising • Non-albicans Candida species are now more than 50% of the infecting strains • Up to 76% if history of azole prophylaxis 19
Slide 20: Mortality Varies By Species
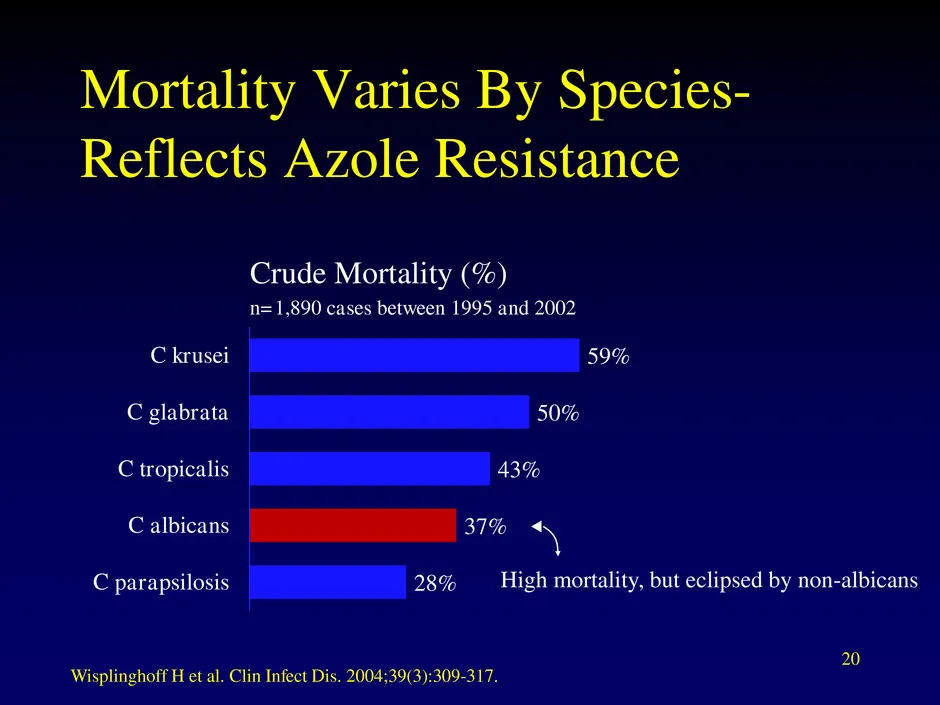
Wisplinghoff H et al. Clin Infect Dis. 2004;39(3):309-317. Mortality Varies By Species- Reflects Azole Resistance 28% 37% 43% 50% 59% C parapsilosis C albicans C tropicalis C glabrata C krusei Crude Mortality (%) n=1,890 cases between 1995 and 2002 High mortality, but eclipsed by non-albicans 20

Slide 21: Candida auris is an Emerging Serious Public Health Threat
Candida auris is an Emerging Serious Public Health Threat • Mortality approaches 70% in candidemia patients • Almost all resistant to azole and 40% resistant to polyenes (Ampho B) • 5-10% resistant to marketed echinocandins Clancy and Nguyen. CID, 2017. 21

Slide 22: Need for Prompt Appropriate Therapy for All Candida spp
Need for Prompt Appropriate Therapy for All Candida spp • Odds of mortality increases >30x if the incorrect drug is used or treatment delayed by ≥24 hours • All-cause mortality by treatment: – Echinocandins = ~30% – No or delayed treatment = 60-100% • Inadequate therapy leads to increased costs and

Slide 23: What are my treatment options?
What are my treatment options? 23

Slide 24: The challenge of empiric and directed therapy
The challenge of empiric and directed therapy DAYS 0 4 6 8 10 14122 Candidiasis suspected Lab confirms yeast in blood EMPIRIC THERAPY DIRECTED THERAPY Candida glabrata confirmed 24

Slide 25: Echinocandins are First Line Therapy for IC
IDSA/ESCMID: Echinocandins are First Line Therapy for IC • Echinocandins demonstrated superior to azoles in candidemia and most forms of IC – High incidence of non-albicans Candida is a driver for the superiority of echinocandins but echinocandins also superior in treating azole-susceptible C. albic

Slide 26: Echinocandins Could Be Improved
Echinocandins Could Be Improved • To safely target less susceptible Candida species either empirically or as directed therapy once identified • Once daily, IV-only therapy can lead to increased hospital lengths-of-stay, costs, and complications 26

Slide 27: Once Daily IV Echinocandins Complicates Outpatient Therapy
Once Daily IV Echinocandins Complicates Outpatient Therapy • Echinocandins in outpatient setting requires once daily IV administration and PICC line placement • Alternative in azole-susceptible cases is for step- down to inferior oral fluconazole therapy – Increased therapy noncompliance and risk fo

Slide 28: What would improve my options?
What would improve my options? 28

Slide 29: A Better Echinocandin
A Better Echinocandin • Optimized PK/PD The safety profile of the echinocandin class that persists through higher exposures administered to overcome increasing rates of Candida resistance and improve outcomes. • Convenient Outpatient Dosing Dosing of first-line therapy available in the outpatient se

Slide 30: With a better echinocandin…
With a better echinocandin… Mr. L: MVA surgery History renal failure central line placed DAYS 0 4 6 8 10 14122 Fever 39.5oC Antibiotics Candidiasis suspected Lab confirms yeast in blood EMPIRIC Starting a ‘better echinocandin’ empiricially Candida glabrata confirmed DOCUMENTED OR Starting a ‘better

Slide 31: Introducing Dr. David Perlin
31 Introducing Dr. David Perlin David S. Perlin, Ph.D. Executive Director and Professor, Public Health Research Institute, Rutgers Biomedical and Health Sciences Newark, New Jersey, USA

Slide 32: CD101: a next generation echinocandin
32 CD101: a next generation echinocandin

Slide 33: CD101 is a next generation echinocandin
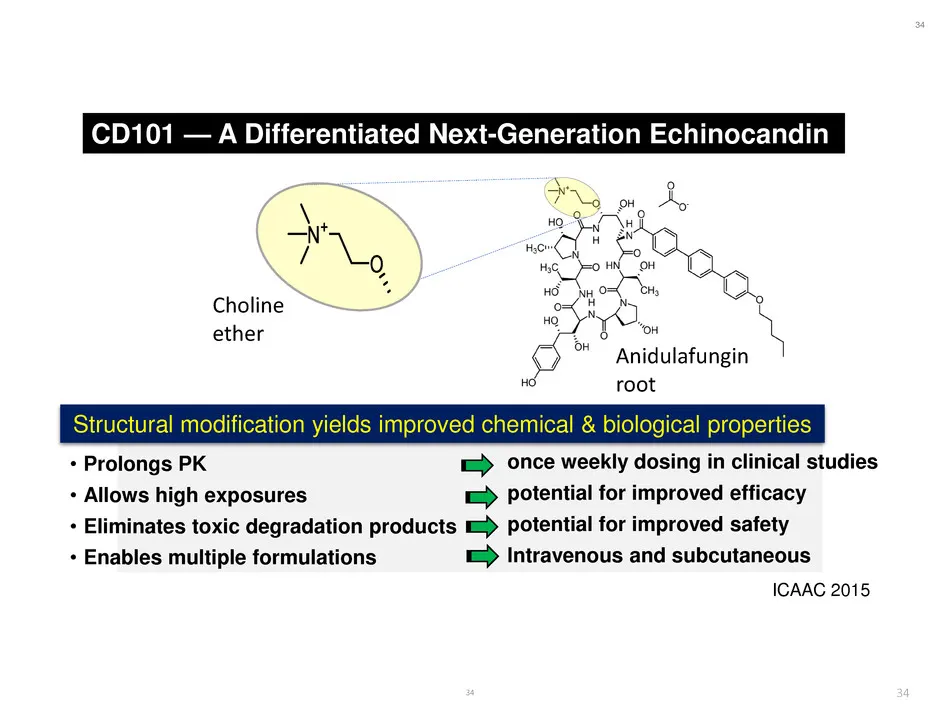
33 CD101 is a next generation echinocandin It has unique chemical properties that promote preclinical safety & efficacy, and position it as a potential best-in-class echinocandin
Slide 34: CD101: Differentiated Next-Generation Echinocandin
3434 ICAAC 2015 • Prolongs PK • Allows high exposures • Eliminates toxic degradation products • Enables multiple formulations once weekly dosing in clinical studies potential for improved efficacy potential for improved safety Intravenous and subcutaneous CD101 — A Differentiated Next-Generation Ech
Slide 35: CD101: Prolonged half-life and stability
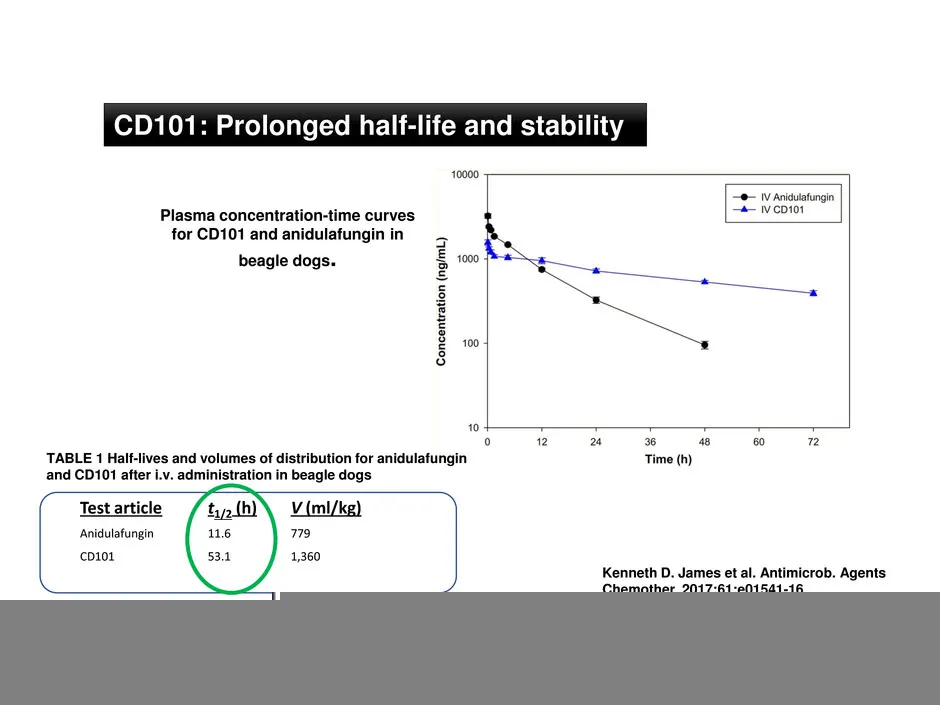
35 Plasma concentration-time curves for CD101 and anidulafungin in beagle dogs. TABLE 1 Half-lives and volumes of distribution for anidulafungin and CD101 after i.v. administration in beagle dogs Test article t1/2 (h) V (ml/kg) Anidulafungin 11.6 779 CD101 53.1 1,360 Kenneth D. James et al. Antimicr
Slide 36: CD101 In Vitro Activity vs Candida and Aspergillus
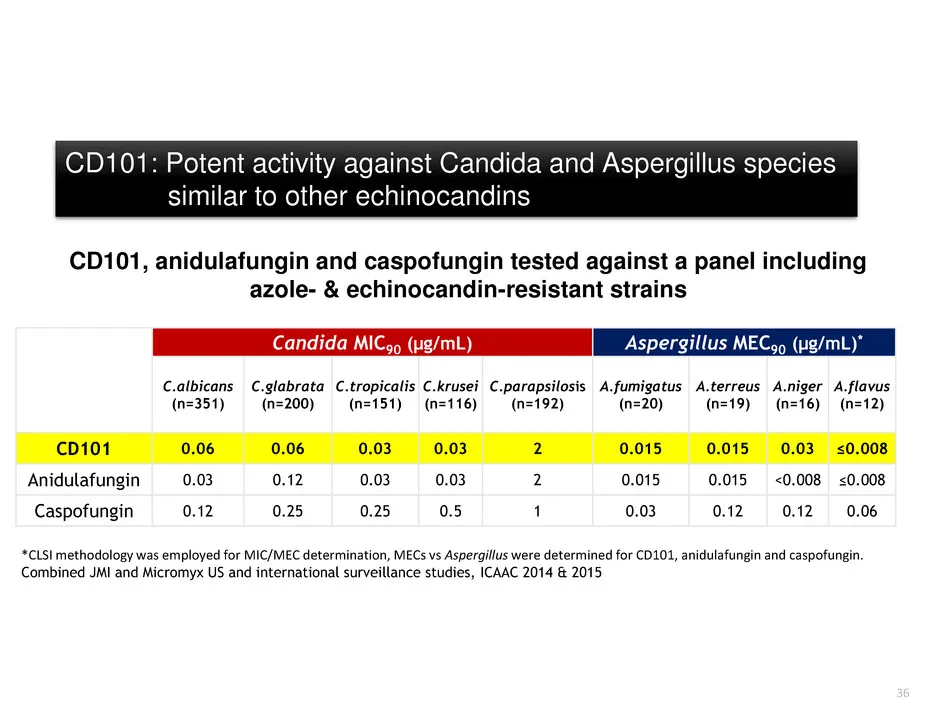
36 Candida MIC90 (µg/mL) Aspergillus MEC90 (µg/mL) * C.albicans (n=351) C.glabrata (n=200) C.tropicalis (n=151) C.krusei (n=116) C.parapsilosis (n=192) A.fumigatus (n=20) A.terreus (n=19) A.niger (n=16) A.flavus (n=12) CD101 0.06 0.06 0.03 0.03 2 0.015 0.015 0.03 ≤0.008 Anidulafungin 0.03 0.12 0.03
Slide 37: CD101 IV: Safe in GLP Toxicology Studies
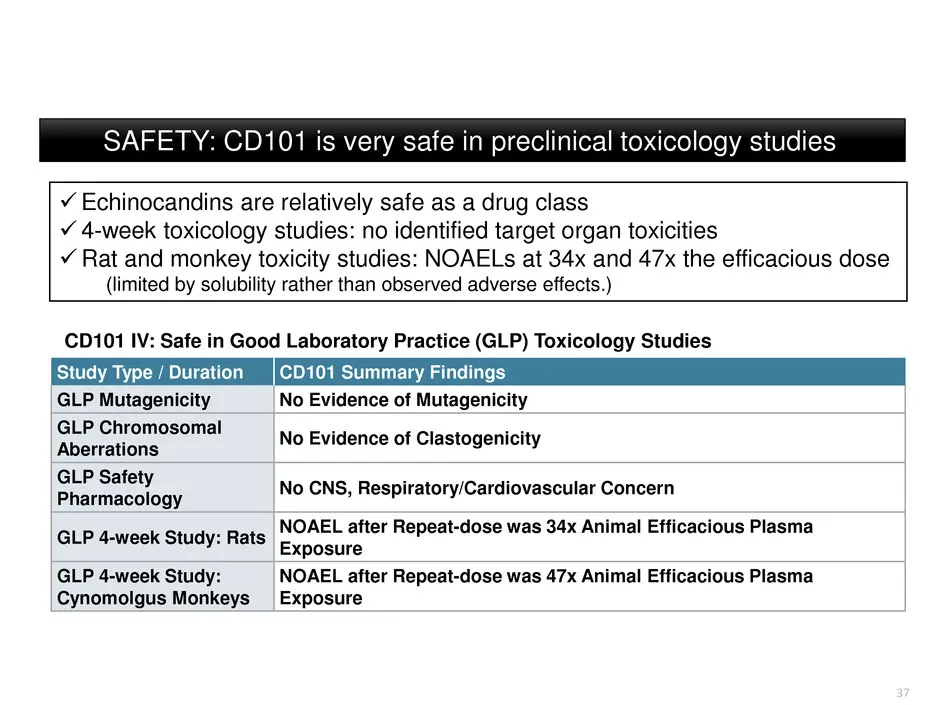
37 Study Type / Duration CD101 Summary Findings GLP Mutagenicity No Evidence of Mutagenicity GLP Chromosomal Aberrations No Evidence of Clastogenicity GLP Safety Pharmacology No CNS, Respiratory/Cardiovascular Concern GLP 4-week Study: Rats NOAEL after Repeat-dose was 34x Animal Efficacious Plasma E
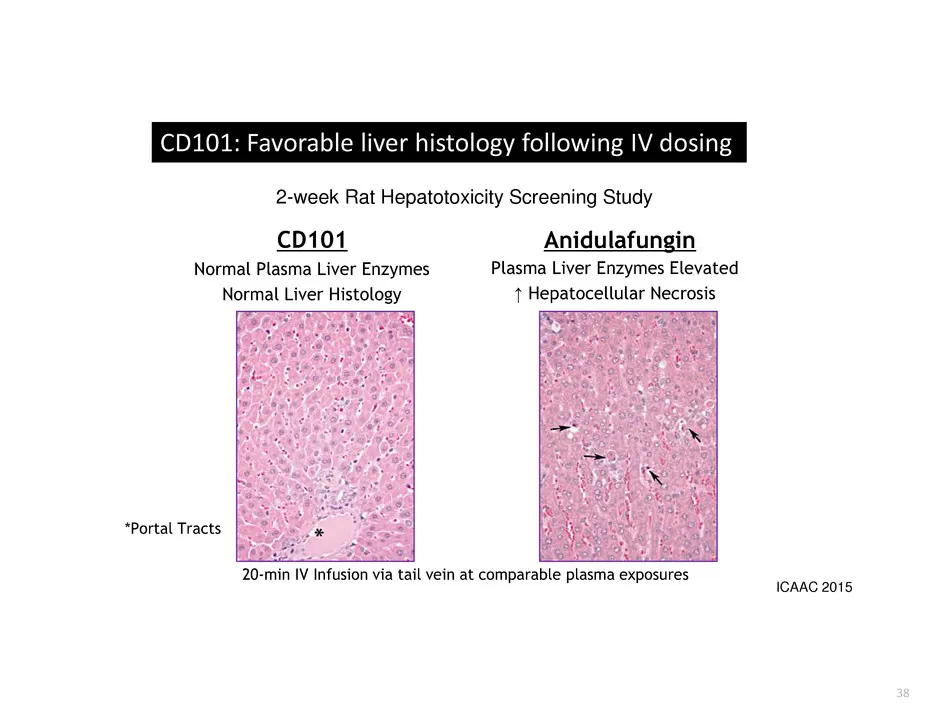
Slide 38: CD101: Favorable liver histology following IV dosing
38 Plasma Liver Enzymes Elevated ↑ Hepatocellular Necrosis Normal Plasma Liver Enzymes Normal Liver Histology AnidulafunginCD101 *Portal Tracts 20-min IV Infusion via tail vein at comparable plasma exposures 2-week Rat Hepatotoxicity Screening Study ICAAC 2015 CD101: Favorable liver histology follow
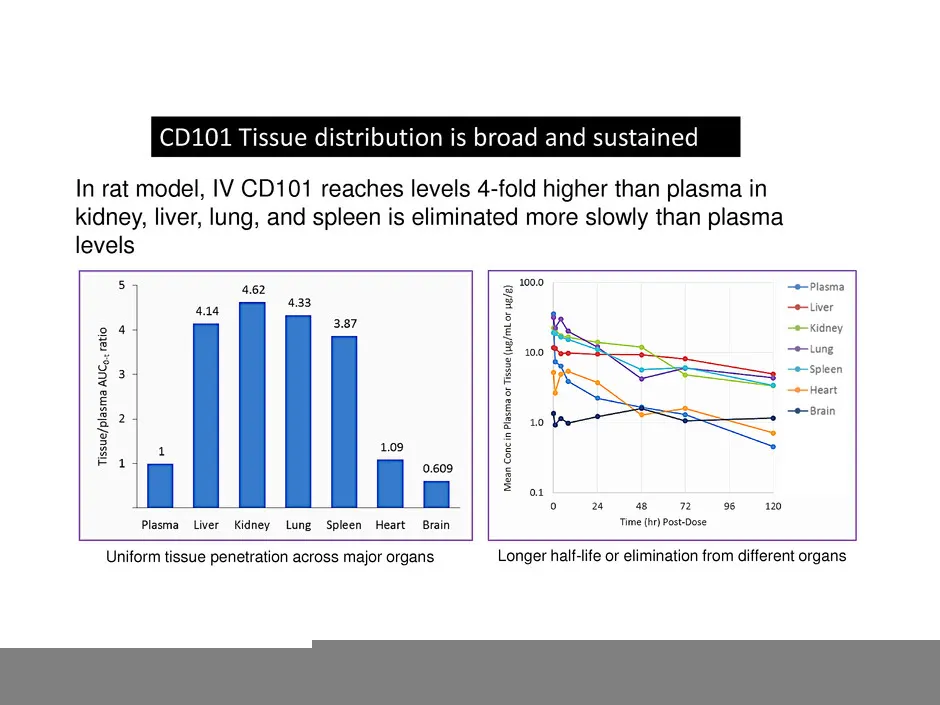
Slide 39: CD101 tissue distribution is broad and sustained
39 Uniform tissue penetration across major organs Longer half-life or elimination from different organs CD101 Tissue distribution is broad and sustained In rat model, IV CD101 reaches levels 4-fold higher than plasma in kidney, liver, lung, and spleen is eliminated more slowly than plasma levels
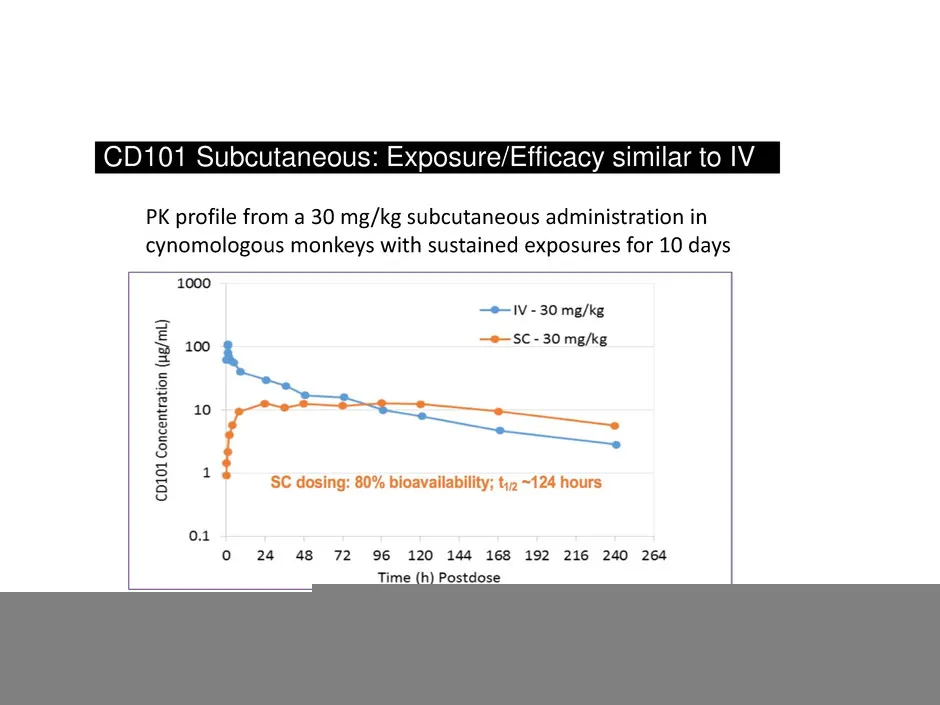
Slide 40: CD101 Subcutaneous: Exposure/Efficacy similar to IV
40 CD101 Subcutaneous: Exposure/Efficacy similar to IV PK profile from a 30 mg/kg subcutaneous administration in cynomologous monkeys with sustained exposures for 10 days
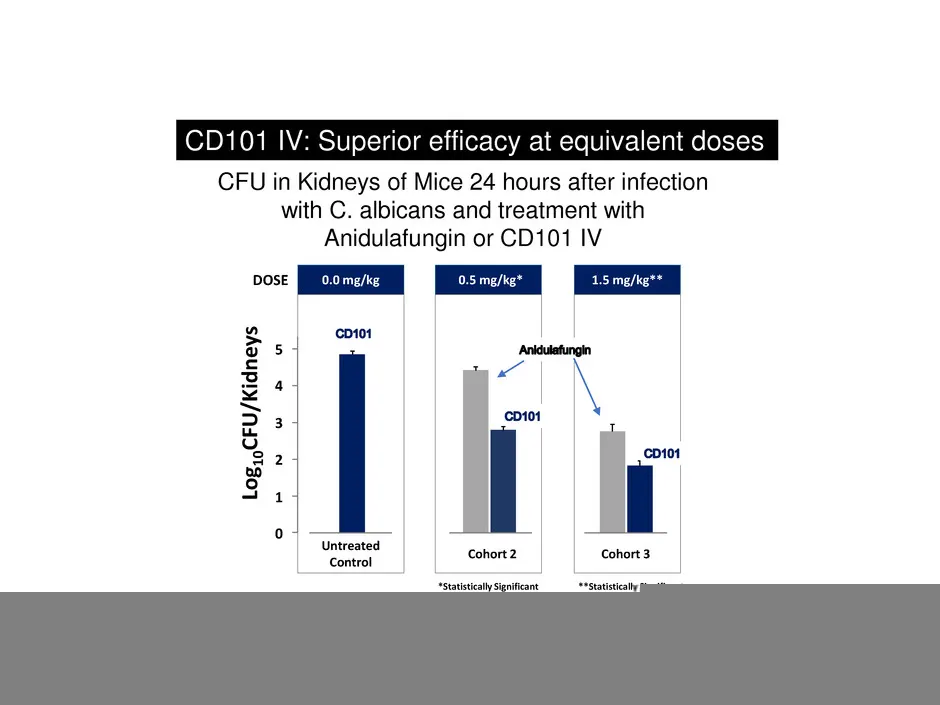
Slide 41: CD101 IV: Superior efficacy at equivalent doses
41 CFU in Kidneys of Mice 24 hours after infection with C. albicans and treatment with Anidulafungin or CD101 IV Lo g 1 0 CFU /Ki d n e ys Untreated Control Cohort 2 Cohort 3 1 2 3 4 5 0 0.5 mg/kg* 1.5 mg/kg**0.0 mg/kgDOSE *Statistically Significant at p < 0.005 **Statistically Significant at p < 0.
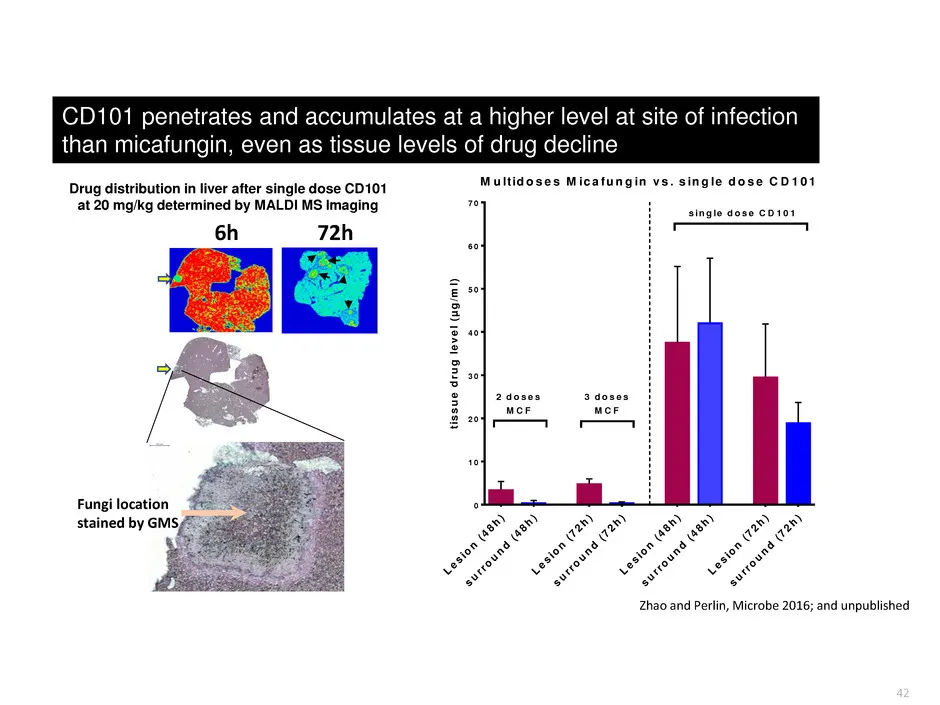
Slide 42: CD101 penetrates and accumulates at site of infection
42 M u ltid o s e s M ic a fu n g in v s . s in g le d o s e C D 1 0 1 L e s io n ( 4 8 h ) s u r r o u n d ( 4 8 h ) L e s io n ( 7 2 h ) s u r r o u n d ( 7 2 h ) L e s io n ( 4 8 h ) s u r r o u n d ( 4 8 h ) L e s io n ( 7 2 h ) s u r r o u n d ( 7 2 h ) 0 1 0 2 0 3 0 4 0 5 0 6 0 7 0 ti s s u e
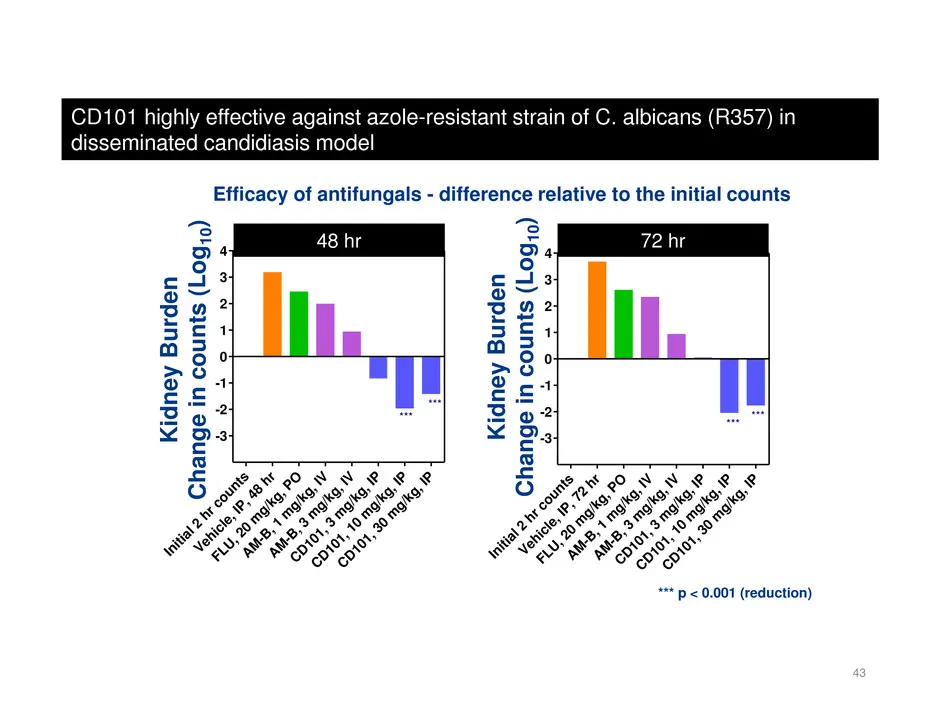
Slide 43: Efficacy of antifungals vs initial counts
Efficacy of antifungals - difference relative to the initial counts Initi al 2 hr co un ts Ve hi cl e, IP , 4 8 h r FL U , 2 0 m g/ kg, P O A M -B , 1 mg/ kg, IV A M -B , 3 mg/ kg, IV C D 10 1, 3 m g/ kg, IP C D 10 1, 1 0 mg/ kg , I P C D 10 1, 3 0 mg/ kg , I P -3 -2 -1 0 1 2 3 4 48 hr after infecti

Slide 44: Candida auris is highly drug-resistant and causes high mortality
44 Candida auris is highly drug-resistant and causes high mortality
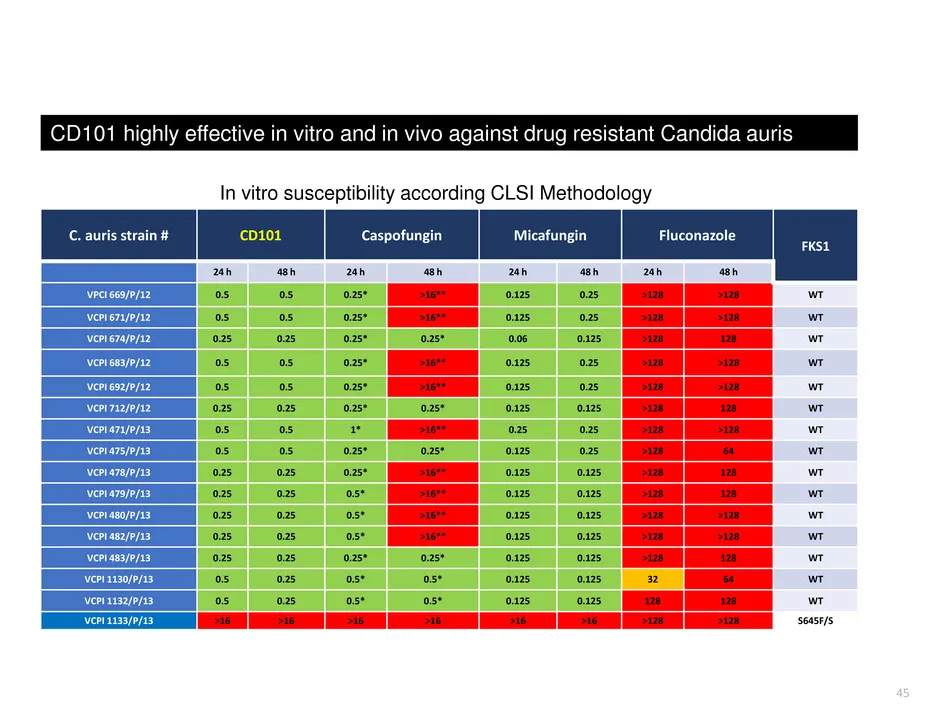
Slide 45: CD101 highly effective against drug resistant Candida auris
45 CD101 highly effective in vitro and in vivo against drug resistant Candida auris C. auris strain # CD101 Caspofungin Micafungin Fluconazole FKS1 24 h 48 h 24 h 48 h 24 h 48 h 24 h 48 h VPCI 669/P/12 0.5 0.5 0.25* >16** 0.125 0.25 >128 >128 WT VCPI 671/P/12 0.5 0.5 0.25* >16** 0.125 0.25 >128 >128
Slide 46: CD101 Summary
46 CD101 is a next-generation echinocandin with expected spectrum of antifungal activity and in vivo efficacy. CD101 is distinguished from other ECN class drugs by its exceptional chemical stability promoting extended PKs, high exposure levels in tissue and at site of infection and overall safet

Slide 47: Introducing Dr. Paul Ambrose
47 Introducing Dr. Paul Ambrose Paul Ambrose, Pharm D. FIDSA President, Institute for Clinical Pharmacodynamics, Inc.

Slide 48: Echinocandin Dosing: An Opportunity for Improvement
Institute for Clinical Pharmacodynamics, Inc. Schenectady, New York Echinocandin Dosing An Opportunity for Improvement

Slide 49: Where are we going today…
Where are we going today… ● How are we selecting systemic antimicrobial dosing regimens today? o Does PK-PD forecast the future? o How do we know that we can sometimes do better? ● Are current echinocandin dosing regimens PK- PD optimized? ● What does a PK-PD-optimized CD101 regimen look like? 49

Slide 50: PK-PD answers critical questions
PK-PD answers critical questions 50

Slide 51: The PK-PD Approach
The PK-PD Approach e-€-S Learn. Confirm. Succeed. ——
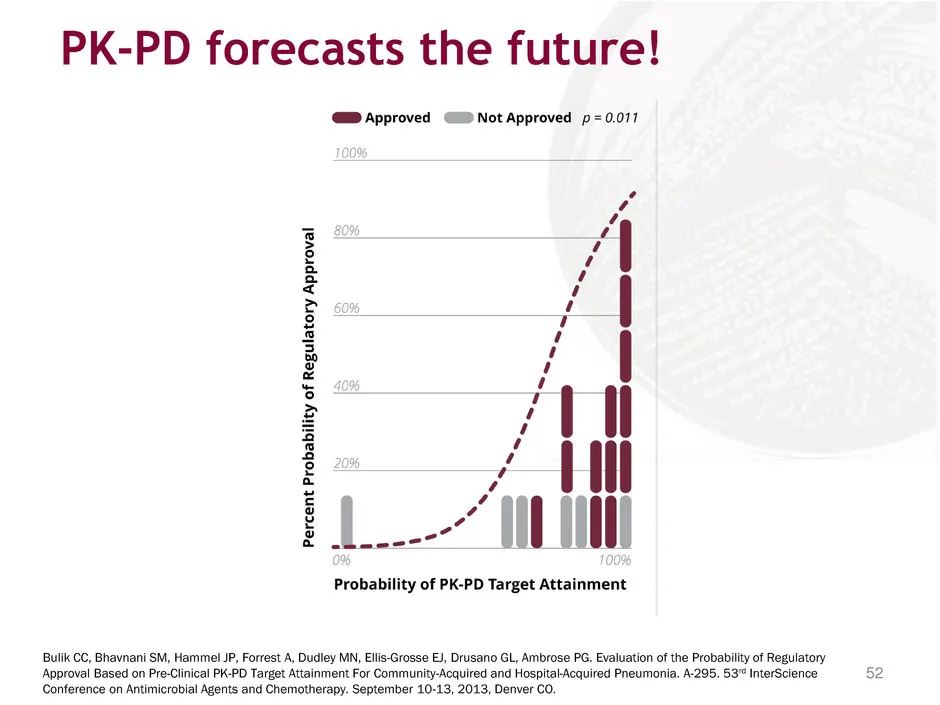
Slide 52: PK-PD forecasts the future!
Bulik CC, Bhavnani SM, Hammel JP, Forrest A, Dudley MN, Ellis-Grosse EJ, Drusano GL, Ambrose PG. Evaluation of the Probability of Regulatory Approval Based on Pre-Clinical PK-PD Target Attainment For Community-Acquired and Hospital-Acquired Pneumonia. A-295. 53rd InterScience Conference on Antimicro
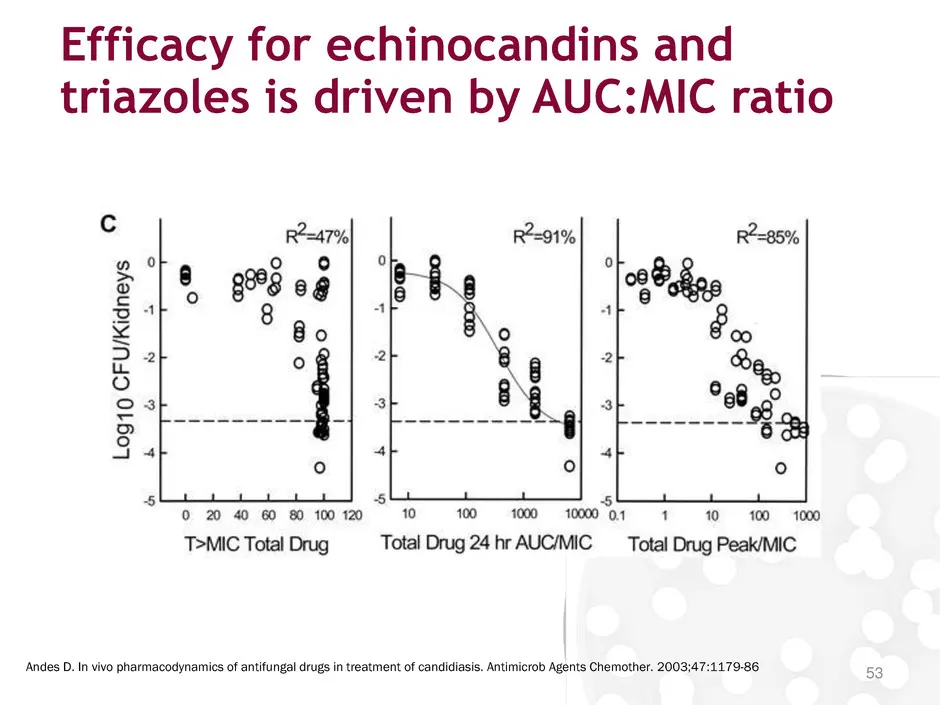
Slide 53: Efficacy driven by AUC:MIC ratio
Andes D. In vivo pharmacodynamics of antifungal drugs in treatment of candidiasis. Antimicrob Agents Chemother. 2003;47:1179-86 Efficacy for echinocandins and triazoles is driven by AUC:MIC ratio 53

Slide 54: Does dose-fractionation work?
Ceftolozane-Tazobactam● Yes! Well, the majority of time, anyway ● The dose-fractionation design provides information on maintenance regimen performance ● It does not provide information on: o The impact of loading doses, o The optimal length of therapy, or o Resistance emergence Does dose-fractionat
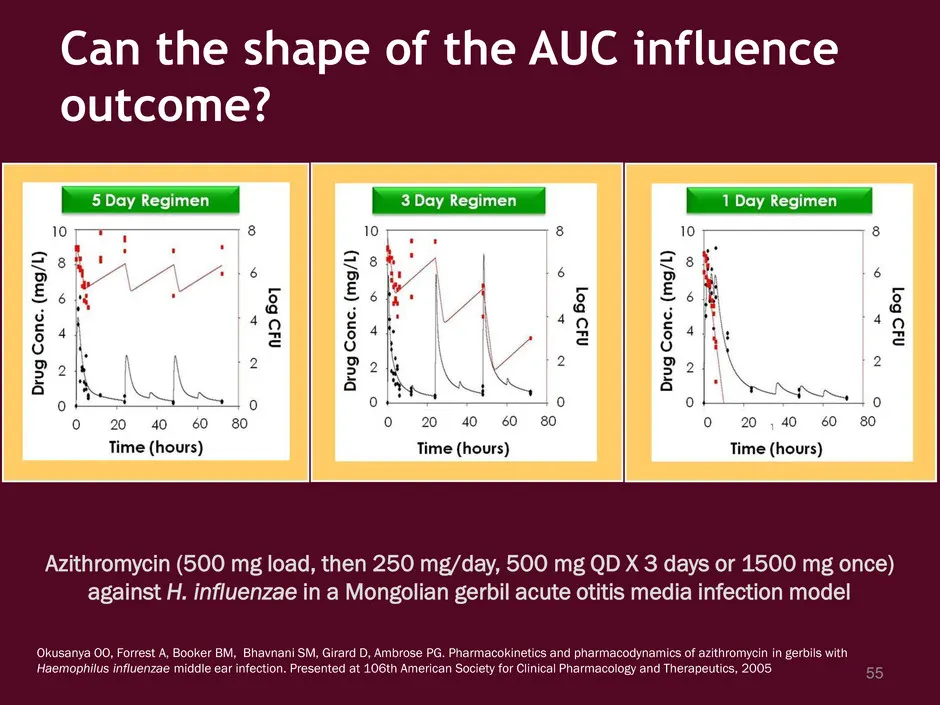
Slide 55: Can the shape of the AUC influence outcome?
Can the shape of the AUC influence outcome? Okusanya OO, Forrest A, Booker BM, Bhavnani SM, Girard D, Ambrose PG. Pharmacokinetics and pharmacodynamics of azithromycin in gerbils with Haemophilus influenzae middle ear infection. Presented at 106th American Society for Clinical Pharmacology and Thera

Slide 56: What is front-loading?
● A front-loaded regimen is defined as one where a significant portion of the total regimen exposure is administered early in therapy o Represents one of the ways we can change exposure shape to optimize outcome ● Can be accomplished as a single large dose or as multiple large doses followed by main

Slide 57: Why consider front-loading?
Why consider front-loading? ● Highest exposure at the time of greatest bacterial density results in the greatest kill possible o Optimizes the likelihood of positive clinical outcome, o Reduces the likelihood of spontaneous mutation, and o Helps eliminate a preexisting resistant subpopulation ● Clin

Slide 58: Where are we going today…
Where are we going today… ● How are we selecting systemic antimicrobial dosing regimens today? o Does PK-PD forecast the future? o How do we know that we can sometimes do better? ● Are current echinocandin dosing regimens PK- PD optimized? ● What does a PK-PD-optimized CD101 regimen look like? 58
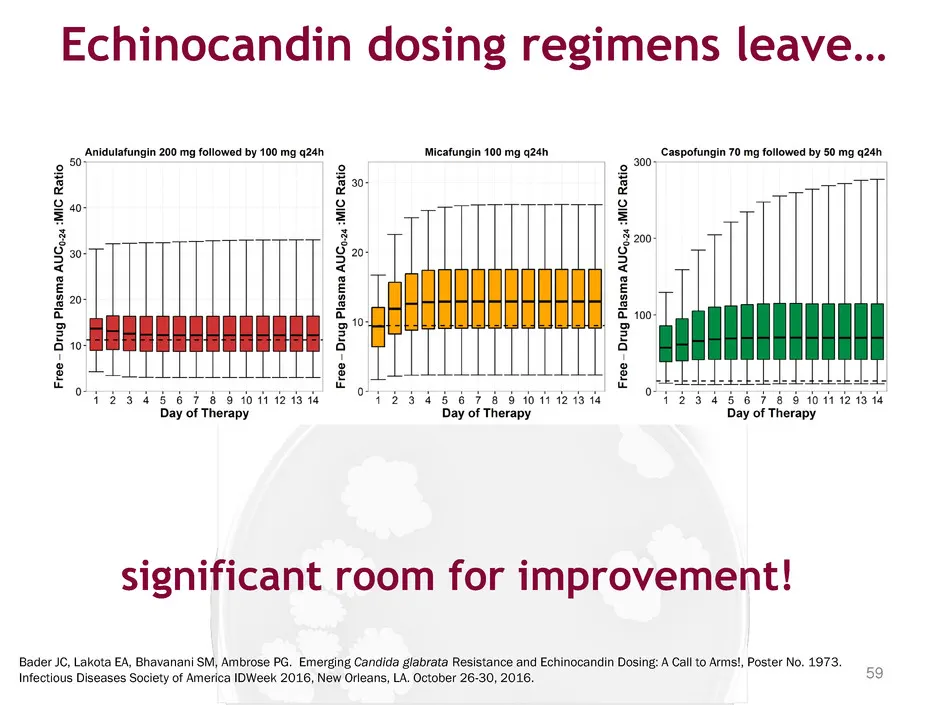
Slide 59: Echinocandin dosing regimens leave significant room for improvement
Ceftolozane-Tazobactam Echinocandin dosing regimens leave… Bader JC, Lakota EA, Bhavanani SM, Ambrose PG. Emerging Candida glabrata Resistance and Echinocandin Dosing: A Call to Arms!, Poster No. 1973. Infectious Diseases Society of America IDWeek 2016, New Orleans, LA. October 26-30, 2016. signific

Slide 60: Where are we going today…
Where are we going today… ● How are we selecting systemic antimicrobial dosing regimens today? o Does PK-PD forecast the future? o How do we know that we can sometimes do better? ● Are current echinocandin dosing regimens PK- PD optimized? ● What does a PK-PD-optimized CD101 regimen look like? 60
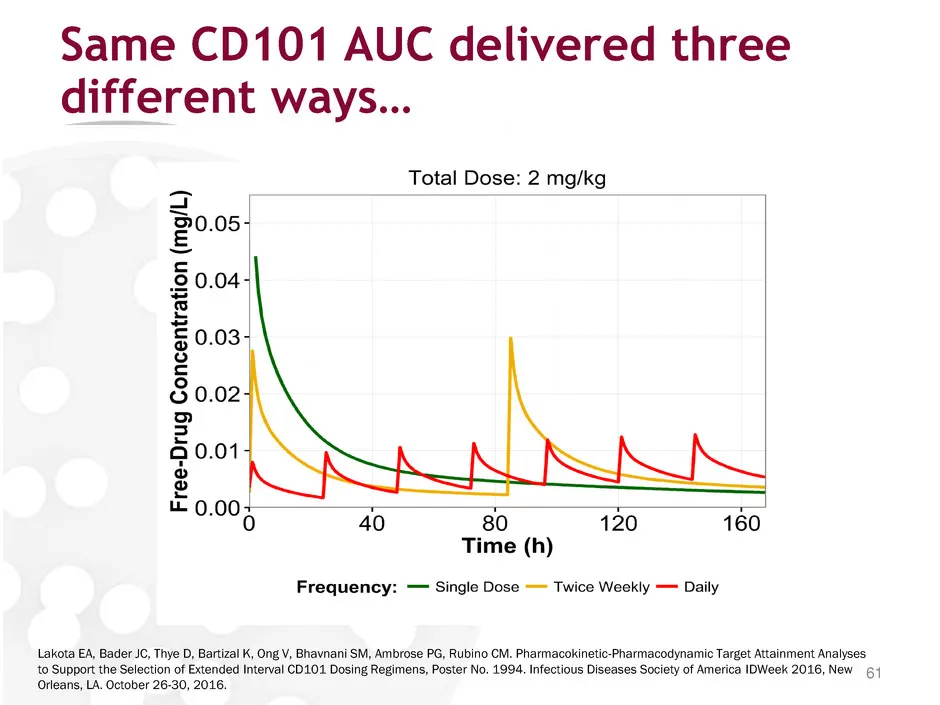
Slide 61: Same CD101 AUC delivered three different ways
Ceftolozane-Tazobactam Same CD101 AUC delivered three different ways… Lakota EA, Bader JC, Thye D, Bartizal K, Ong V, Bhavnani SM, Ambrose PG, Rubino CM. Pharmacokinetic-Pharmacodynamic Target Attainment Analyses to Support the Selection of Extended Interval CD101 Dosing Regimens, Poster No. 1994. I
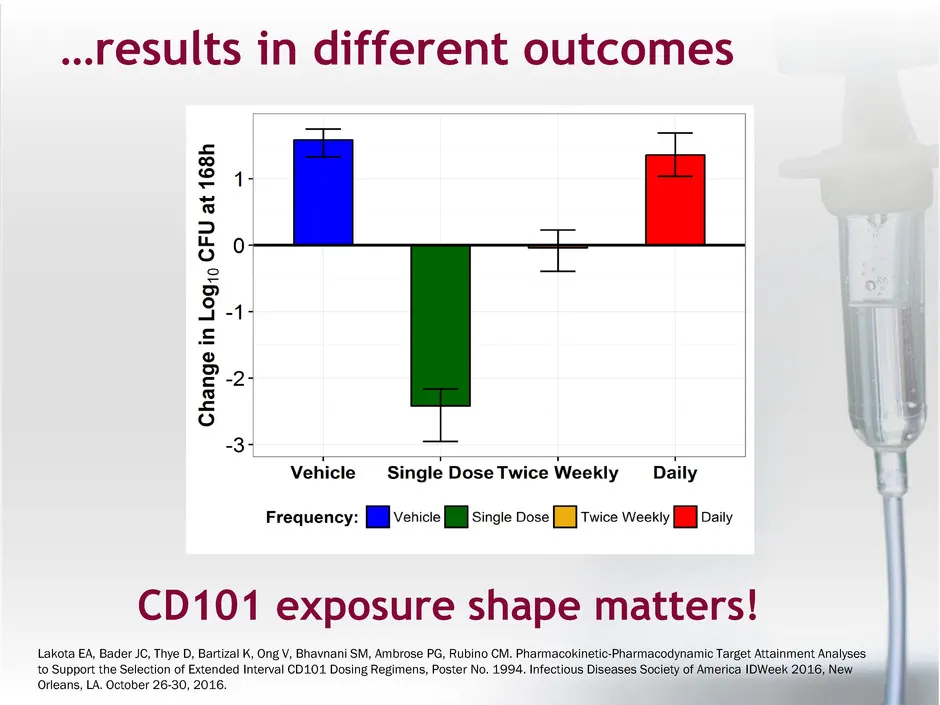
Slide 62: CD101 exposure shape matters!
…results in different outcomes CD101 exposure shape matters! Lakota EA, Bader JC, Thye D, Bartizal K, Ong V, Bhavnani SM, Ambrose PG, Rubino CM. Pharmacokinetic-Pharmacodynamic Target Attainment Analyses to Support the Selection of Extended Interval CD101 Dosing Regimens, Poster No. 1994. Infectious
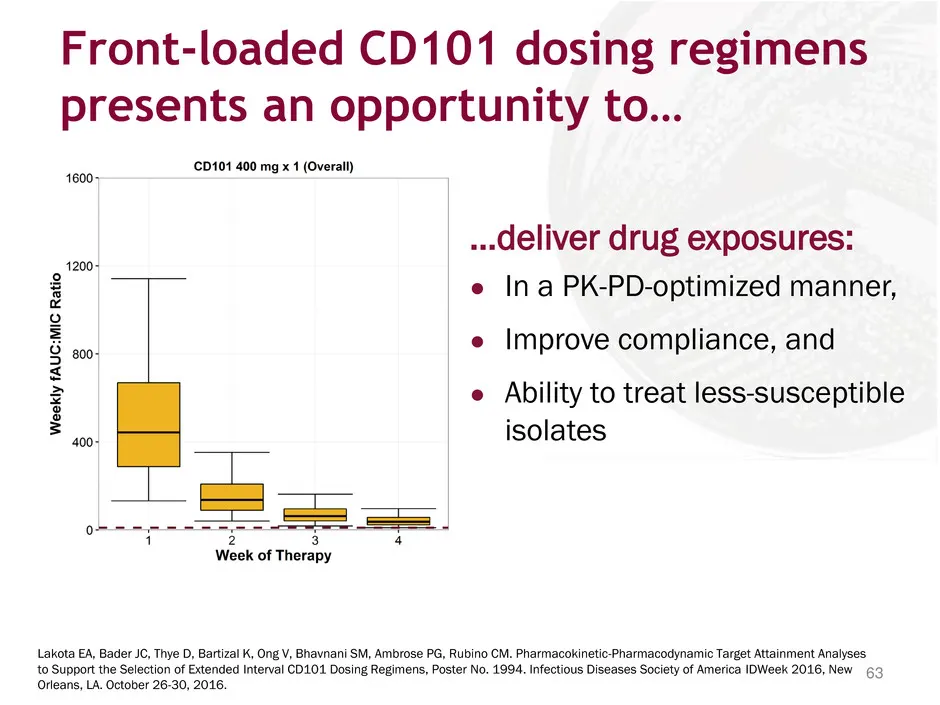
Slide 63: Front-loaded CD101 dosing regimens presents an opportunity
Front-loaded CD101 dosing regimens presents an opportunity to… …deliver drug exposures: ● In a PK-PD-optimized manner, ● Improve compliance, and ● Ability to treat less-susceptible isolates Lakota EA, Bader JC, Thye D, Bartizal K, Ong V, Bhavnani SM, Ambrose PG, Rubino CM. Pharmacokinetic-Pharmacody
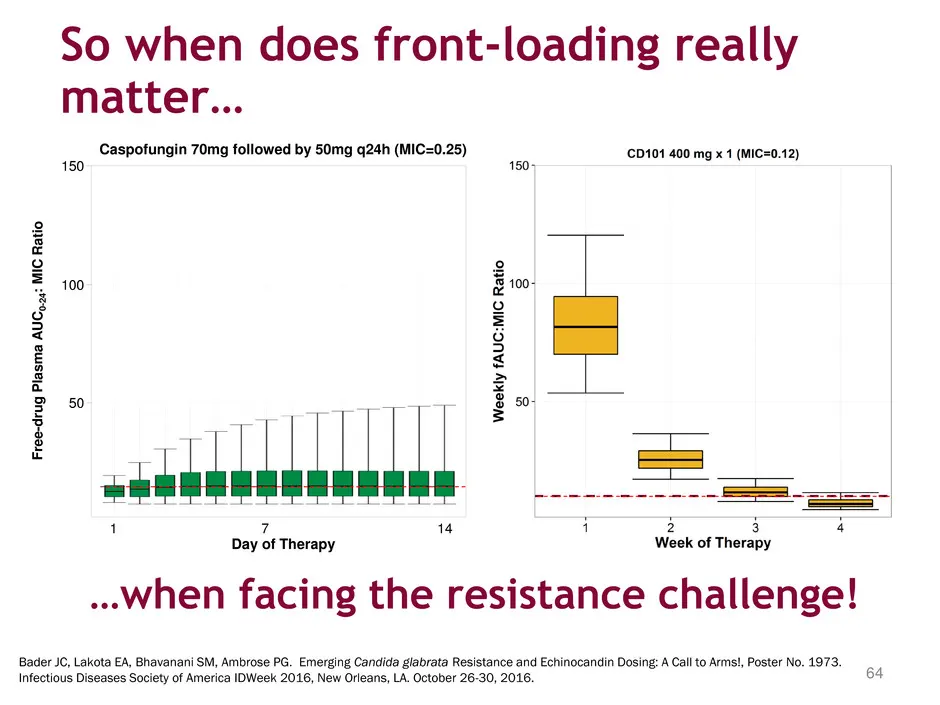
Slide 64: When does front-loading really matter
Ceftolozane-Tazobactam So when does front-loading really matter… Bader JC, Lakota EA, Bhavanani SM, Ambrose PG. Emerging Candida glabrata Resistance and Echinocandin Dosing: A Call to Arms!, Poster No. 1973. Infectious Diseases Society of America IDWeek 2016, New Orleans, LA. October 26-30, 2016. …w

Slide 65: Conclusions
Conclusions… •There is significant room for improvement in how echinocandins are dosed, especially… o Anidulafungin and micafungin o Caspofungin against less susceptible strains • CD101 clearly benefits in vivo from front-loading exposure o Optimizes the likelihood of positive clinical outcome, o Th

Slide 66: Thank you for your attention.
Thank you for your attention.

Slide 67: Introducing Dr. Taylor Sandison
67 Introducing Dr. Taylor Sandison Chief Medical Officer, Cidara Therapeutics M.D. and M.P.H. from the University of Washington Diploma in Tropical Medicine and Hygiene (DTM&H) from the London School of Hygiene and Tropical Medicine Board certified in Infectious Diseases and Internal Medicin

Slide 68: CD101 Clinical Trials
CD101 Clinical Trials
Slide 69: CD101 IV: Streamlined Development Plan
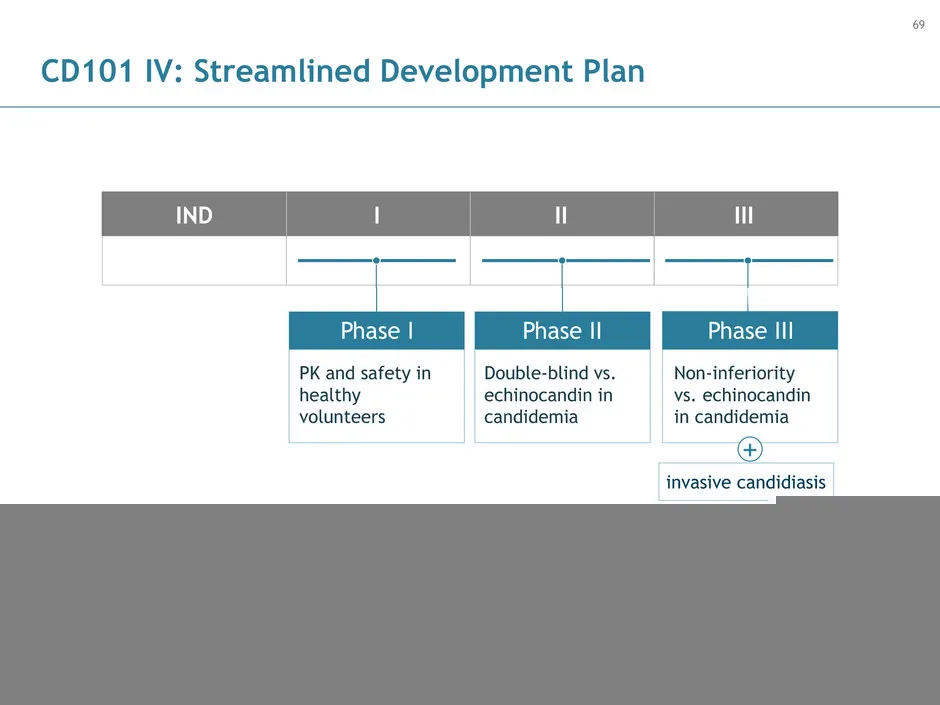
69 CD101 IV: Streamlined Development Plan PK and safety in healthy volunteers Double-blind vs. echinocandin in candidemia Phase I Phase II Non-inferiority vs. echinocandin in candidemia IND I II III Phase III + invasive candidiasis 69
Slide 70: Phase 1 SAD and MAD Study Designs
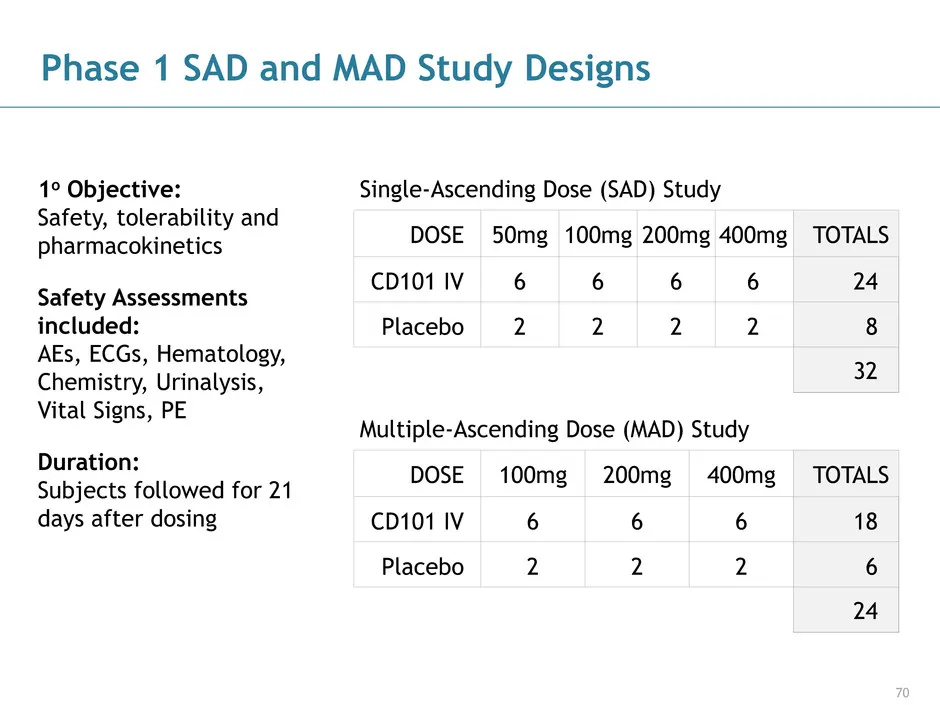
70 Phase 1 SAD and MAD Study Designs DOSE 50mg 100mg 200mg 400mg CD101 IV Placebo TOTALS 6 6 6 6 2 2 2 2 24 8 32 1o Objective: Safety, tolerability and pharmacokinetics Safety Assessments included: AEs, ECGs, Hematology, Chemistry, Urinalysis, Vital Signs, PE Duration: Subjects followed for 21 days
Slide 71: Summary: CD101 IV Phase 1 SAD/MAD Studies
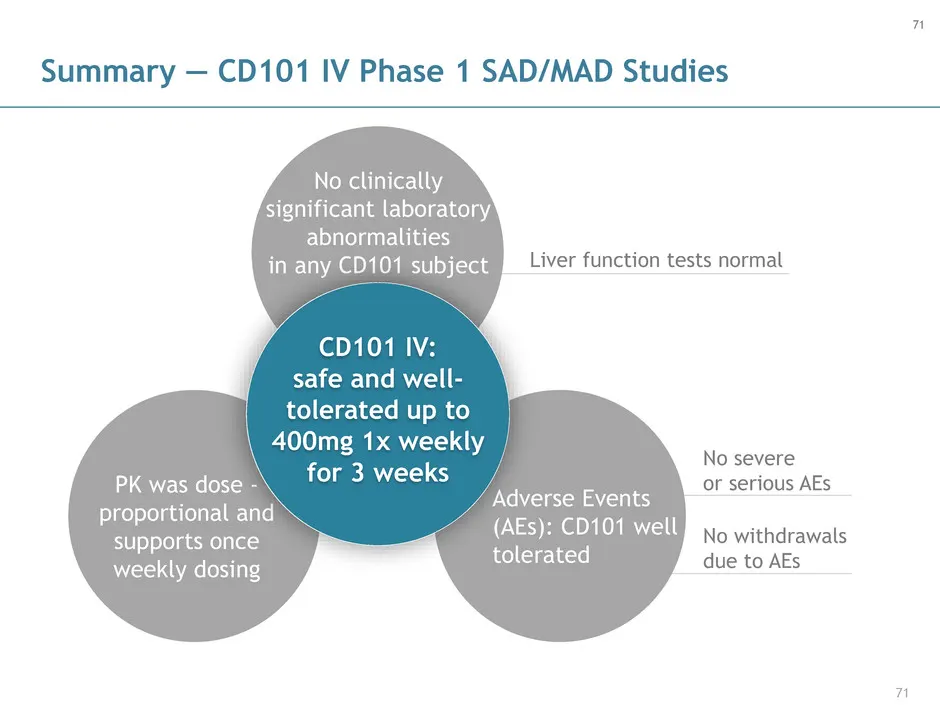
71 Summary — CD101 IV Phase 1 SAD/MAD Studies No severe or serious AEs No withdrawals due to AEs PK was dose - proportional and supports once weekly dosing No clinically significant laboratory abnormalities in any CD101 subject Adverse Events (AEs): CD101 well tolerated CD101 IV: safe and well- tole
Slide 72: STRIVE trial: Candidemia & Invasive Candidiasis
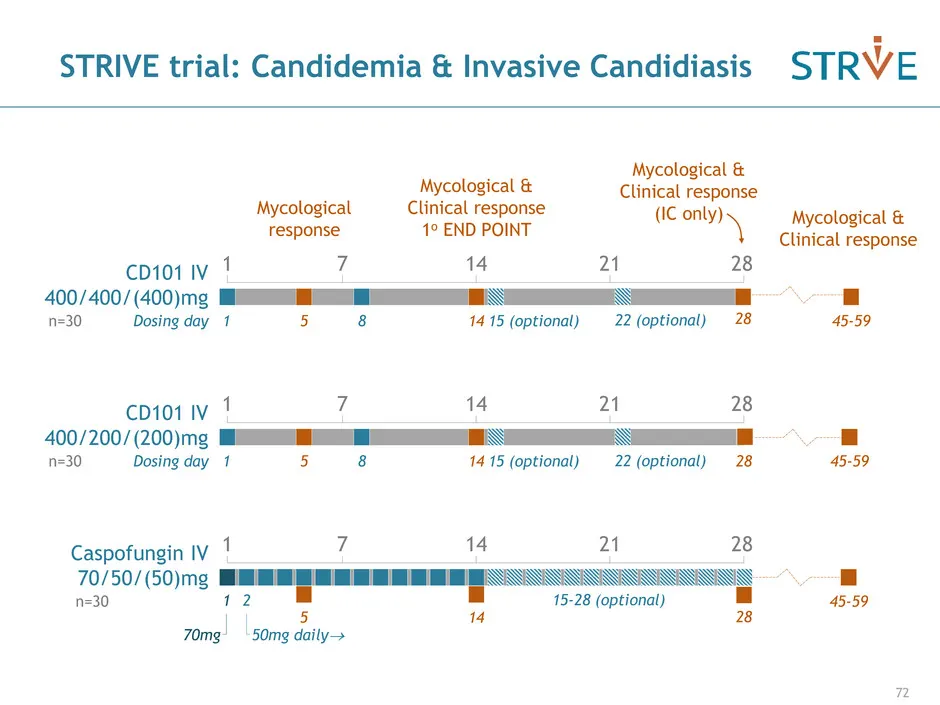
72 STRIVE trial: Candidemia & Invasive Candidiasis CD101 IV 400/400/(400)mg 1 8Dosing day 15 (optional)5 Mycological response 14 Mycological & Clinical response 1o END POINT Mycological & Clinical response 45-59n=30 1 7 14 21 28 22 (optional) Mycological & Clinical response (IC only) CD101 IV 400/20
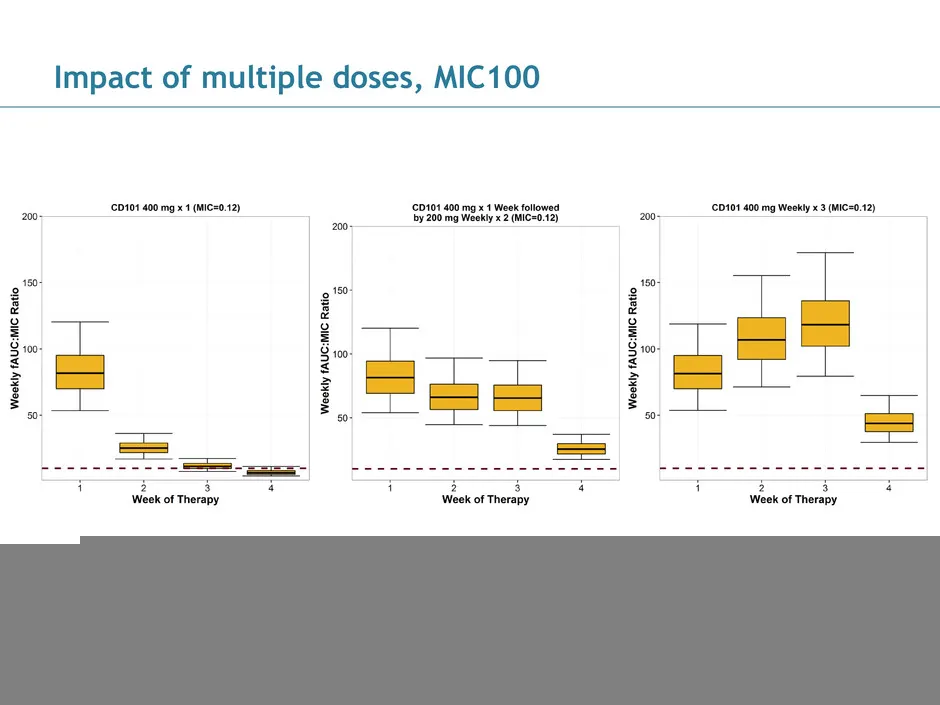
Slide 73: Impact of multiple doses, MIC100
73 Impact of multiple doses, MIC100 73

Slide 74: STRIVE on Target for Topline data in Q4 2017
74 STRIVE on Target for Topline data in Q4 2017 Sites currently active in US, Spain, Italy, Greece, Bulgaria Build out Phase 2 study in preparation for Phase 3 • Activating new sites: Canada, Belgium, Hungary, Romania, Russia • Adding invasive candidiasis patients to the study patient population

Slide 75: FDA Agrees to Program with Single Phase 2 and Phase 3
75 FDA Agrees to Program with Single Phase 2 and Phase 3 Phase 2 (STRIVE) study and Phase 3 study will have similar study design, inclusion/exclusion criteria, and enrollment expectations Phase 3: Non-inferiority trial design vs caspofungin Phase 3 scheduled to start mid-2018 Planning concur

Slide 76: CD101 IV: On Track for Approval in Candidemia/IC
76 CD101 IV: On Track for Approval in Candidemia/IC 2016 2017 2018 2019 2020 2021 CD101 IV for systemic infections CD101 IV for prophylaxis Ph2 Candidemia/IC Ph3 Candidemia/IC Ph2 Invasive Candidiasis Study Data Data NDA Prophylaxis Ph2, or Data Streamlined program for 1x weekly CD101, projected f

Slide 77: Introducing Dr. Kieren Marr
77 Introducing Dr. Kieren Marr Professor of Medicine, Johns Hopkins School of Medicine Professor of Oncology, Sidney Kimmel Comprehensive Cancer Center Professor of Business, JH Carey School of Business Vice Chair for Innovation in Healthcare Implementation Director, Transplant and Oncolog

Slide 78: Antifungals and Opportunities
Antifungals and Opportunities Kieren A. Marr MD
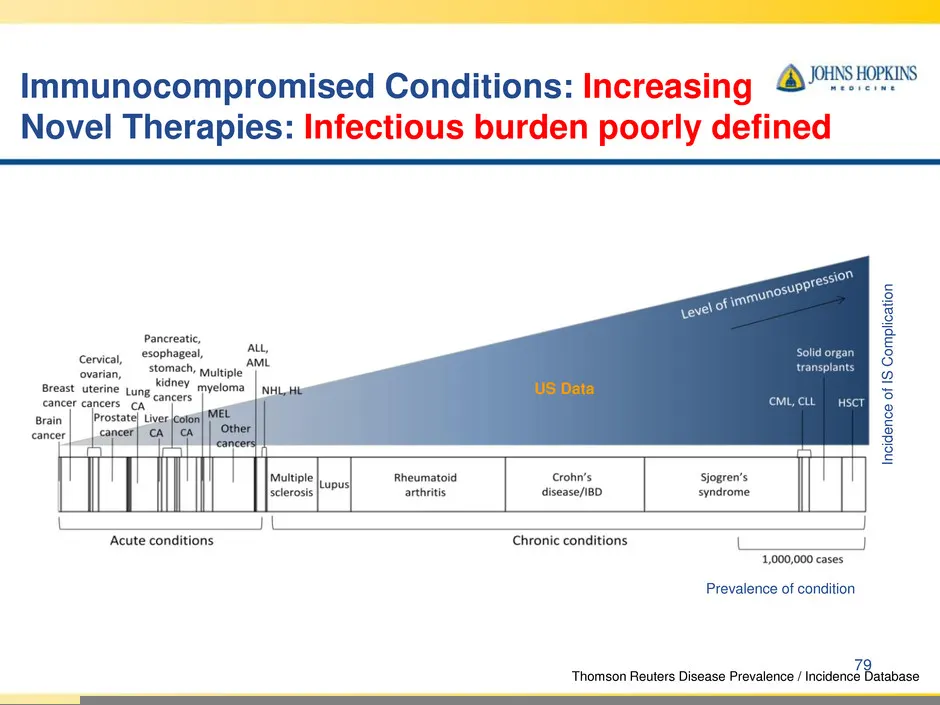
Slide 79: Immunocompromised Conditions: Increasing Novel Therapies
Immunocompromised Conditions: Increasing Novel Therapies: Infectious burden poorly defined US Data Prevalence of condition In c id e n c e o f IS C om p lic a ti o n Thomson Reuters Disease Prevalence / Incidence Database 79
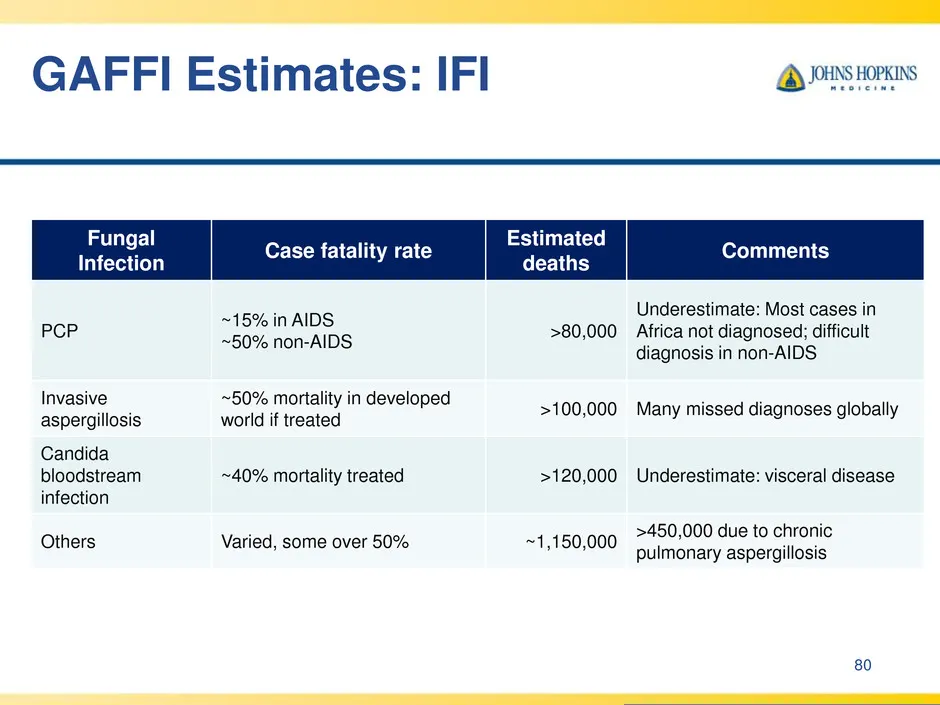
Slide 80: GAFFI Estimates: IFI
GAFFI Estimates: IFI Fungal Infection Case fatality rate Estimated deaths Comments PCP ~15% in AIDS ~50% non-AIDS >80,000 Underestimate: Most cases in Africa not diagnosed; difficult diagnosis in non-AIDS Invasive aspergillosis ~50% mortality in developed world if treated >100,000 Many missed diagno
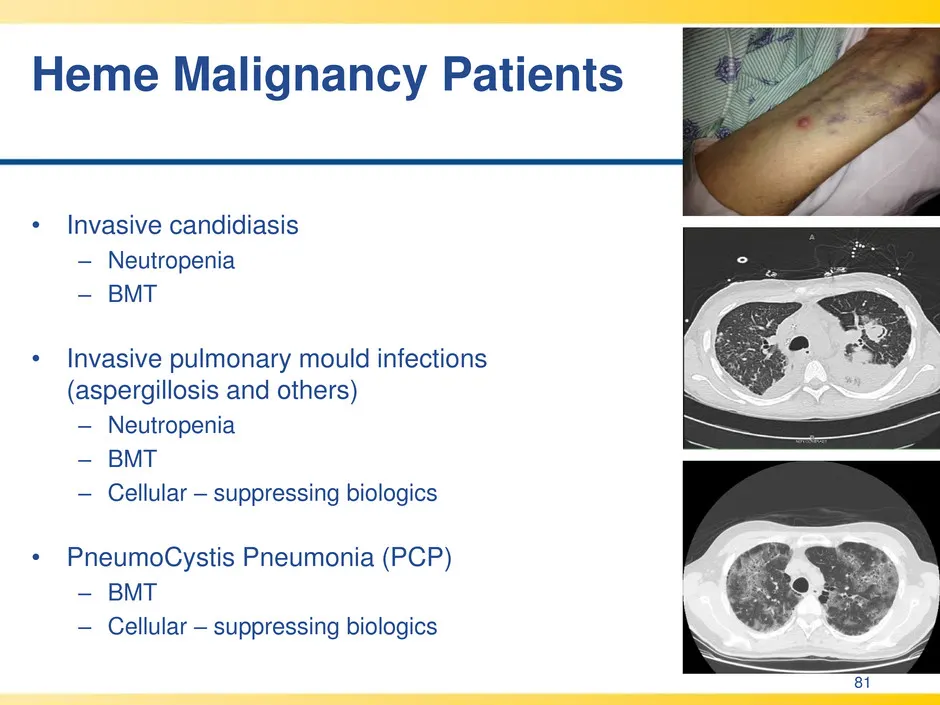
Slide 81: Heme Malignancy Patients
• Invasive candidiasis – Neutropenia – BMT • Invasive pulmonary mould infections (aspergillosis and others) – Neutropenia – BMT – Cellular – suppressing biologics • PneumoCystis Pneumonia (PCP) – BMT – Cellular – suppressing biologics Heme Malignancy Patients 81
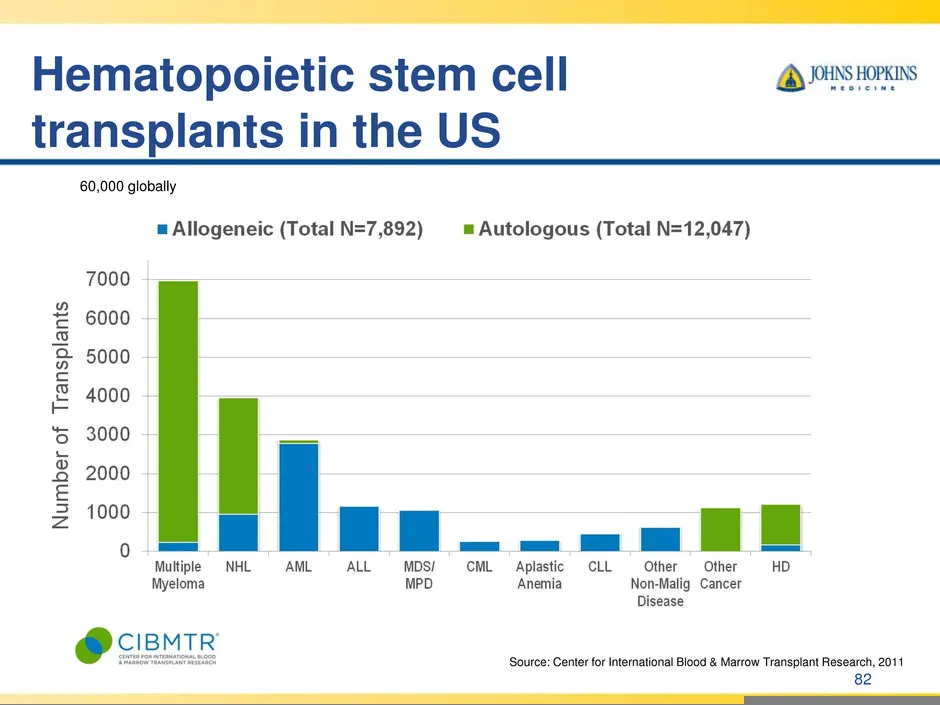
Slide 82: Hematopoietic stem cell transplants in the US
Hematopoietic stem cell transplants in the US Source: Center for International Blood & Marrow Transplant Research, 2011 60,000 globally 82
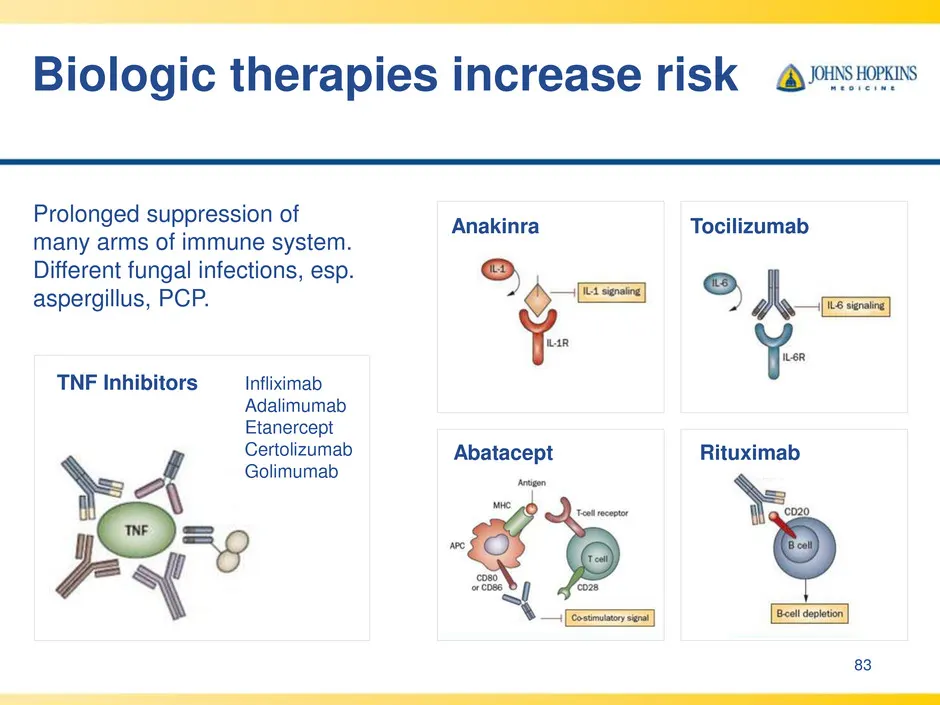
Slide 83: Biologic therapies increase risk
Biologic therapies increase risk Prolonged suppression of many arms of immune system. Different fungal infections, esp. aspergillus, PCP. TNF Inhibitors Anakinra Tocilizumab Abatacept Rituximab Infliximab Adalimumab Etanercept Certolizumab Golimumab 83
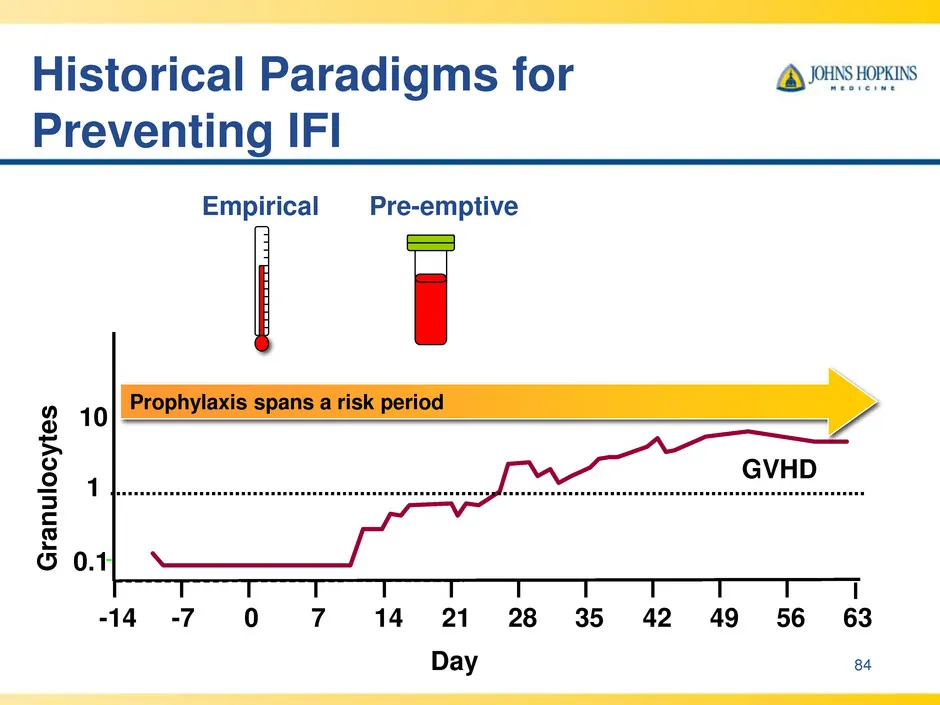
Slide 84: Historical Paradigms for Preventing IFI
Historical Paradigms for Preventing IFI -7 0 7 14 21 28 35 42 49 56 63-14 0.1 1 10 Granuloc y te s Day Prophylaxis spans a risk period Empirical Pre-emptive Clinical symptoms/signs Antigenemia / PCR GVHD 84
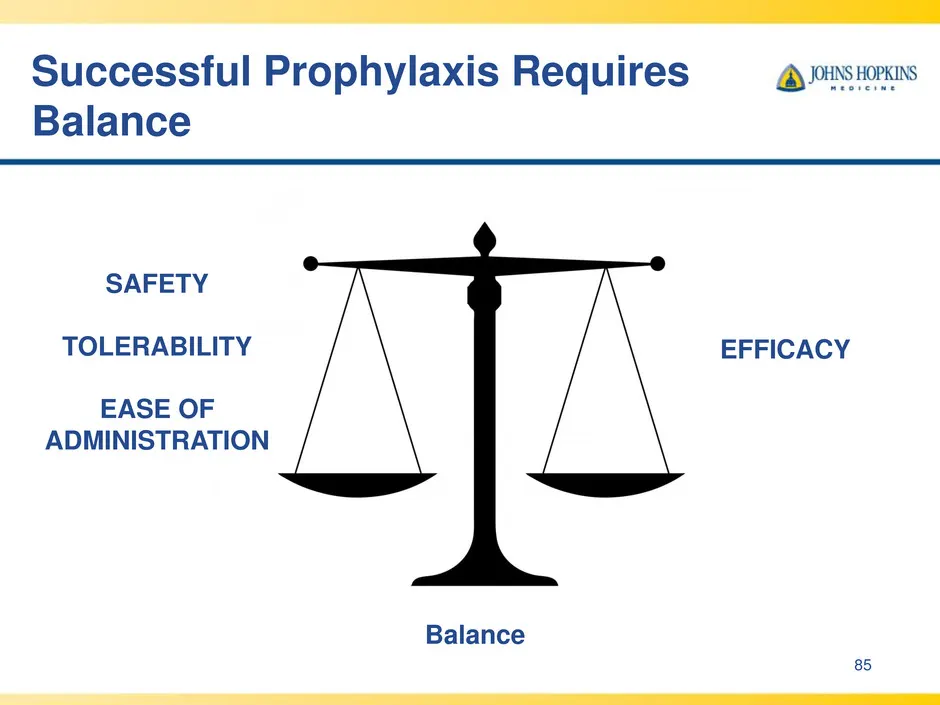
Slide 85: Successful Prophylaxis Requires Balance
Successful Prophylaxis Requires Balance SAFETY TOLERABILITY EASE OF ADMINISTRATION EFFICACY Balance 85
Slide 86: Prophylaxis Standards
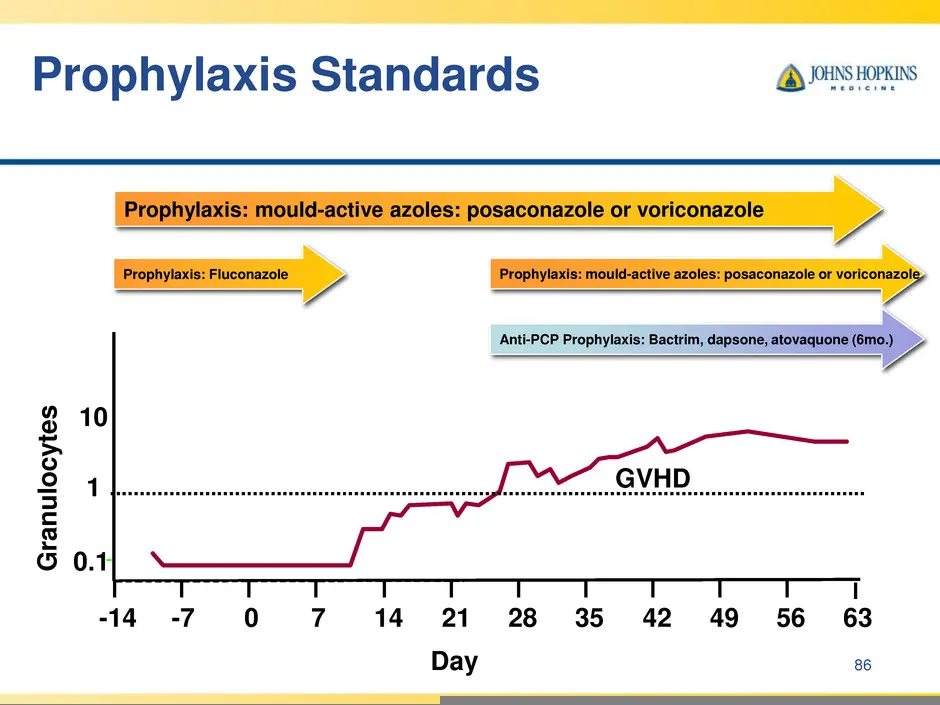
Prophylaxis Standards -7 0 7 14 21 28 35 42 49 56 63-14 0.1 1 10 Granuloc y te s Day Prophylaxis: mould-active azoles: posaconazole or voriconazole GVHD Prophylaxis: mould-active azoles: posaconazole or voriconazoleProphylaxis: Fluconazole Anti-PCP Prophylaxis: Bactrim, dapsone, atovaquone (6mo.) 86
Slide 87: Many Problems with Azoles
Many Problems with Azoles • Azoles pre-engraftment and with GVHD – Liver toxicities, neuro toxicities – Rash, skin cancer, intolerance – Level monitoring – On & off - drug interactions – Breakthrough infections common 87
Slide 88: Many Problems with Bactrim
Many Problems with Bactrim… • Bactrim post-engraftment (6mo.) – Rash / “allergy” in 20% – Kidney toxicity – Bone marrow toxicity – Intolerance dapsone, atovaquone, pentamidine • Less effective; 10% breakthrough, 50% mortality 88
Slide 89: Pneumocystis (PCP) prophylaxis
• Trimethoprim-sulfamethoxazole (TMP-SMX) recommended first-line agent based on efficacy (83% reduction in PCP mortality) • TMP-SMX discontinuation rates between 20–40% • Tolerability of TMP-SMX alternatives (dapsone, atovaquone, pentamidine) even worse, and breakthrough common (10–20%) • TMP-SMX re

Slide 90: Biologics: increasing troubles with PCP
Biologics: increasing troubles with PCP • TNFα inhibitors: example: Campath, etanercept • Tyrosine kinase inhibitor: Ibrutinib – PCP infection warning added to label April ‘17 • Rituxan (especially in certain diseases: CLL, vasculitis) • B Cell receptor PI3K inhibitor: Idelalisib clinical trials sto

Slide 91: 91
91

Slide 92: Unmet Needs
• Azoles work well to prevent yeasts and molds but use is limited by intolerance, toxicity and drug interactions – Breakthrough infection still very common • PCP is preventable but current drugs limited by intolerance and toxicities – Breakthrough infection becoming more common • High mortality at h
Slide 93: Opportunity: CD101 to prevent Candida, Aspergillus and PCP
• Echinocandins have shown efficacy in a range of PCP models, but not all echinocandins show the same efficacy • Echinocandins may play a larger role in PCP prevention given the higher escalating rates of P. jirovecii resistance to TMP-SMX • CD101 strongly inhibits bD glucan synthesis, the main prop
Slide 94: PCP prophylaxis with CD101 highly effective
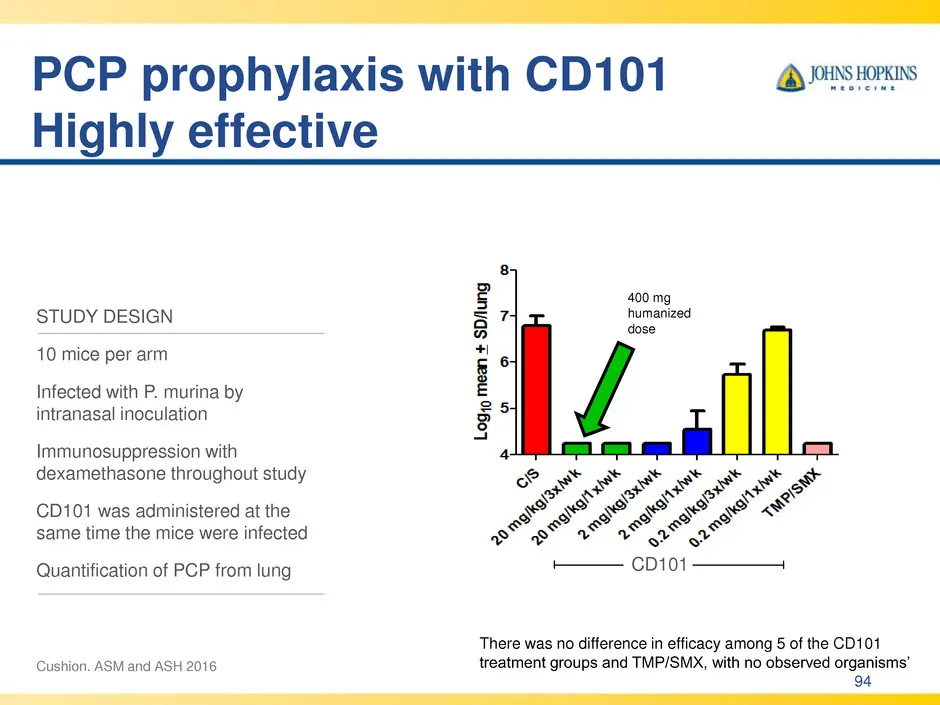
PCP prophylaxis with CD101 Highly effective Cushion. ASM and ASH 2016 STUDY DESIGN 10 mice per arm Infected with P. murina by intranasal inoculation Immunosuppression with dexamethasone throughout study CD101 was administered at the same time the mice were infected Quantification of PCP from lung *D
Slide 95: Aspergillus prophylaxis with CD101, 100% success at humanized doses
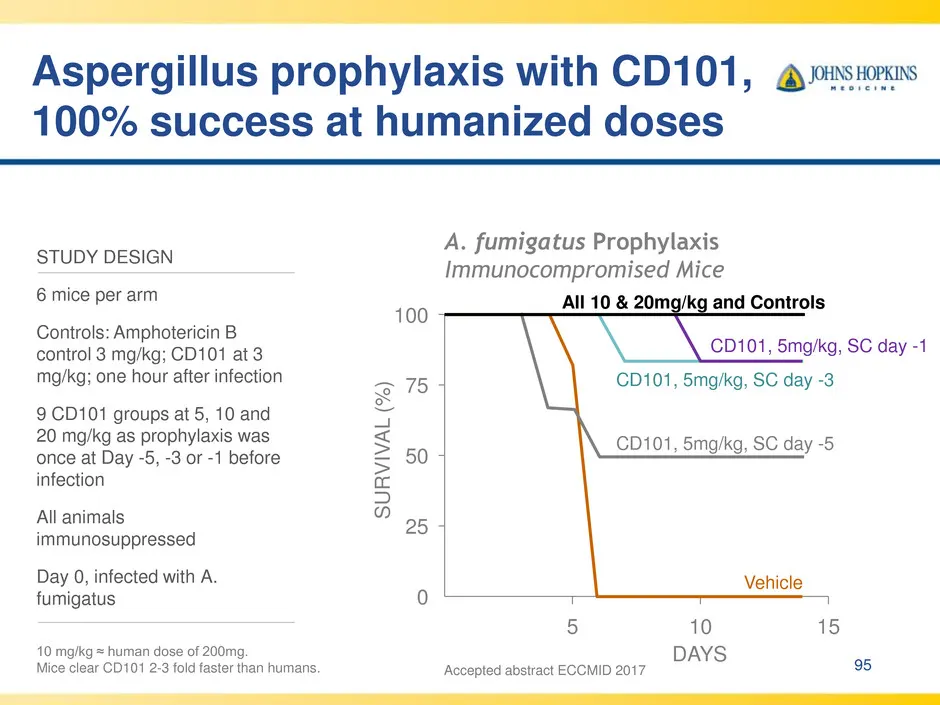
Aspergillus prophylaxis with CD101, 100% success at humanized doses 10 mg/kg ≈ human dose of 200mg. Mice clear CD101 2-3 fold faster than humans. Accepted abstract ECCMID 2017 STUDY DESIGN 6 mice per arm Controls: Amphotericin B control 3 mg/kg; CD101 at 3 mg/kg; one hour after infection 9 CD101 gro
Slide 96: CD101: broad spectrum prophylaxis clinical trial
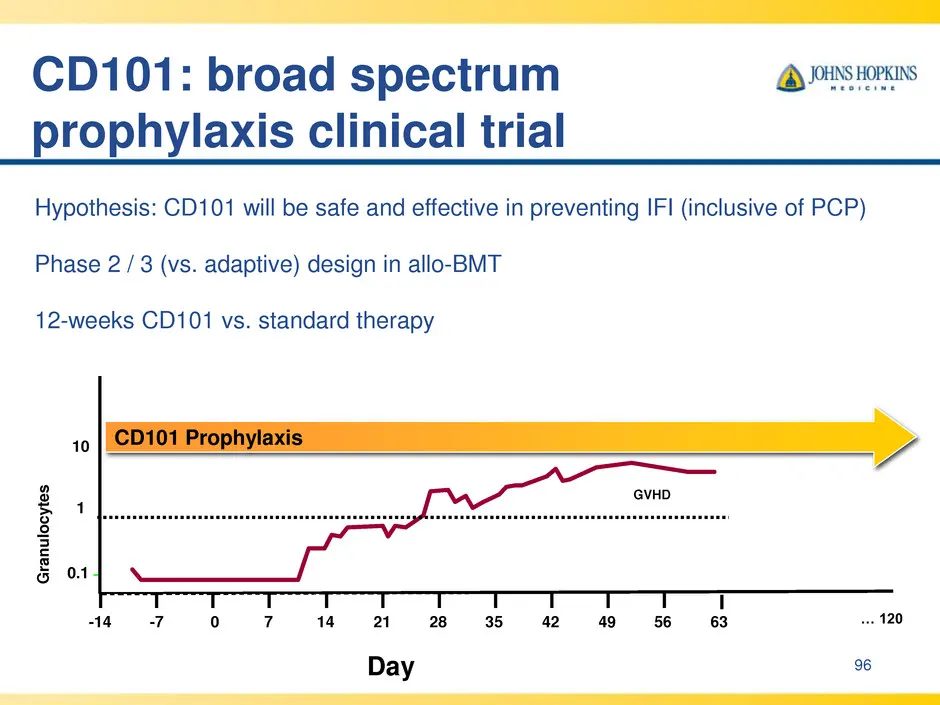
CD101: broad spectrum prophylaxis clinical trial -7 0 7 14 21 28 35 42 49 56 63-14 0.1 1 10 Gr a nulo c y te s Day CD101 Prophylaxis Clinical symptoms/signs Antigenemia / PCR GVHD Hypothesis: CD101 will be safe and effective in preventing IFI (inclusive of PCP) Phase 2 / 3 (vs. adaptive) design in a

Slide 97: Introducing Paul Daruwala
97 Introducing Paul Daruwala Chief Commercial Officer, Cidara Therapeutics
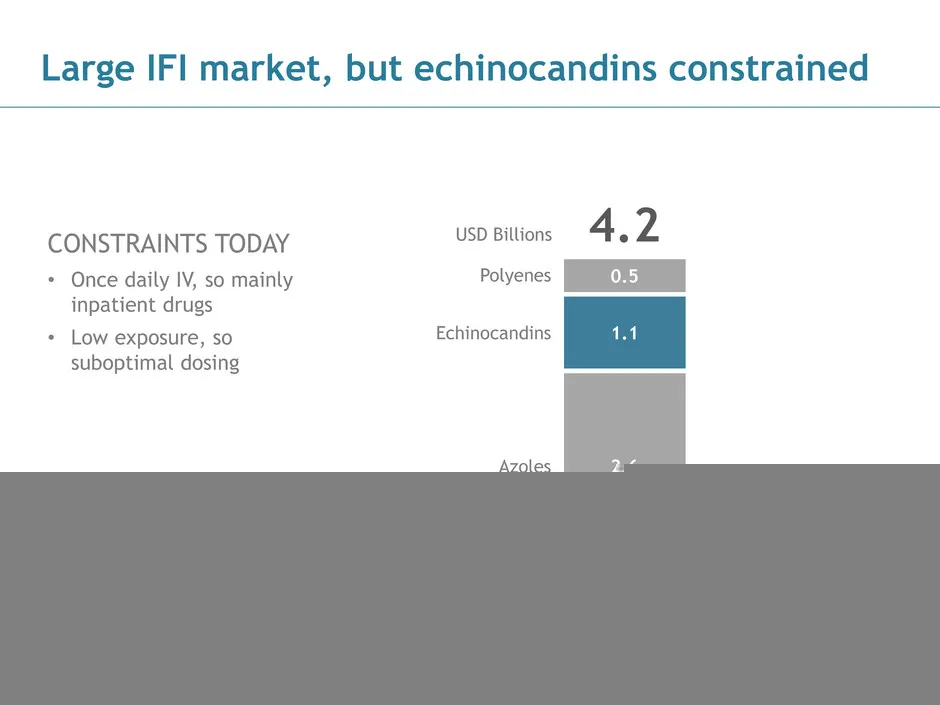
Slide 98: Large IFI market, but echinocandins constrained
98 Large IFI market, but echinocandins constrained CONSTRAINTS TODAY • Once daily IV, so mainly inpatient drugs • Low exposure, so suboptimal dosing 1.1 2.6 0.5 4.2 Polyenes Echinocandins Azoles USD Billions
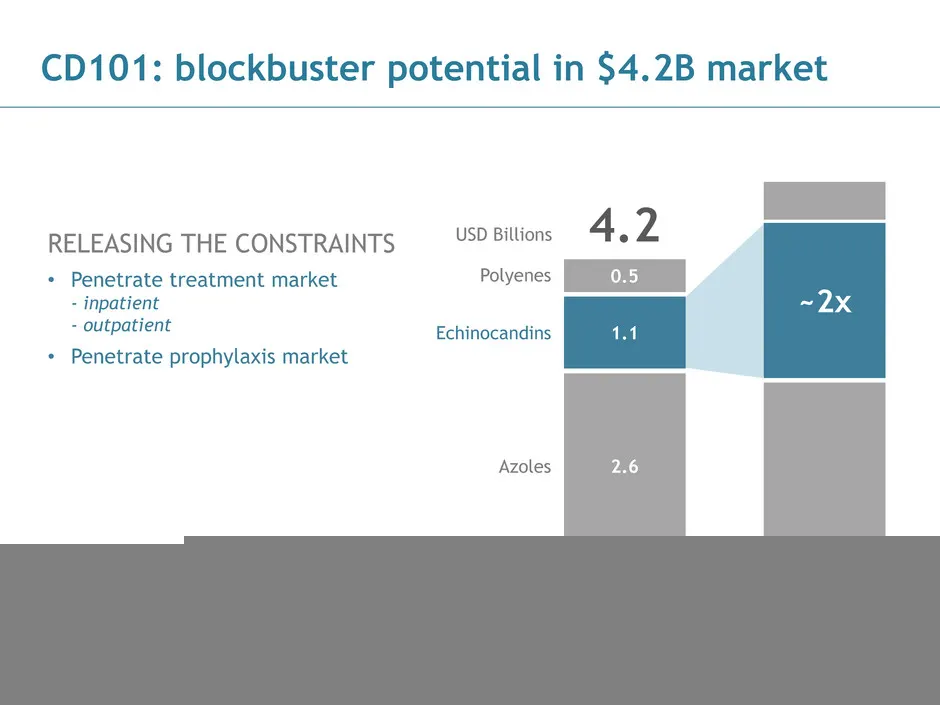
Slide 99: CD101: blockbuster potential in $4.2B market
99 CD101: blockbuster potential in $4.2B market 1.1 2.6 0.5 4.2 Polyenes Echinocandins Azoles ~2x USD BillionsRELEASING THE CONSTRAINTS • Penetrate treatment market - inpatient - outpatient • Penetrate prophylaxis market
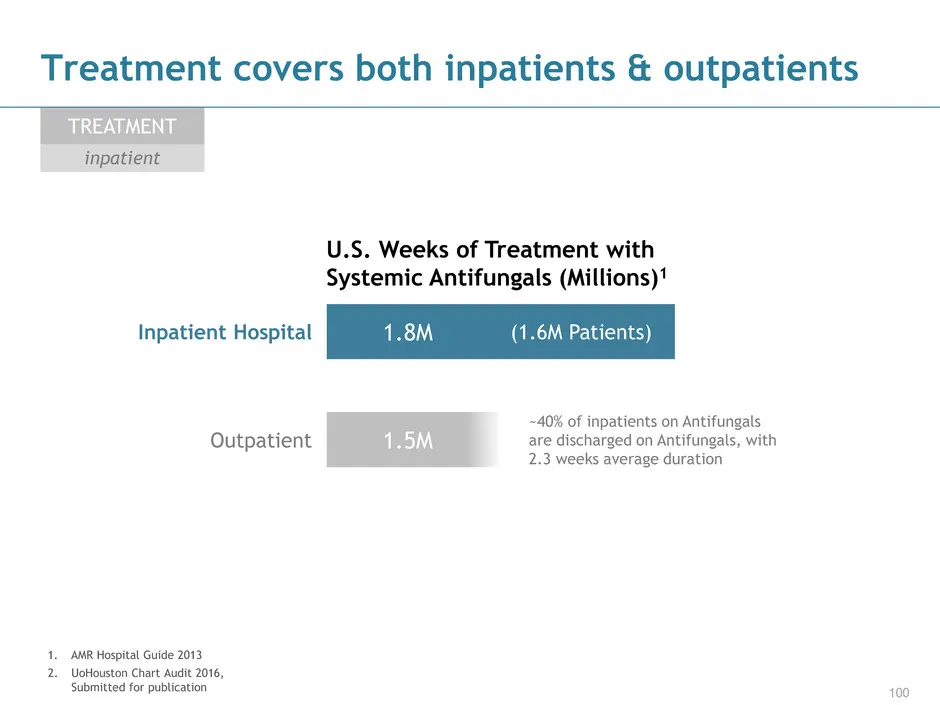
Slide 100: Treatment covers both inpatients & outpatients
100 inpatient Treatment covers both inpatients & outpatients U.S. Weeks of Treatment with Systemic Antifungals (Millions)1 Inpatient Hospital Outpatient (1.6M Patients) ~40% of inpatients on Antifungals are discharged on Antifungals, with 2.3 weeks average duration 1.8M 1.5M TREATMENT 1. AMR Hospita
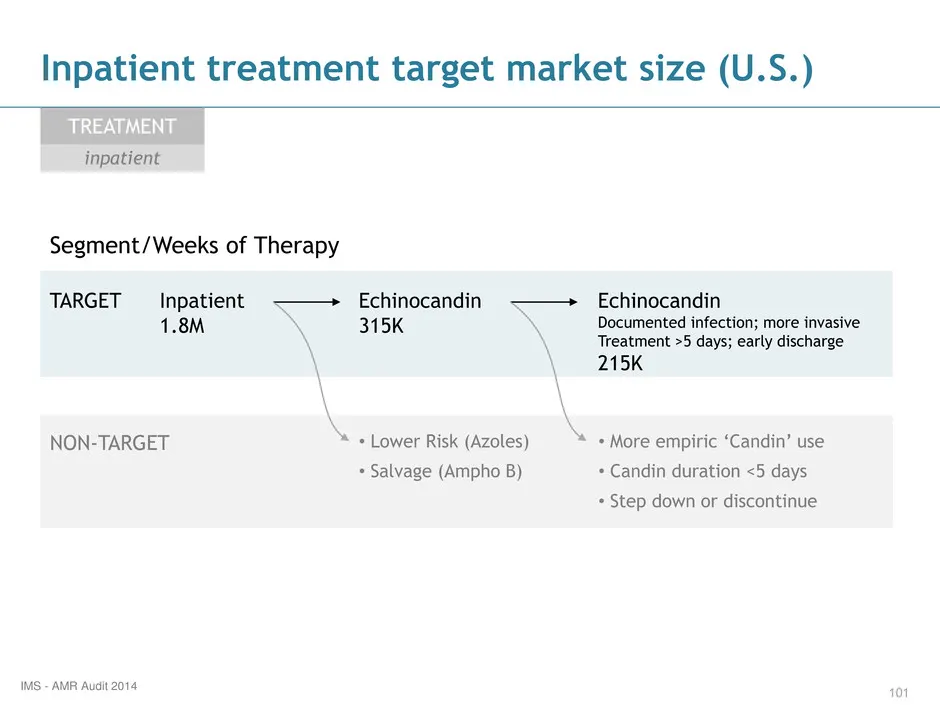
Slide 101: Inpatient treatment target market size
101 inpatient TREATMENT Inpatient 1.8M Echinocandin 315K Echinocandin Documented infection; more invasive Treatment >5 days; early discharge 215K • Lower Risk (Azoles) • Salvage (Ampho B) • More empiric ‘Candin’ use • Candin duration <5 days • Step down or discontinue Segment/Weeks of Therapy IMS -
Slide 102: CD101 is attractive for inpatient treatment
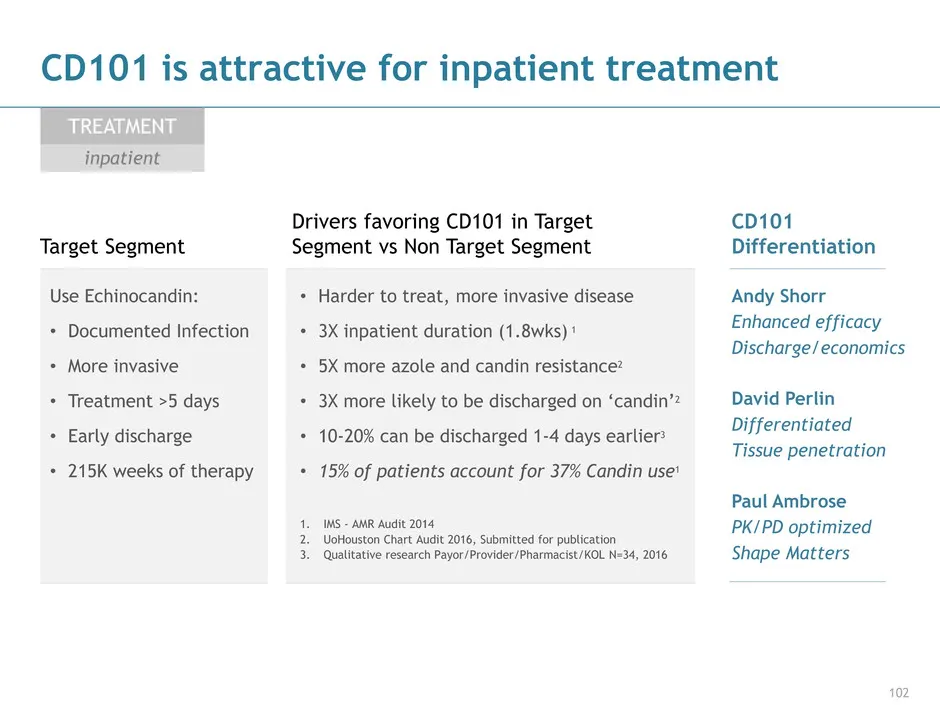
102 inpatient CD101 is attractive for inpatient treatment Use Echinocandin: • Documented Infection • More invasive • Treatment >5 days • Early discharge • 215K weeks of therapy Target Segment • Harder to treat, more invasive disease • 3X inpatient duration (1.8wks) 1 • 5X more azole and candin resis
Slide 103: Treatment: inpatient market example
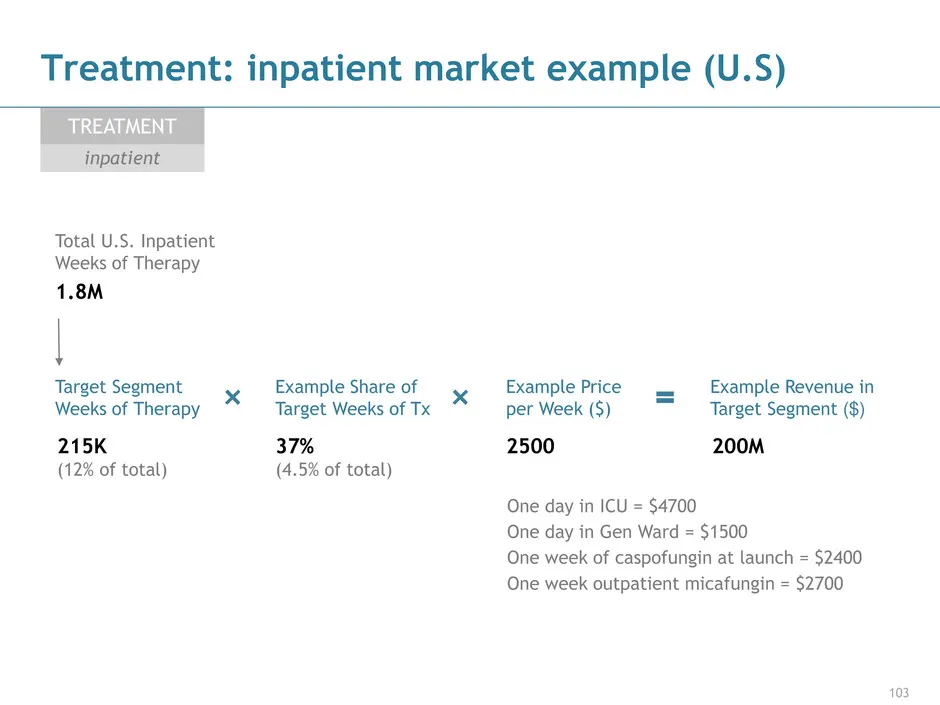
103 inpatient Treatment: inpatient market example (U.S) 1.8M Total U.S. Inpatient Weeks of Therapy Example Share of Target Weeks of Tx 215K (12% of total) 37% (4.5% of total) Target Segment Weeks of Therapy Example Revenue in Target Segment ($) 200M Example Price per Week ($) 2500 One day in ICU = $
Slide 104: Outpatient treatment
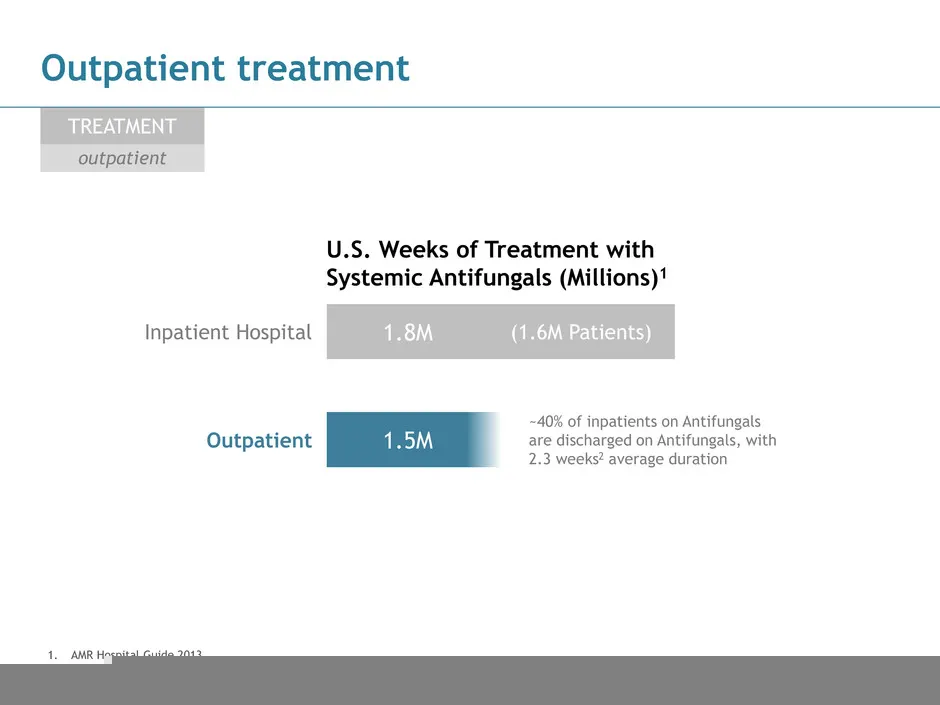
104 outpatient Outpatient treatment TREATMENT Inpatient Hospital Outpatient (1.6M Patients) ~40% of inpatients on Antifungals are discharged on Antifungals, with 2.3 weeks2 average duration 1.8M 1.5M 1. AMR Hospital Guide 2013 2. UoHouston Chart Audit 2016, Submitted for publication U.S. Weeks of Tr
Slide 105: Outpatient treatment target market size
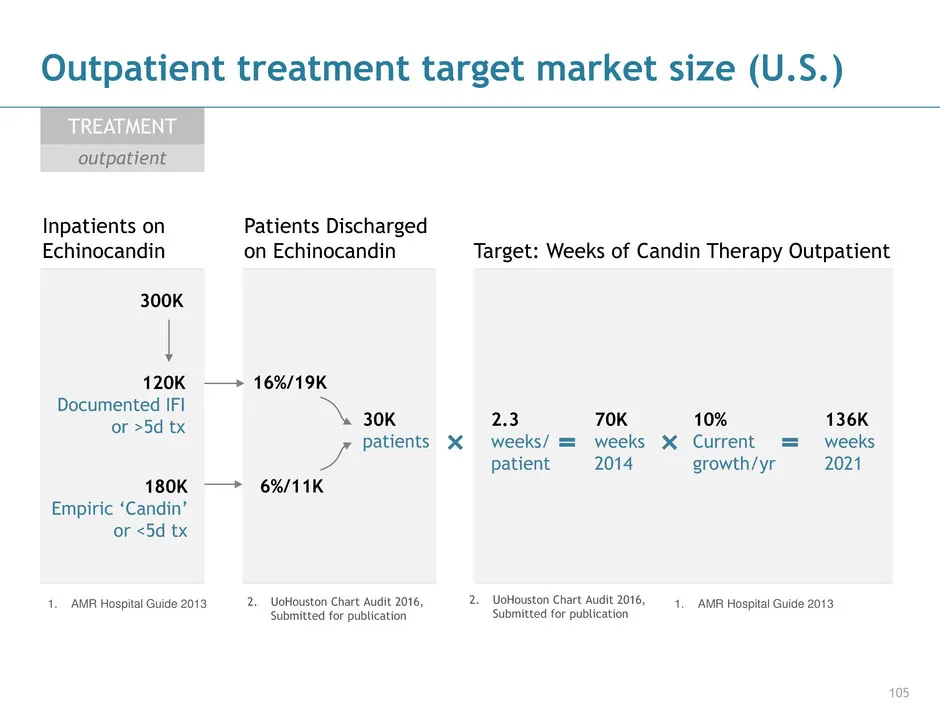
105 Outpatient treatment target market size (U.S.) 120K Documented IFI or >5d tx 180K Empiric ‘Candin’ or <5d tx 6%/11K 16%/19K Patients Discharged on Echinocandin Inpatients on Echinocandin 30K patients Target: Weeks of Candin Therapy Outpatient 136K weeks 2021 10% Current growth/yr 70K weeks 2014

Slide 106: CD101 is attractive for outpatient treatment
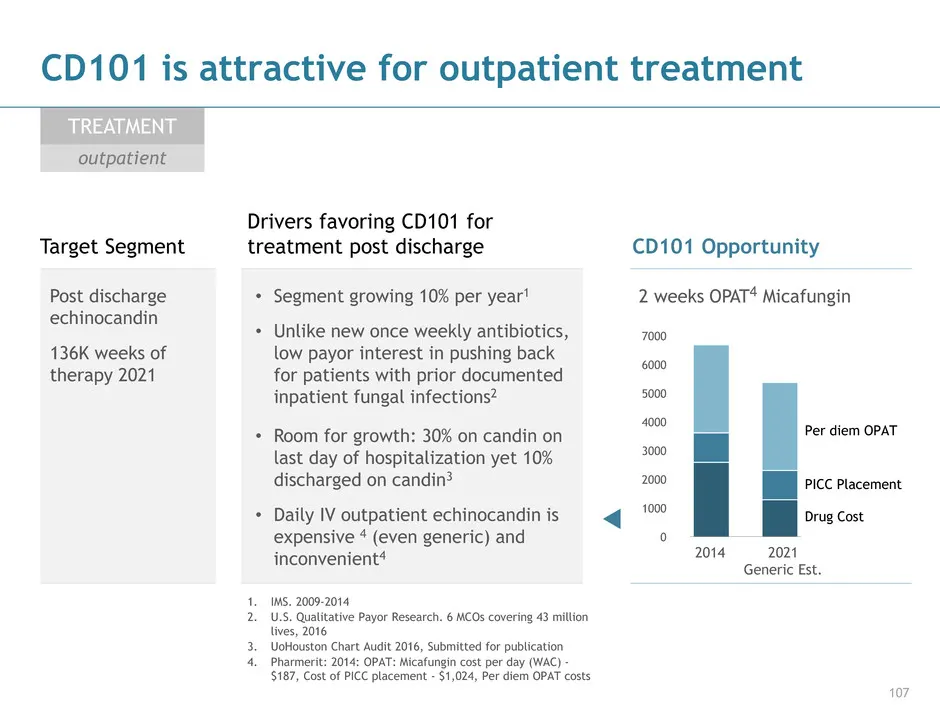
106 outpatient CD101 is attractive for outpatient treatment Post discharge echinocandin 136K weeks of therapy 2021 Target Segment • Segment growing 10% per year1 • Unlike new once weekly antibiotics, low payor interest in pushing back for patients with prior documented inpatient fungal infections2 1
Slide 107: CD101 is attractive for outpatient treatment
107 outpatient CD101 is attractive for outpatient treatment Post discharge echinocandin 136K weeks of therapy 2021 Target Segment • Segment growing 10% per year1 • Unlike new once weekly antibiotics, low payor interest in pushing back for patients with prior documented inpatient fungal infections2 1
Slide 108: Treatment: outpatient market example
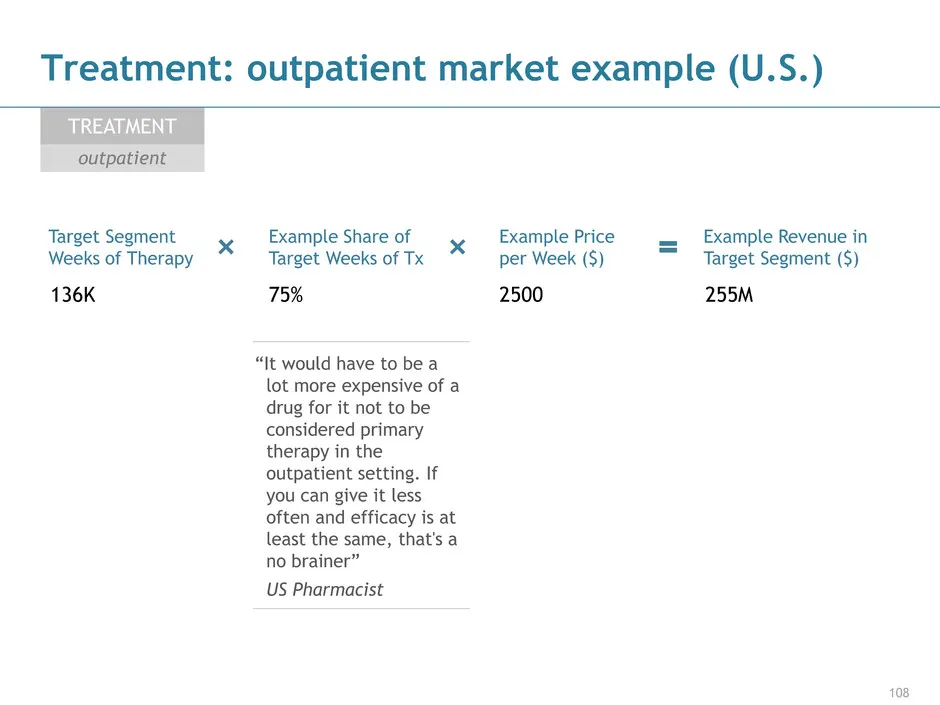
108 Example Share of Target Weeks of Tx 136K 75% Target Segment Weeks of Therapy Example Revenue in Target Segment ($) 255M Example Price per Week ($) 2500 Treatment: outpatient market example (U.S.) outpatient TREATMENT “It would have to be a lot more expensive of a drug for it not to be considered
Slide 109: Prophylaxis: an increasingly important target
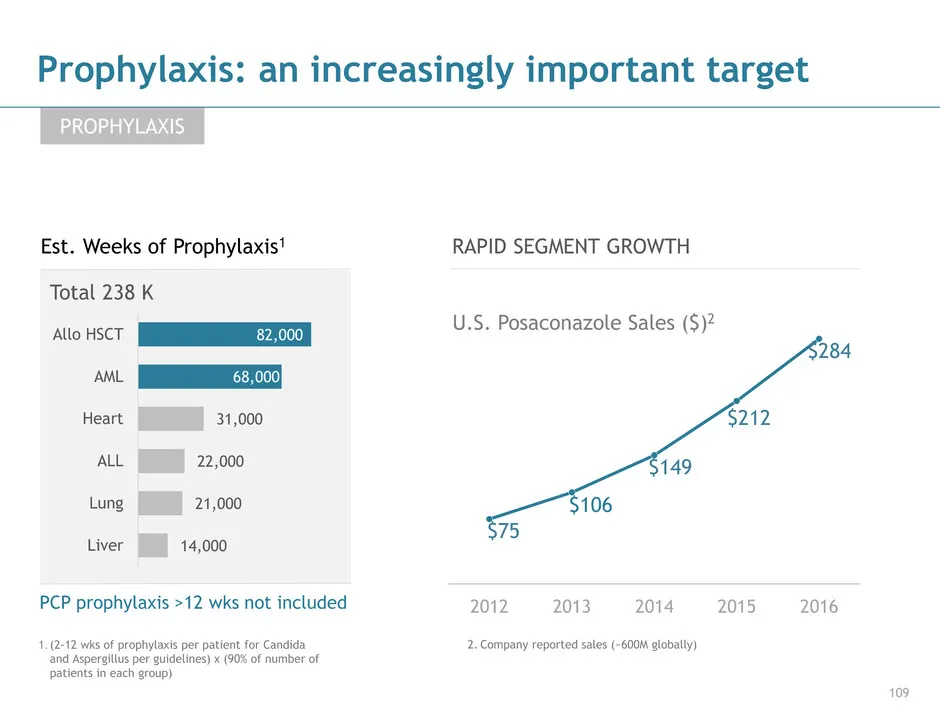
109 PROPHYLAXIS Est. Weeks of Prophylaxis1 14,000 21,000 22,000 31,000 68,000 82,000 Liver Lung ALL Heart AML Allo HSCT Prophylaxis: an increasingly important target 1. (2-12 wks of prophylaxis per patient for Candida and Aspergillus per guidelines) x (90% of number of patients in each group) Total
Slide 110: Prophylaxis market example
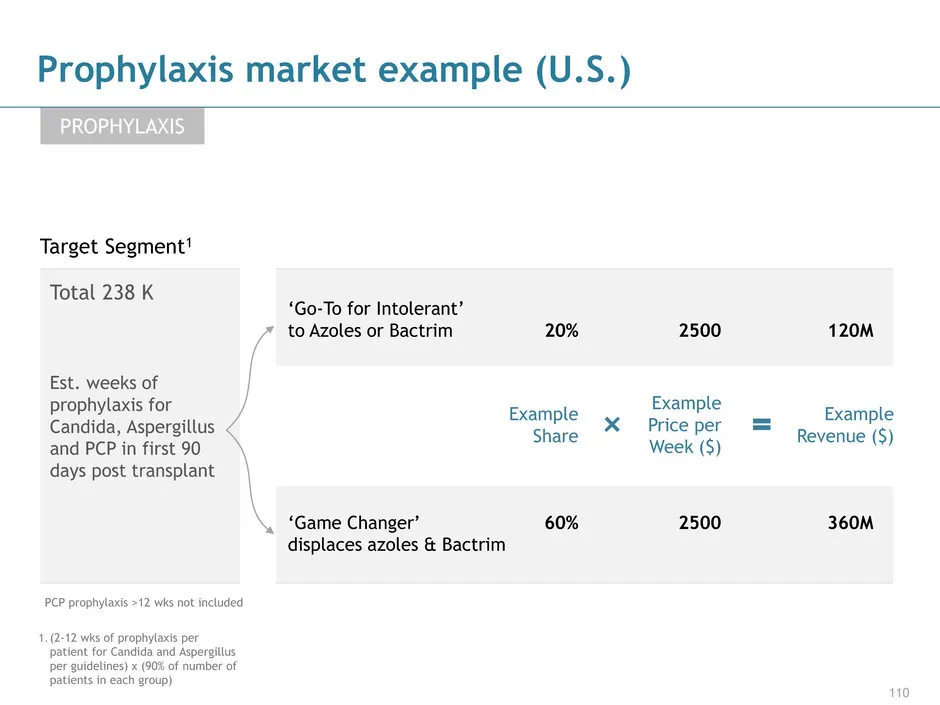
110 Target Segment1 ‘Go-To for Intolerant’ to Azoles or Bactrim Prophylaxis market example (U.S.) Est. weeks of prophylaxis for Candida, Aspergillus and PCP in first 90 days post transplant PROPHYLAXIS Example Share Example Revenue ($) Example Price per Week ($) 20% 2500 120M 1. (2-12 wks of prophyl
Slide 111: CD101: Accessing multiple segments drives value
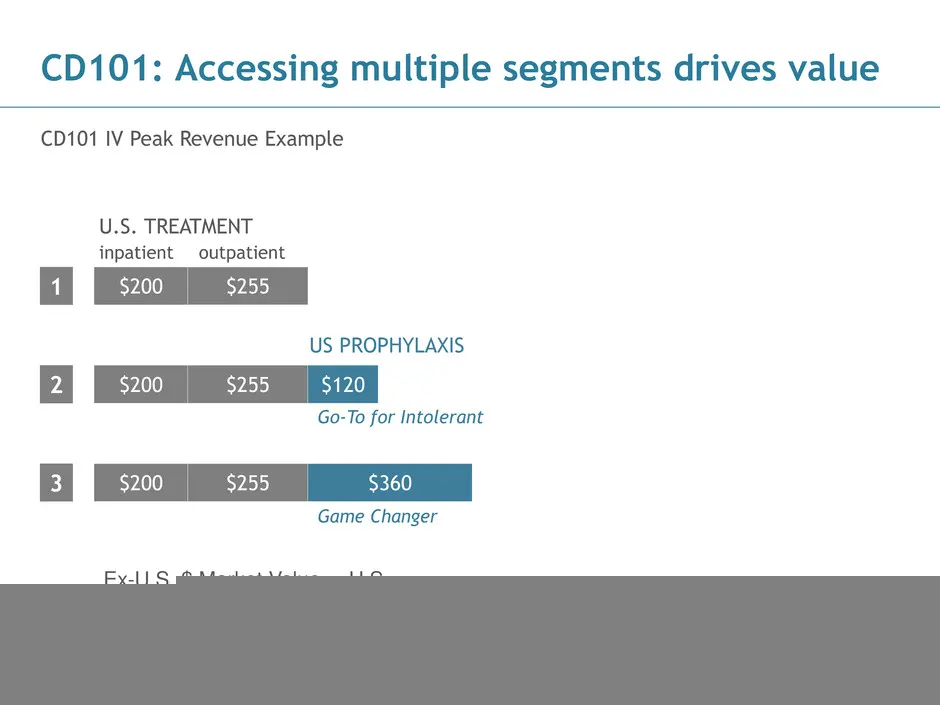
111 CD101: Accessing multiple segments drives value 1 2 3 $200 $255 U.S. TREATMENT inpatient outpatient $200 $255 $360 US PROPHYLAXIS $200 $255 $120 CD101 IV Peak Revenue Example Go-To for Intolerant Game Changer Ex-U.S. $ Market Value ≈ U.S.

Slide 112: Introducing Dr. Cornelius Clancy
112 Introducing Dr. Cornelius Clancy Cornelius J. Clancy, M.D. VA Pittsburgh Healthcare System, University of Pittsburgh Medical Center

Slide 113: Unmet needs in treating antibiotic-resistant Gram negative infections
Unmet needs in treating antibiotic-resistant Gram negative bacterial infections Cornelius J. Clancy, M.D. VA Pittsburgh Healthcare System University of Pittsburgh Medical Center 113
Slide 114: Antibiotic resistance is a problem at UPMC
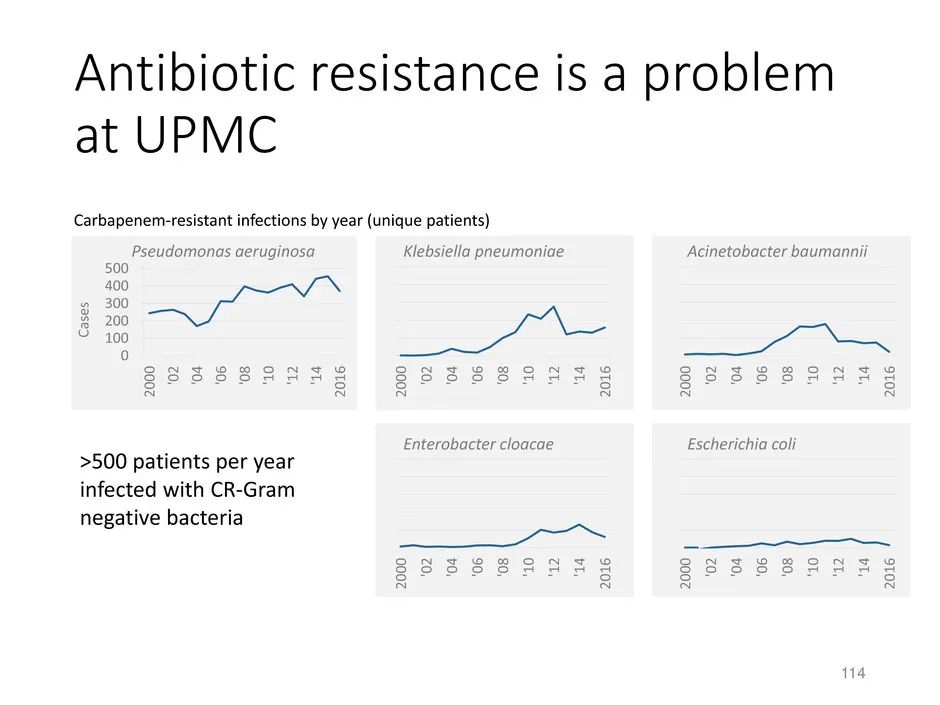
Antibiotic resistance is a problem at UPMC 0 100 200 300 400 500 2 0 0 0 '0 2 '0 4 '0 6 '0 8 '1 0 '1 2 '1 4 2 0 1 6 2 0 0 0 '0 2 '0 4 '0 6 '0 8 '1 0 '1 2 '1 4 2 0 1 6 2 0 0 0 '0 2 '0 4 '0 6 '0 8 '1 0 '1 2 '1 4 2 0 1 6 2 0 0 0 '0 2 '0 4 '0 6 '0 8 '1 0 '1 2 '1 4 2 0 1 6 2 0 0 0 '0 2 '0 4 '0 6 '0 8 '1
Slide 115: Antibiotic resistance is highly dynamic
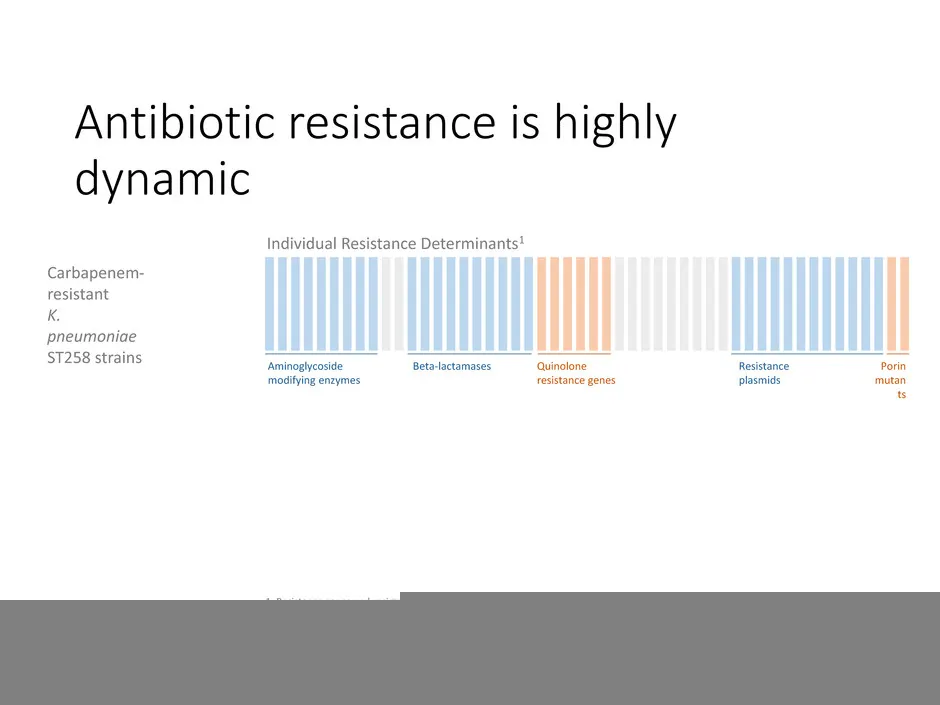
Antibiotic resistance is highly dynamic Individual Resistance Determinants1 Carbapenem- resistant K. pneumoniae ST258 strains 1. Resistance genes and resistance-bearing plasmids (n=50 genetic determinants) Aminoglycoside modifying enzymes Beta-lactamases Quinolone resistance genes Resistance plasmid
Slide 116: Antibiotic resistance is highly dynamic
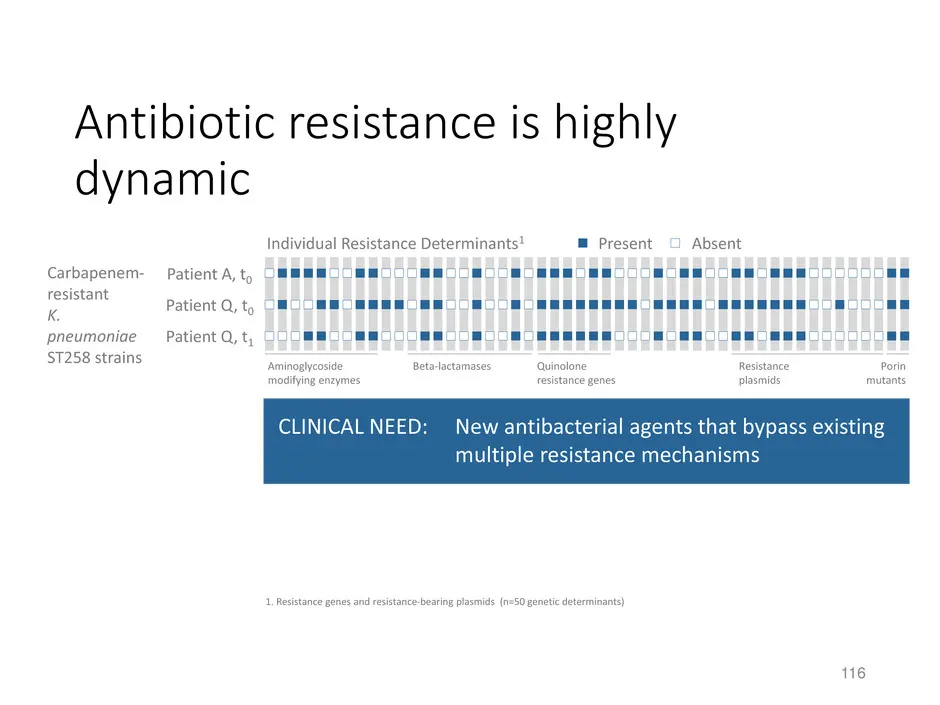
Antibiotic resistance is highly dynamic Individual Resistance Determinants1 Carbapenem- resistant K. pneumoniae ST258 strains Patient A, t0 Patient Q, t0 Patient Q, t1 Present Absent 1. Resistance genes and resistance-bearing plasmids (n=50 genetic determinants) Aminoglycoside modifying enzymes Beta

Slide 117: Our last line of defense is being breached
Sources: Liu YY et al. Lancet Infect Dis. 2016 Feb;16(2):161-8. Du H Lancet Infect Dis. 2016 Jan 29. Yao X et al. Lancet Infect Dis. 2016 Jan 29, Bloomberg. AAC 2016 May 26 online; doi:10.1128/AAC.01103-16 Nov Q1 2015 2016 Mcr-1 resistance plasmid found in carbapenem-resistant Enterobacteriaceae Mcr
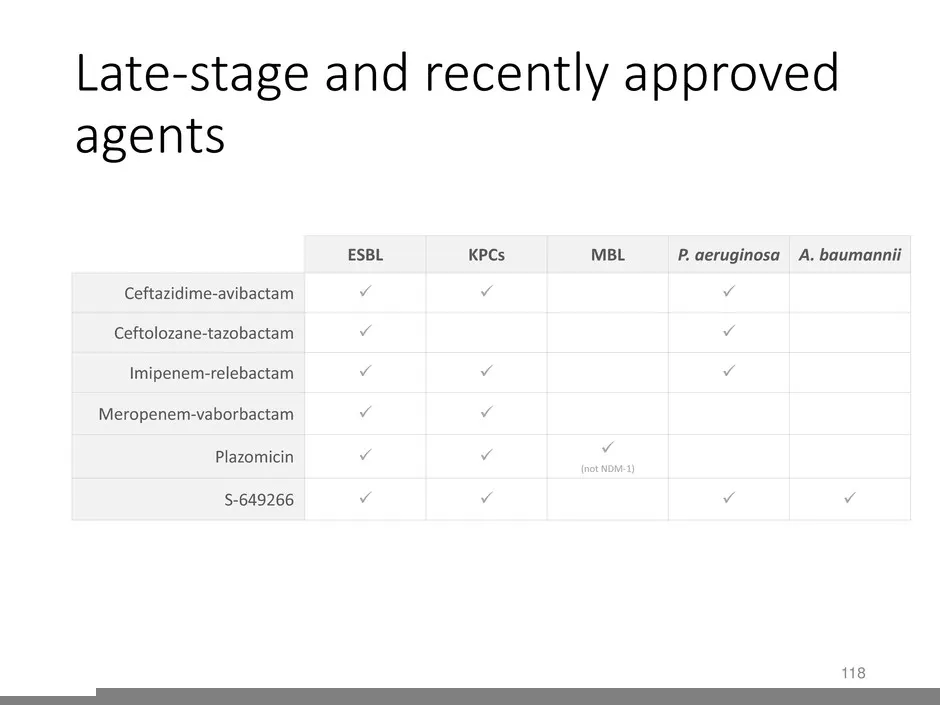
Slide 118: Late-stage and recently approved agents
Late-stage and recently approved agents ESBL KPCs MBL P. aeruginosa A. baumannii Ceftazidime-avibactam Ceftolozane-tazobactam Imipenem-relebactam Meropenem-vaborbactam Plazomicin (not NDM-1) S-649266 118
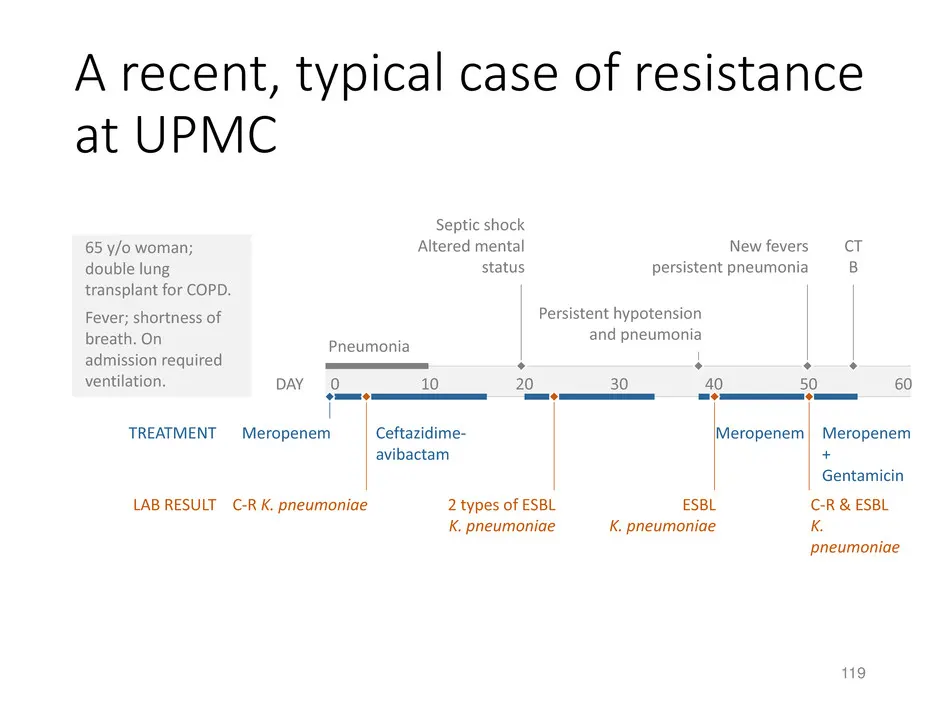
Slide 119: A recent, typical case of resistance at UPMC
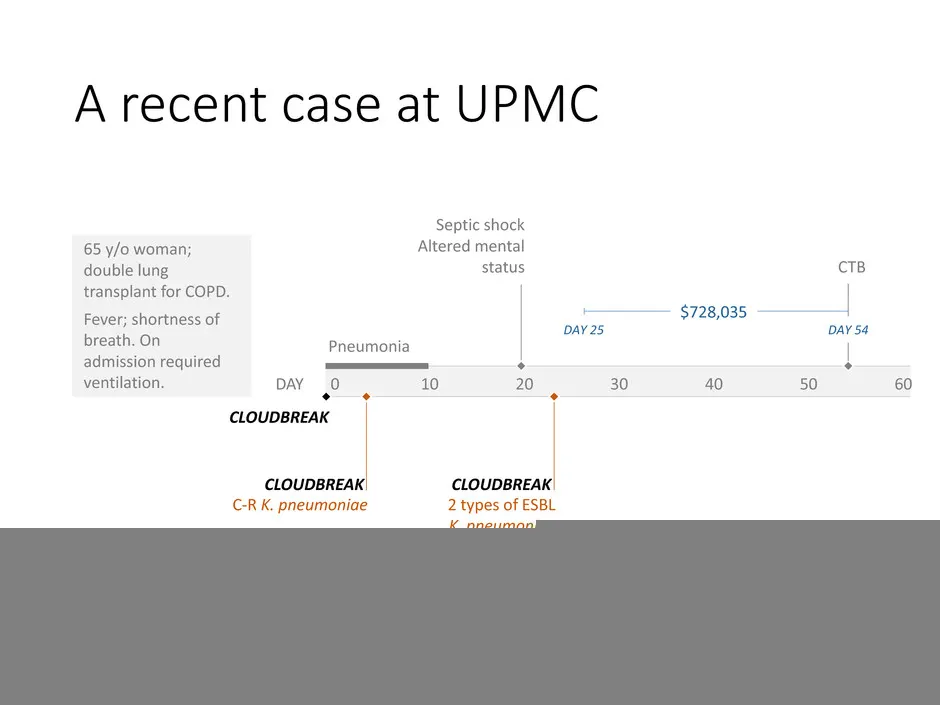
A recent, typical case of resistance at UPMC 65 y/o woman; double lung transplant for COPD. Fever; shortness of breath. On admission required ventilation. 0 10 20 30 40 50 60DAY Pneumonia Meropenem Septic shock Altered mental status C-R K. pneumoniae TREATMENT LAB RESULT Ceftazidime- avibactam 2 typ
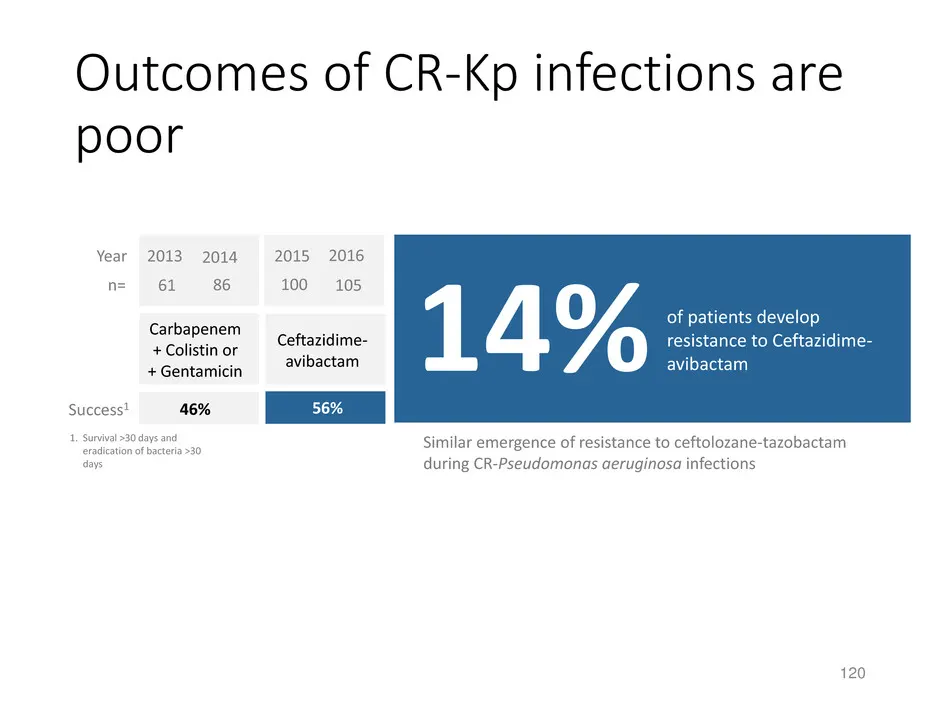
Slide 120: Outcomes of CR-Kp infections are poor
Outcomes of CR-Kp infections are poor 2013 2014 2015 2016 n= 61 86 100 105 Carbapenem + Colistin or + Gentamicin 46% Ceftazidime- avibactam 56% Year of patients develop resistance to Ceftazidime- avibactam 14% Success1 1. Survival >30 days and eradication of bacteria >30 days Similar emergence of re
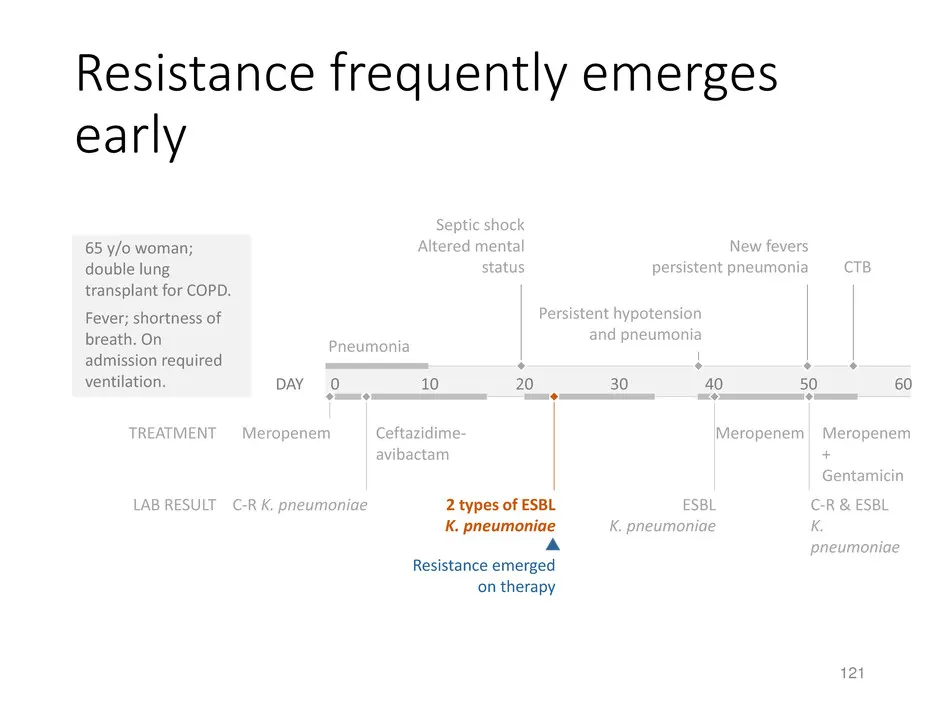
Slide 121: Resistance frequently emerges early
Resistance frequently emerges early 65 y/o woman; double lung transplant for COPD. Fever; shortness of breath. On admission required ventilation. 0 10 20 30 40 50 60DAY Pneumonia Meropenem Septic shock Altered mental status C-R K. pneumoniae TREATMENT LAB RESULT Ceftazidime- avibactam 2 types of ESB
Slide 122: Cases of Ceftazidime-avibactam resistance
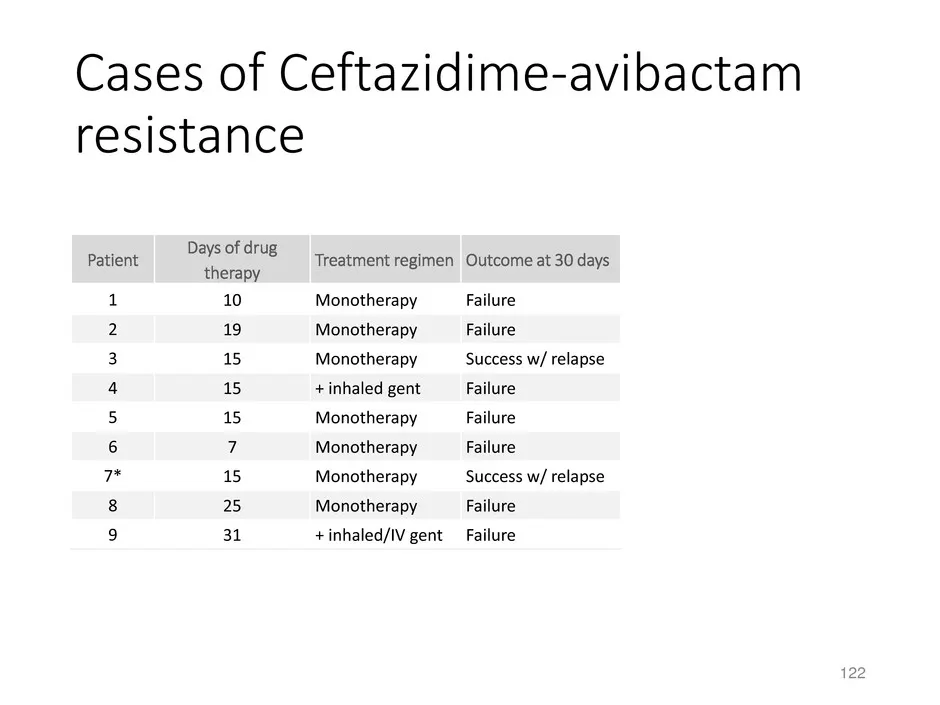
Cases of Ceftazidime-avibactam resistance Patient Days of drug therapy Treatment regimen Outcome at 30 days 1 10 Monotherapy Failure 2 19 Monotherapy Failure 3 15 Monotherapy Success w/ relapse 4 15 + inhaled gent Failure 5 15 Monotherapy Failure 6 7 Monotherapy Failure 7* 15 Monotherapy Success w/

Slide 123: Cases of Ceftazidime-avibactam resistance
Cases of Ceftazidime-avibactam resistance Patient Days of drug therapy Treatment regimen Outcome at 30 days 1 10 Monotherapy Failure 2 19 Monotherapy Failure 3 15 Monotherapy Success w/ relapse 4 15 + inhaled gent Failure 5 15 Monotherapy Failure 6 7 Monotherapy Failure 7* 15 Monotherapy Success w/

Slide 124: Where are we at UPMC?
Where are we at UPMC? • Highly-resistant Gram negative pathogens are firmly entrenched • New agents in the pipeline are not the answer • We advocate combination antibiotic therapy to try to achieve synergy and limit resistance 124

Slide 125: We need new antibiotics
new antibioticsWe need 125

Slide 126: We need a new paradigm
paradigmnewWe need a 126

Slide 127: Cloudbreak: Multi-modal mechanism
paradigmnewWe need a Cloudbreak • Direct activity and broader range • Synergy with SOC • Immune augmentation • Hard to treat pathogens • Combination Rx • Activating host defenses, even in transplant recipients Multi-modal mechanism Promising Clinical Utility 127
Slide 128: A recent case at UPMC
A recent case at UPMC 65 y/o woman; double lung transplant for COPD. Fever; shortness of breath. On admission required ventilation. 0 10 20 30 40 50 60DAY Pneumonia Septic shock Altered mental status C-R K. pneumoniae 2 types of ESBL K. pneumoniae CTB CLOUDBREAK CLOUDBREAK CLOUDBREAK $728,035 DAY 25

Slide 129: Conclusions
Conclusions Cloudbreak™ is potentially a major step forward in treating patients with highly resistant Gram negative infections • Broad spectrum activity • Novel, multi-modality treatment paradigms • Conceptual advance by incorporating native host defenses into treatment 129

Slide 130: Introducing Dr. Kevin Forrest
130 Introducing Dr. Kevin Forrest Chief Strategy Officer, Cidara Therapeutics

Slide 131: Platform Overview
Platform Overview Cloudbreak Antifungal Update Future platform expansion Antibacterial Update
Slide 132: Cloudbreak: antimicrobial immunotherapy
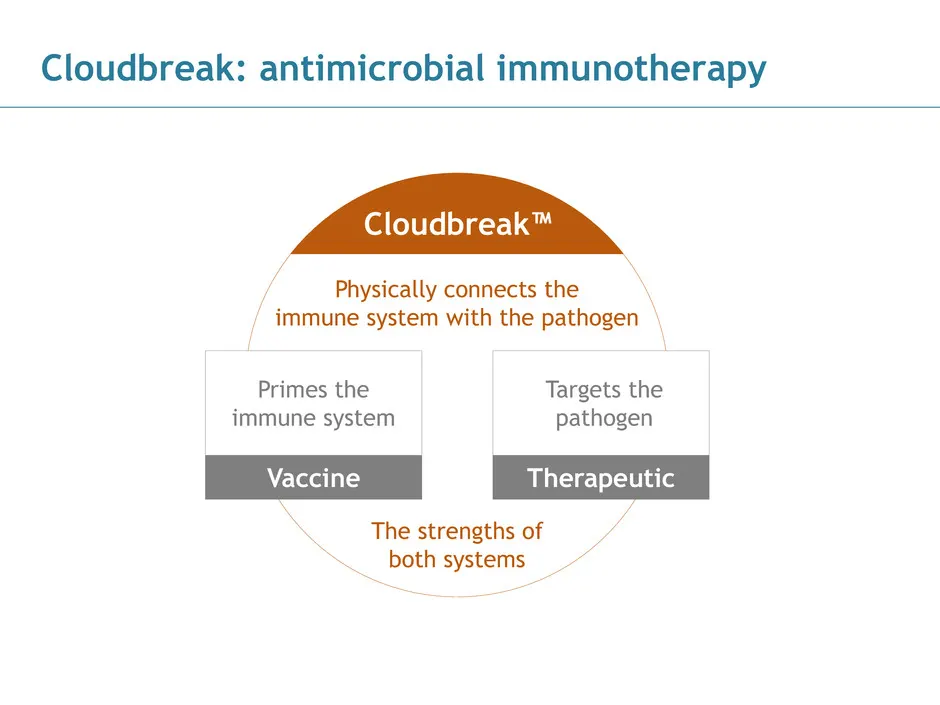
132 Physically connects the immune system with the pathogen Vaccine Primes the immune system Therapeutic Targets the pathogen The strengths of both systems Cloudbreak™ Cloudbreak: antimicrobial immunotherapy
Slide 133: Cloudbreak: inspired by cancer immunotherapy
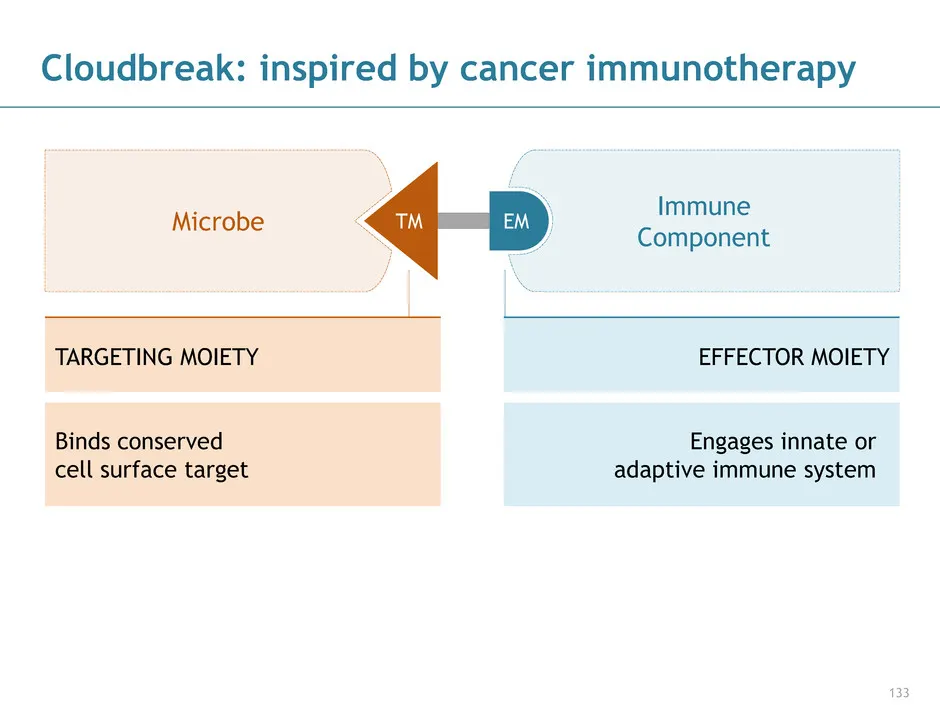
133 Cloudbreak: inspired by cancer immunotherapy Binds conserved cell surface target Engages innate or adaptive immune system TARGETING MOIETY Microbe Immune Component TM EM EFFECTOR MOIETY

Slide 134: Cloudbreak IP
134 Cloudbreak IP Methods of use + Composition of matter Novel Targeting Moieties Novel TM/EM combos Ability to target specific pathogens and engage immune system Additional filings underway Know-how (positive and negative approaches)

Slide 135: Cloudbreak Antibacterial Update
Platform Overview Cloudbreak Antifungal Update Future platform expansion Antibacterial Update
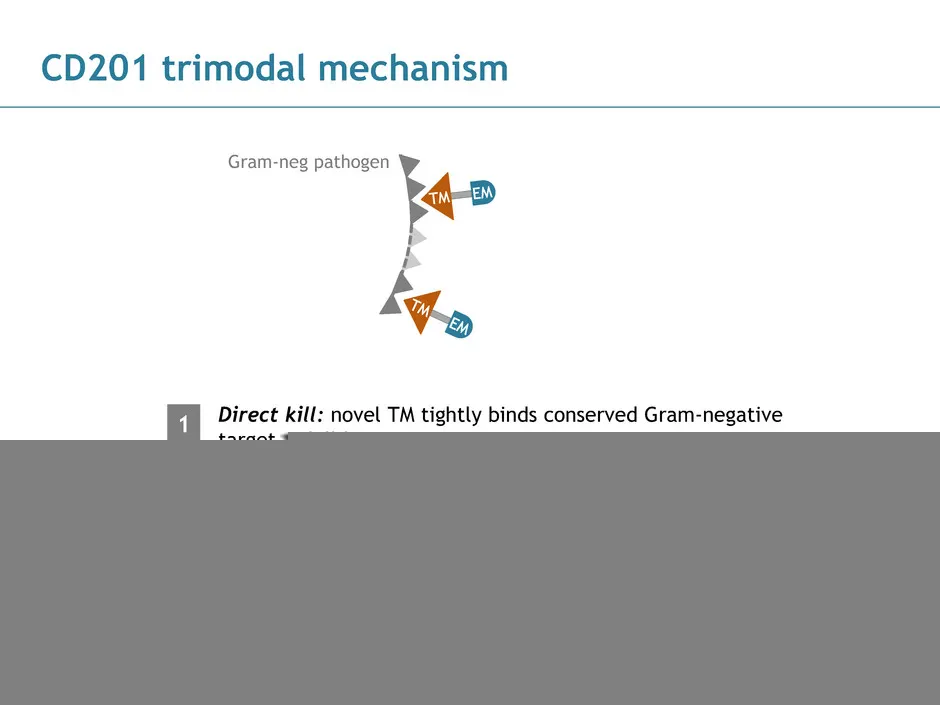
Slide 136: CD201 trimodal mechanism
136 CD201 trimodal mechanism Direct kill: novel TM tightly binds conserved Gram-negative target to kill bacteria Gram-neg pathogen 1
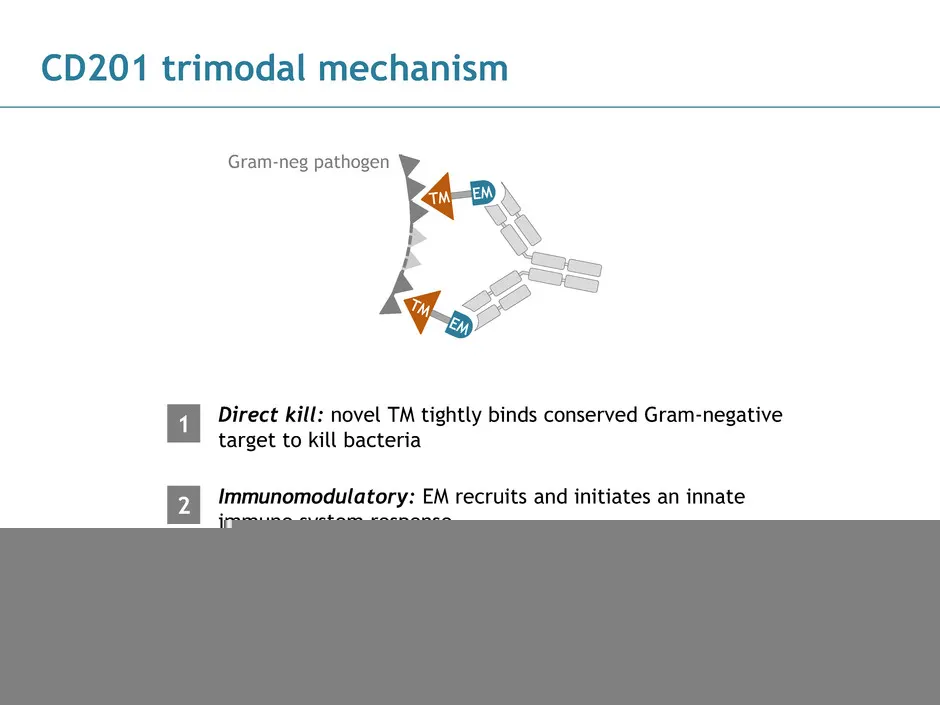
Slide 137: CD201 trimodal mechanism
137 CD201 trimodal mechanism Direct kill: novel TM tightly binds conserved Gram-negative target to kill bacteria Gram-neg pathogen Immunomodulatory: EM recruits and initiates an innate immune system response 1 2
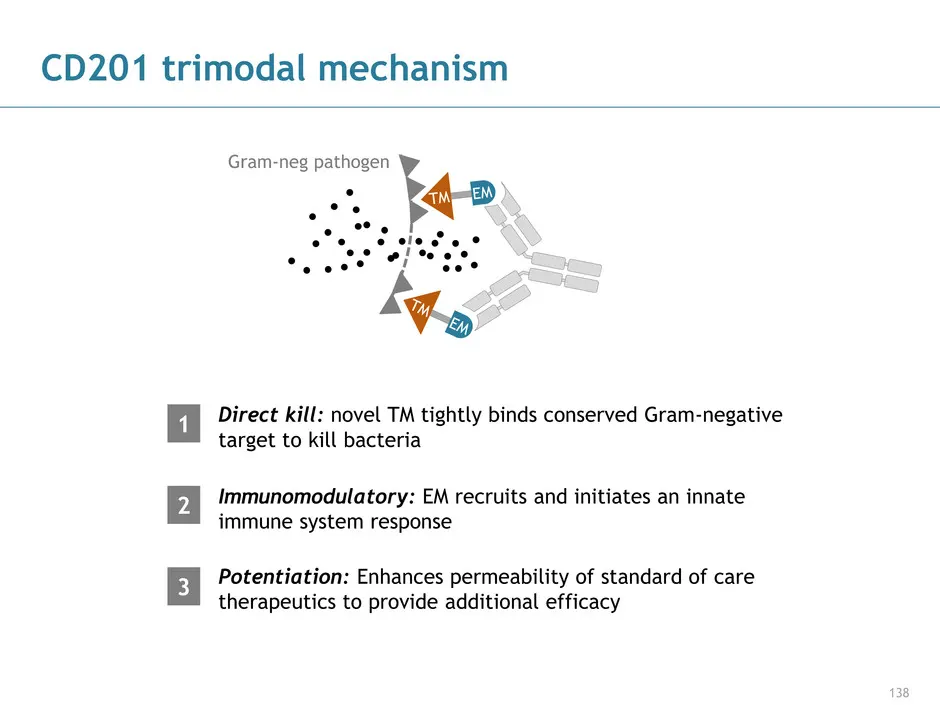
Slide 138: CD201 trimodal mechanism
138 CD201 trimodal mechanism Direct kill: novel TM tightly binds conserved Gram-negative target to kill bacteria Gram-neg pathogen Immunomodulatory: EM recruits and initiates an innate immune system response 1 2 Potentiation: Enhances permeability of standard of care therapeutics to provide addition
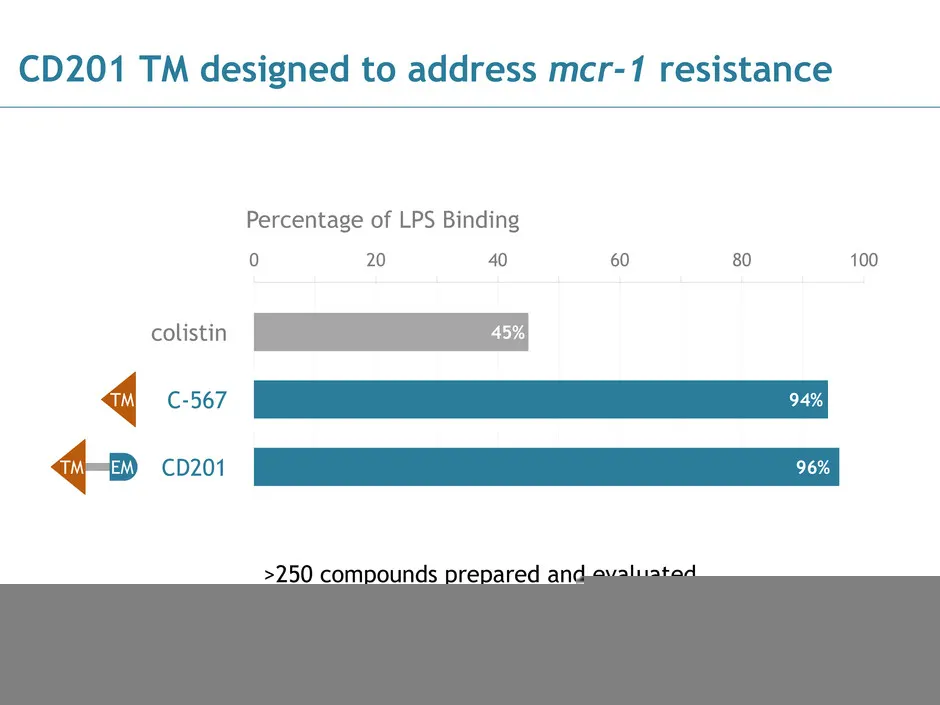
Slide 139: CD201 TM designed to address mcr-1 resistance
139 CD201 TM designed to address mcr-1 resistance colistin C-567 CD201 Percentage of LPS Binding >250 compounds prepared and evaluated 0 20 40 60 80 100 45% 94% 96%TM EM TM
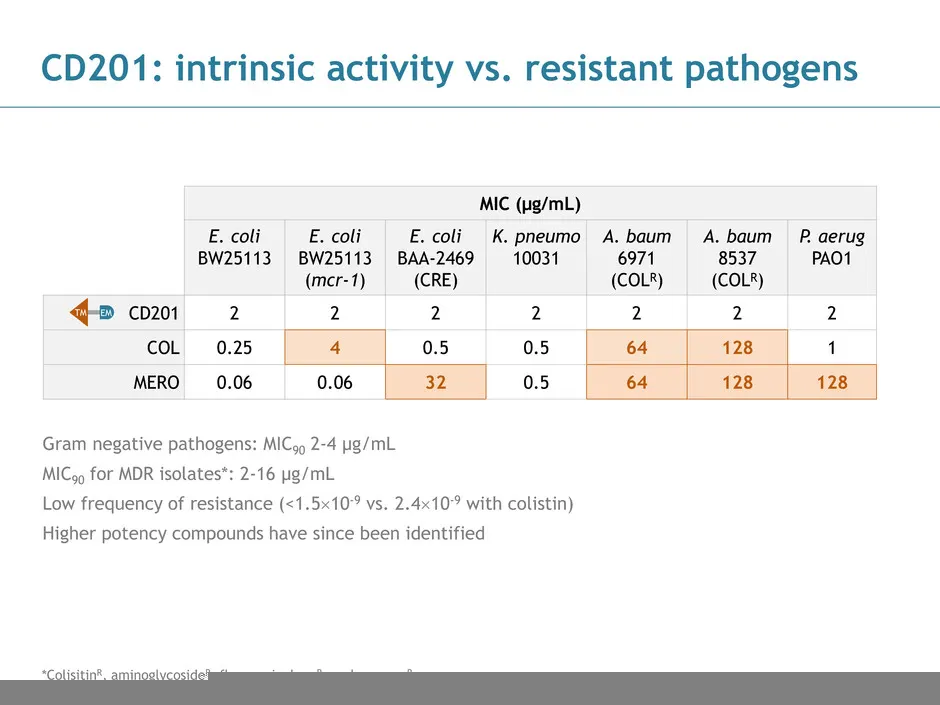
Slide 140: CD201: intrinsic activity vs. resistant pathogens
140 CD201: intrinsic activity vs. resistant pathogens Gram negative pathogens: MIC90 2-4 µg/mL MIC90 for MDR isolates*: 2-16 µg/mL Low frequency of resistance (<1.510-9 vs. 2.410-9 with colistin) Higher potency compounds have since been identified MIC (µg/mL) E. coli BW25113 E. coli BW25113 (mcr-1
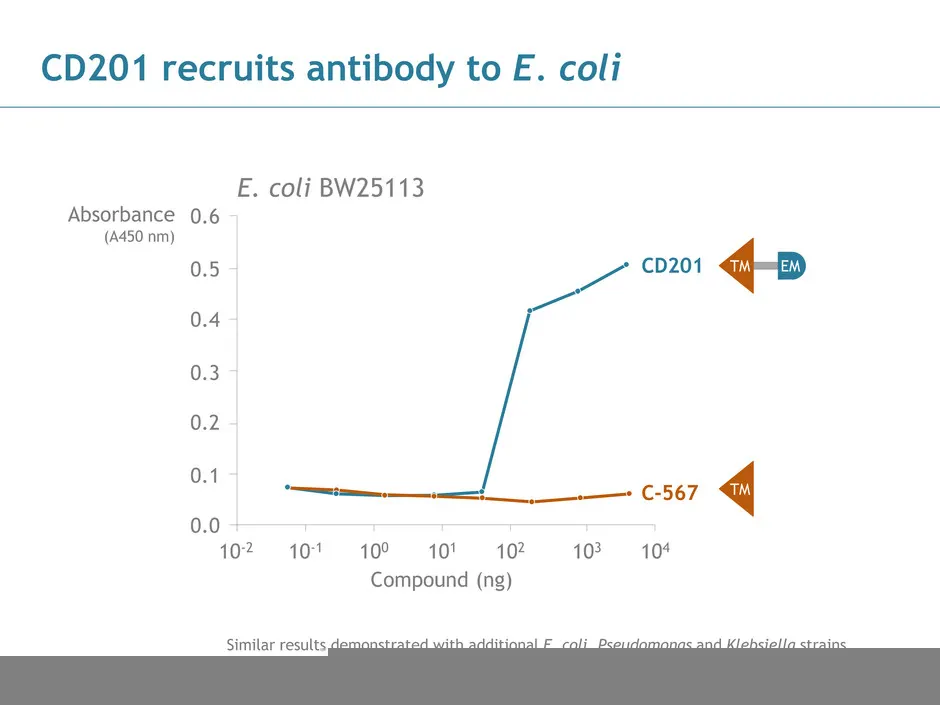
Slide 141: CD201 recruits antibody to E. coli
141 CD201 recruits antibody to E. coli 0.6 0.5 0.4 0.3 0.2 0.1 0.0 10-2 10-1 100 101 102 103 104 Compound (ng) Absorbance (A450 nm) C-567 CD201 TM EM TM Similar results demonstrated with additional E. coli, Pseudomonas and Klebsiella strains E. coli BW25113
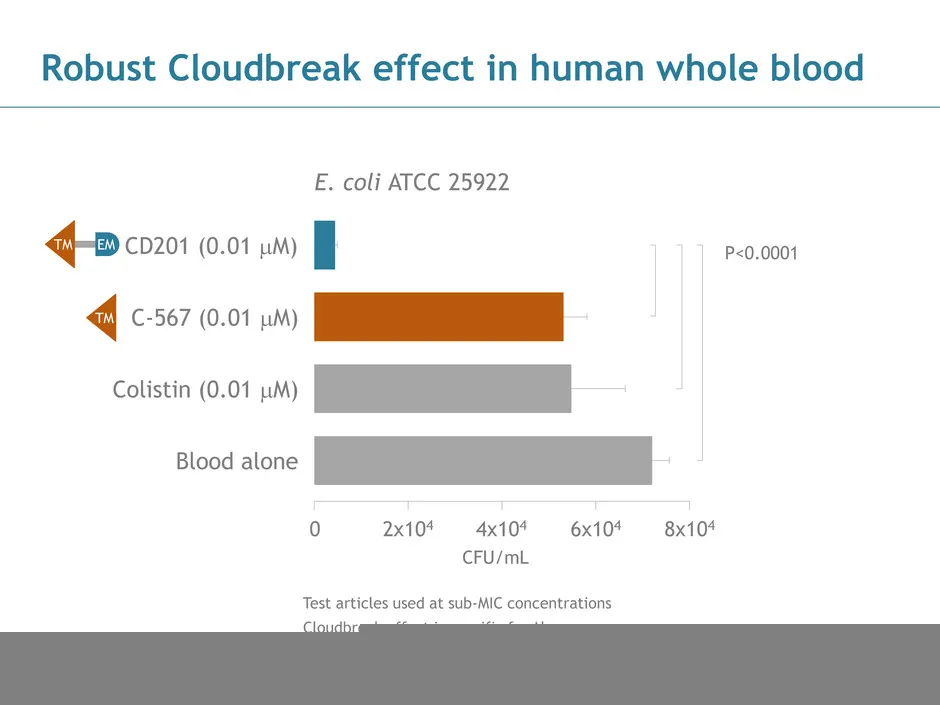
Slide 142: Robust Cloudbreak effect in human whole blood
142 Robust Cloudbreak effect in human whole blood Test articles used at sub-MIC concentrations E. coli ATCC 25922 0 2x10⁴ 4x10⁴ 6x10⁴ 8x10⁴ CD201 (0.01 M) C-567 (0.01 M) Colistin (0.01 M) Blood alone TM EM TM P<0.0001 CFU/mL Cloudbreak effect is specific for Ab
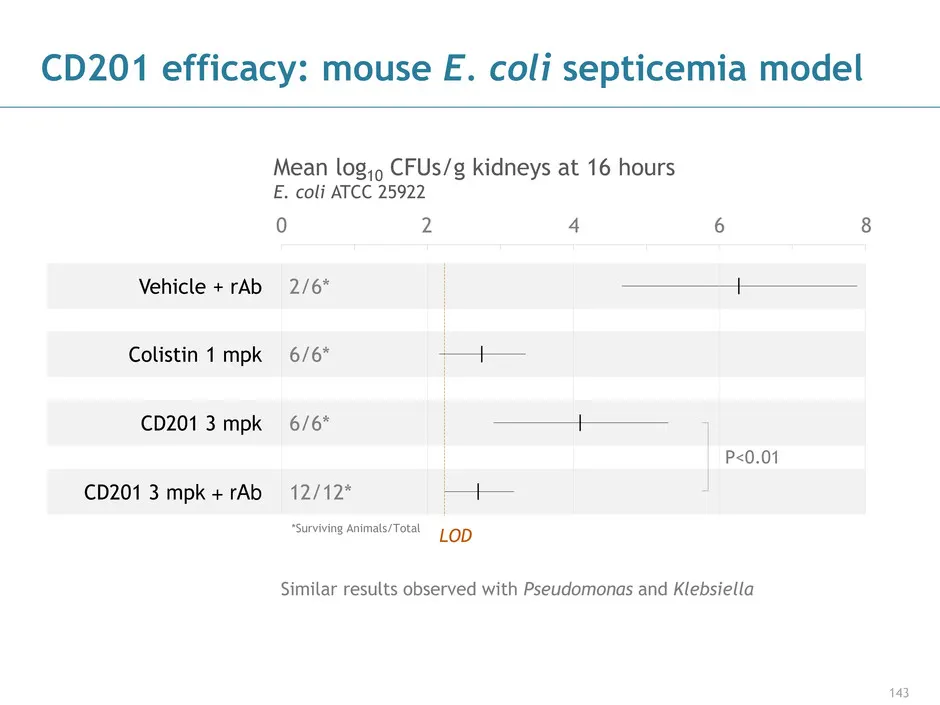
Slide 143: CD201 efficacy: mouse E. coli septicemia model
143 CD201 efficacy: mouse E. coli septicemia model Mean log10 CFUs/g kidneys at 16 hours E. coli ATCC 25922 P<0.01 LOD Vehicle + rAb Colistin 1 mpk CD201 3 mpk CD201 3 mpk + rAb 0 2 4 6 8 Similar results observed with Pseudomonas and Klebsiella 2/6* 6/6* 6/6* 12/12* *Surviving Animals/Total
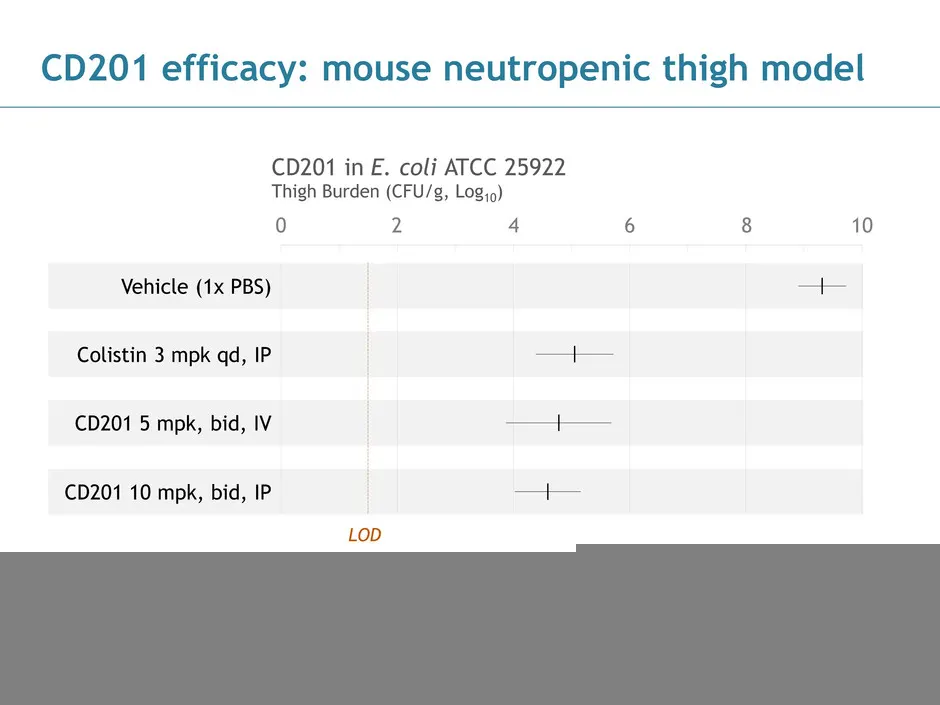
Slide 144: CD201 efficacy: mouse neutropenic thigh model
144 CD201 in E. coli ATCC 25922 CD201 efficacy: mouse neutropenic thigh model Thigh Burden (CFU/g, Log10) Vehicle (1x PBS) Colistin 3 mpk qd, IP CD201 5 mpk, bid, IV CD201 10 mpk, bid, IP 0 2 4 6 8 10 LOD

Slide 145: CARB-X partnership accelerates CD201
145 CARB-X partnership accelerates CD201

Slide 146: CD201 next steps
146 CD201 next steps Continue to build in vivo safety and efficacy profile in vivo lung efficacy in process multi-species in vivo safety in process Advance IND-enabling studies Continue to advance backup TM/EM conjugates Present additional details at upcoming conferences

Slide 147: Cloudbreak Antifungal Update
Platform Overview Cloudbreak Antifungal Update Future platform expansion Antibacterial Update

Slide 148: C-403 Cloudbreak antifungal
148 C-403 cloudbreak antifungal Direct kill: novel TM tightly binds conserved Gram-negative target to kill bacteria Yeast/Mould Immunomodulatory: EM recruits and initiates an innate immune system response 1 2
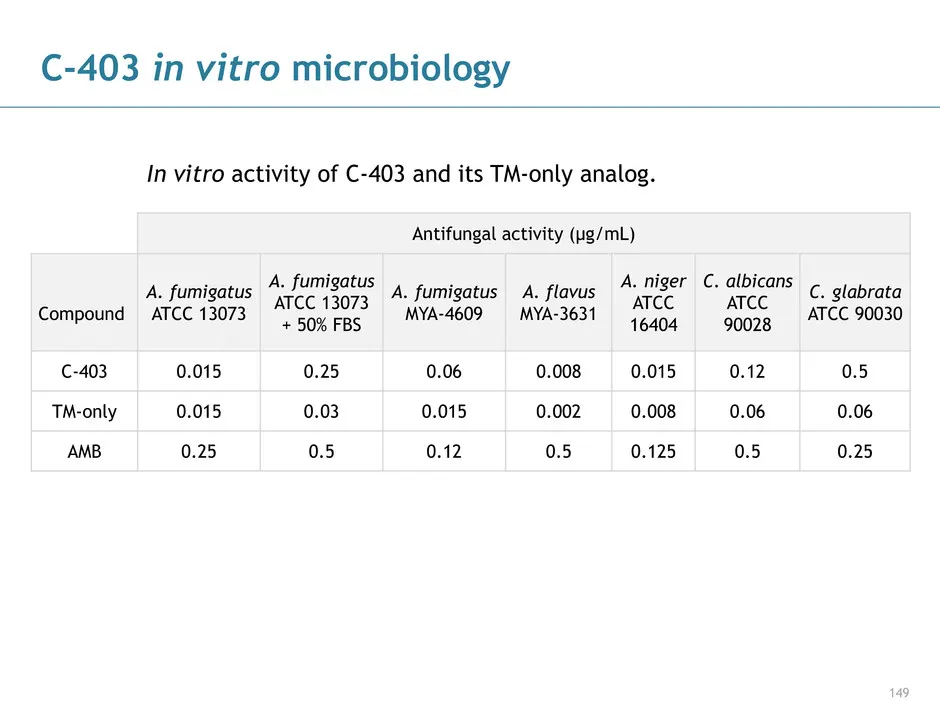
Slide 149: C-403 in vitro microbiology
149 C-403 in vitro microbiology Antifungal activity (µg/mL) Compound A. fumigatus ATCC 13073 A. fumigatus ATCC 13073 + 50% FBS A. fumigatus MYA-4609 A. flavus MYA-3631 A. niger ATCC 16404 C. albicans ATCC 90028 C. glabrata ATCC 90030 C-403 0.015 0.25 0.06 0.008 0.015 0.12 0.5 TM-only 0.015 0.03 0.01
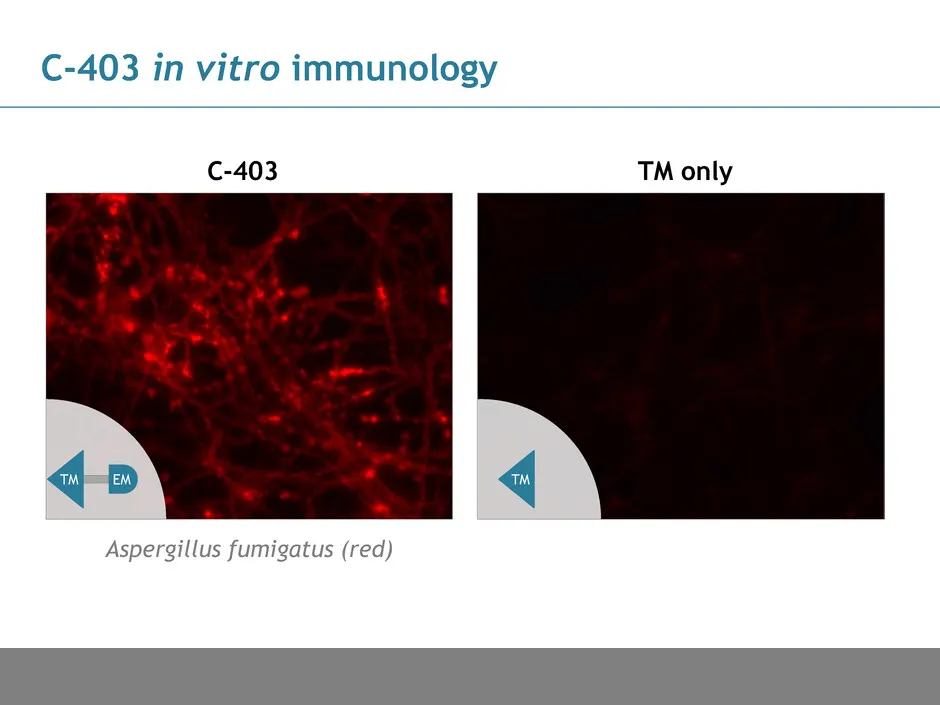
Slide 150: C-403 in vitro immunology
150 C-403 in vitro immunology TM onlyC-403 TMTM EM Aspergillus fumigatus (red)
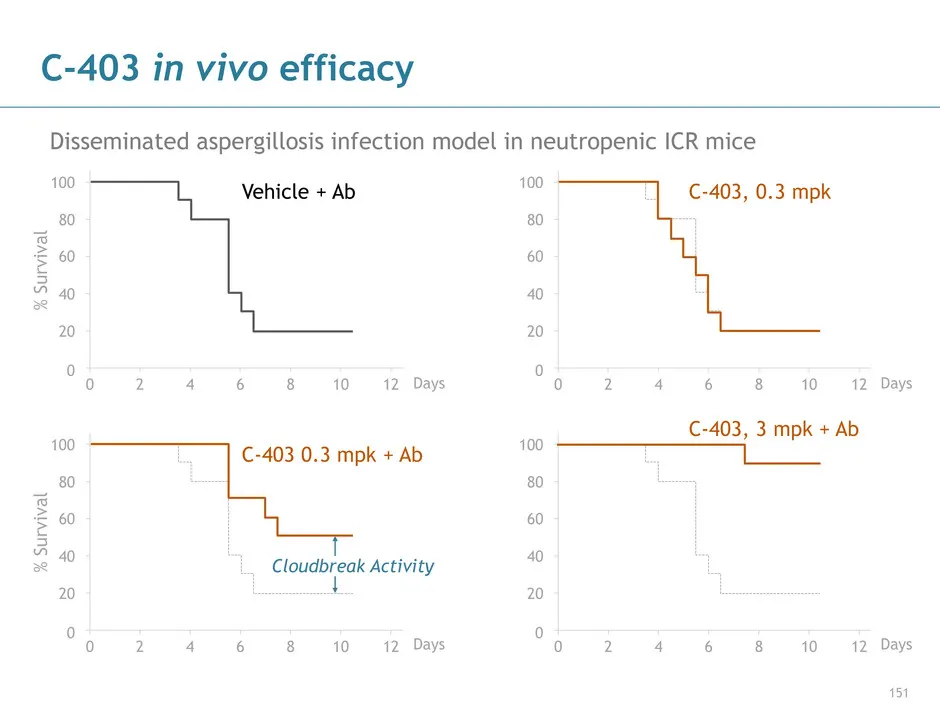
Slide 151: C-403 in vivo efficacy
151 C-403 in vivo efficacy 100 80 60 40 20 0 0 2 4 6 8 10 12 100 80 60 40 20 0 0 2 4 6 8 10 12 100 80 60 40 20 0 0 2 4 6 8 10 12 100 80 60 40 20 0 0 2 4 6 8 10 12 Days Days Days Days Vehicle + Ab C-403, 0.3 mpk C-403 0.3 mpk + Ab C-403, 3 mpk + Ab Cloudbreak Activity % Su rv iv a l % Su rv iv a l Di

Slide 152: C-403 Next steps
152 C-403 Next steps Continue to build out in vivo and ex vivo efficacy and safety Evaluate for potential life cycle management of CD101

Slide 153: Future platform expansion
Platform Overview Cloudbreak Antifungal Update Future platform expansion Antibacterial Update
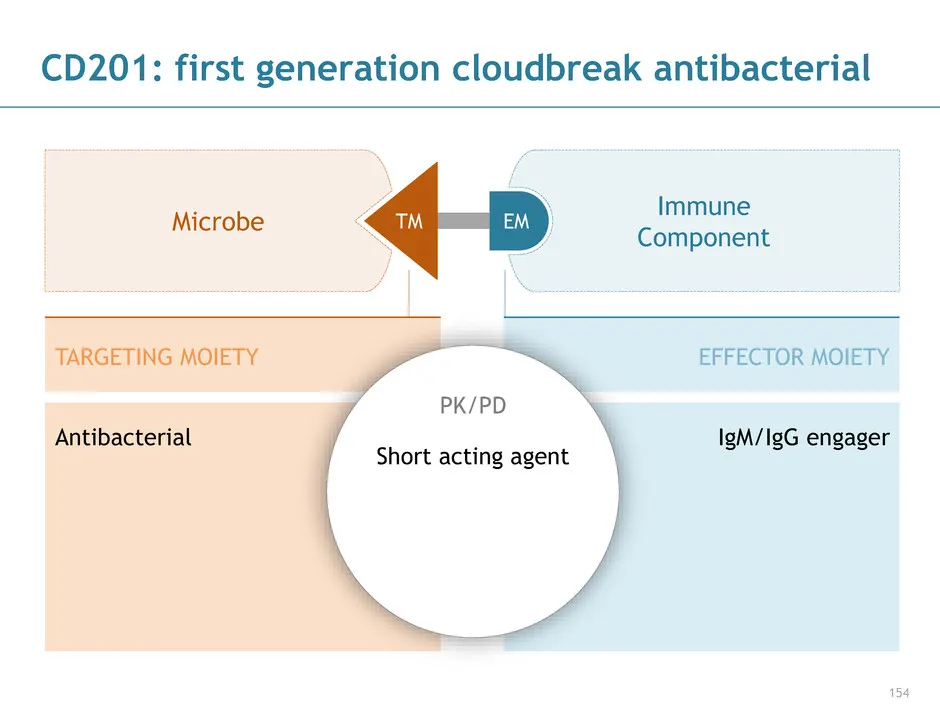
Slide 154: CD201: first generation Cloudbreak antibacterial
154 EFFECTOR MOIETYTARGETING MOIETY Microbe Immune Component TM EM Antibacterial IgM/IgG engager Short acting agent PK/PD CD201: first generation cloudbreak antibacterial
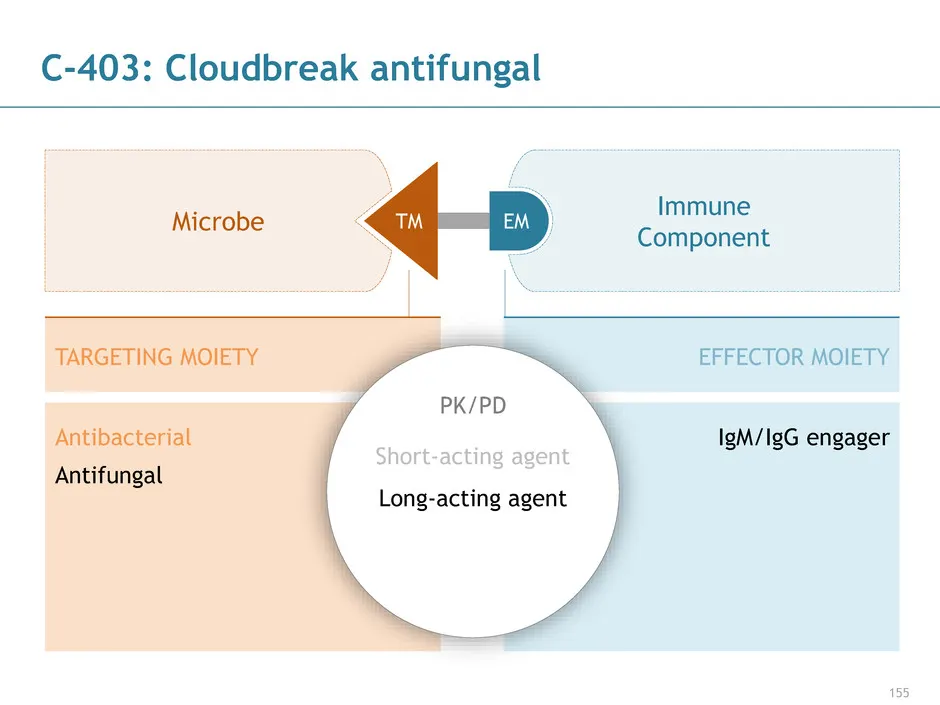
Slide 155: C-403: Cloudbreak antifungal
155 EFFECTOR MOIETYTARGETING MOIETY Microbe Immune Component TM EM Antibacterial Short-acting agent PK/PD C-403: Cloudbreak antifungal Antifungal Long-acting agent IgM/IgG engager
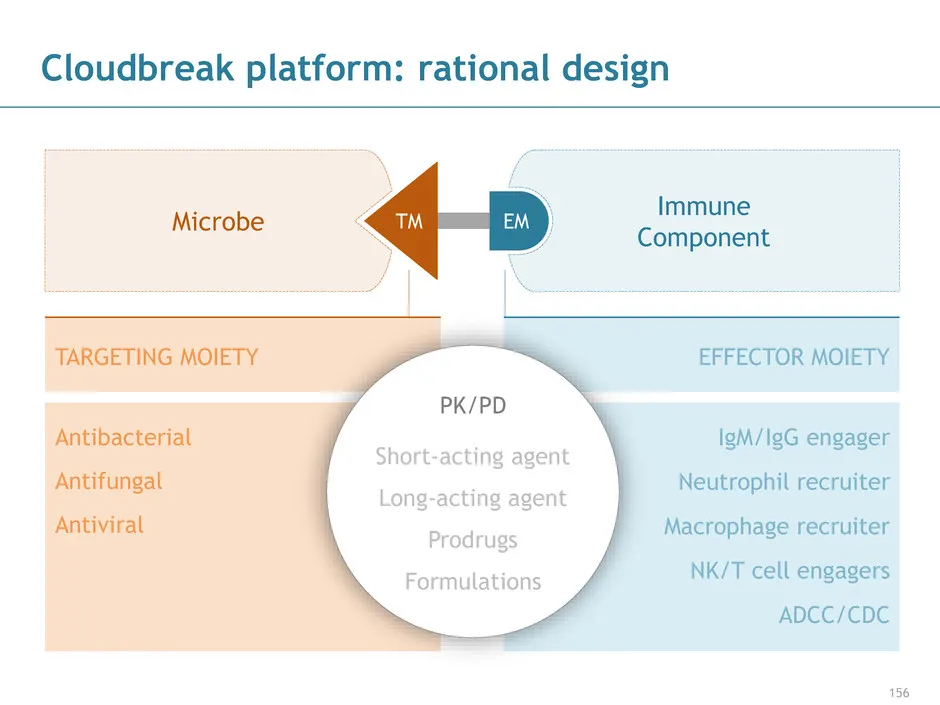
Slide 156: Cloudbreak platform: rational design
156 EFFECTOR MOIETYTARGETING MOIETY Microbe Immune Component TM EM Short-acting agent PK/PD Cloudbreak platform: rational design Long-acting agent Antibacterial Antiviral Neutrophil recruiter Macrophage recruiter NK/T cell engagers ADCC/CDC Prodrugs Formulations Antifungal IgM/IgG engager
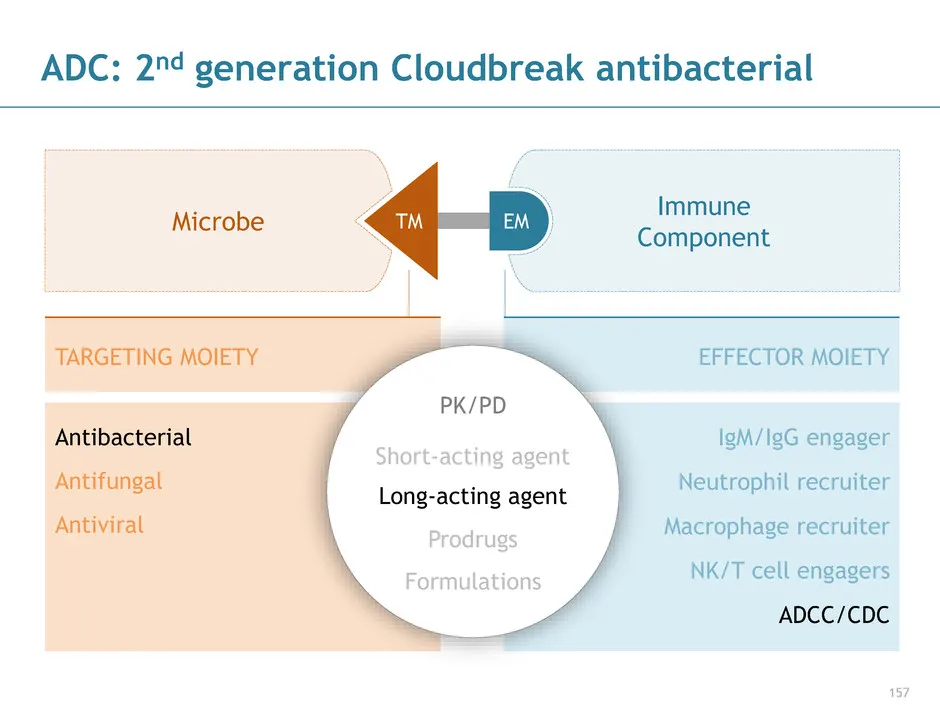
Slide 157: ADC: 2nd generation Cloudbreak antibacterial
157 EFFECTOR MOIETYTARGETING MOIETY Microbe Immune Component TM EM Short-acting agent PK/PD ADC: 2nd generation Cloudbreak antibacterial Long-acting agent Antibacterial Neutrophil recruiter Macrophage recruiter NK/T cell engagers ADCC/CDC Prodrugs Formulations IgM/IgG engager Antiviral Antifungal
Slide 158: Cloudbreak antibacterial ADC
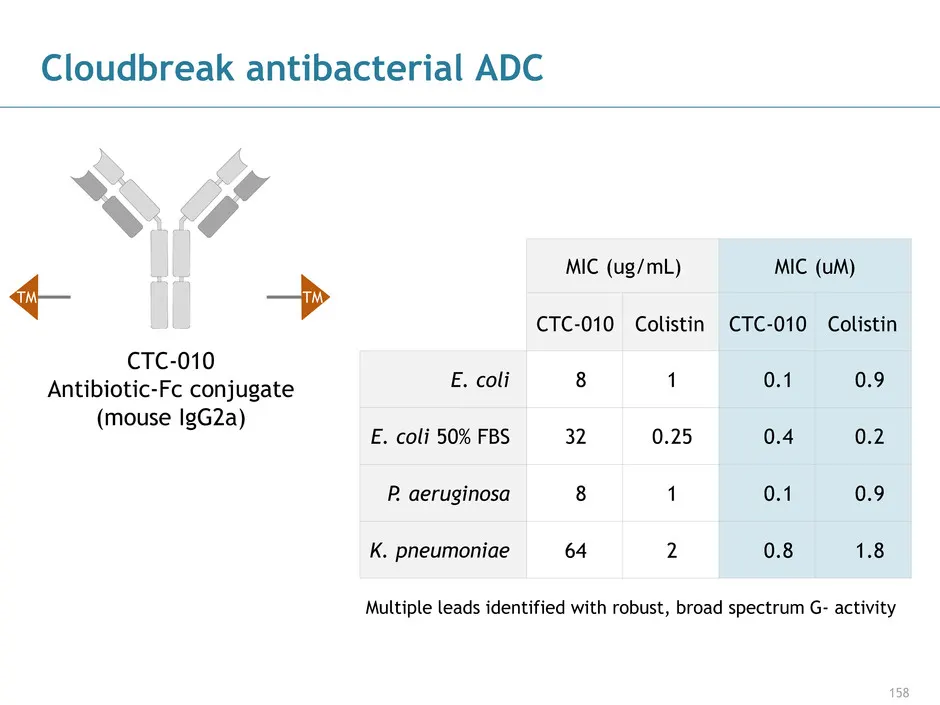
158 CTC-010 Colistin 0.1 0.9 0.4 0.2 0.1 0.9 0.8 1.8 MIC (uM) Cloudbreak antibacterial ADC TM E. coli E. coli 50% FBS P. aeruginosa K. pneumoniae CTC-010 Colistin 8 1 32 0.25 8 1 64 2 MIC (ug/mL) TM CTC-010 Antibiotic-Fc conjugate (mouse IgG2a) Multiple leads identified with robust, broad spectrum G
Slide 159: ADC-mediated binding to E. coli
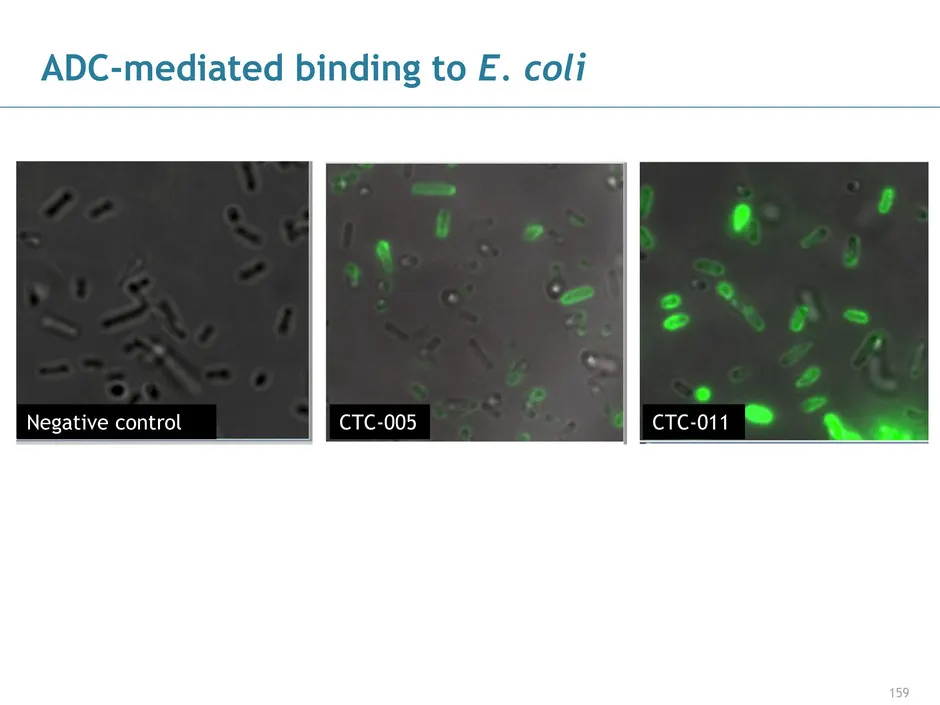
159 ADC-mediated binding to E. coli CTC-005 CTC-011Negative control
Slide 160: CTC-004 in vivo efficacy
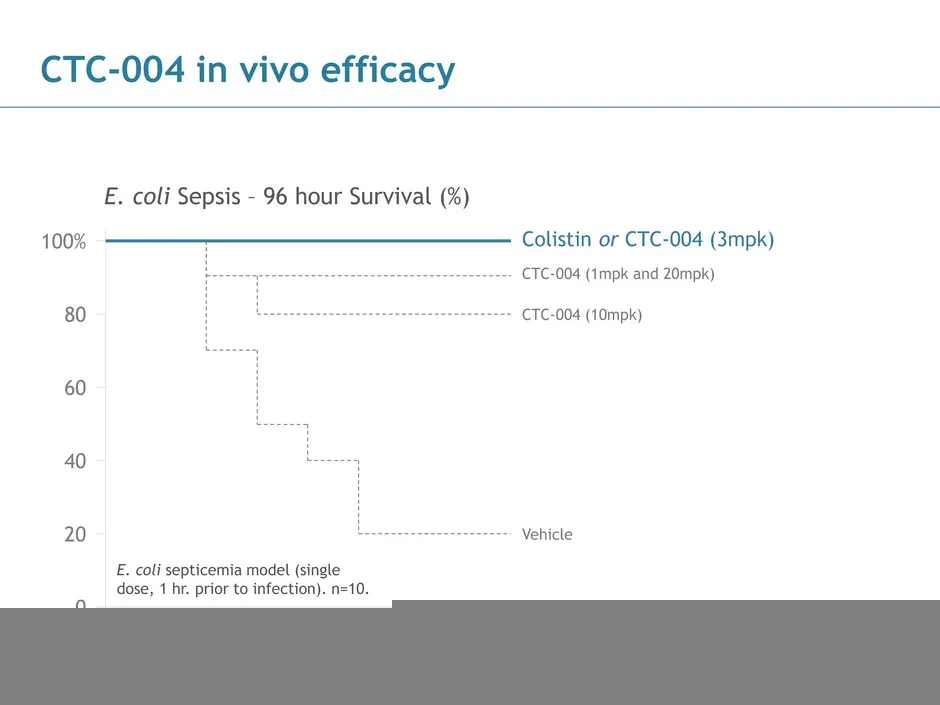
160 100% 80 60 40 20 0 0 24 48 72 96 CTC-004 in vivo efficacy CTC-004 (10mpk) Vehicle CTC-004 (1mpk and 20mpk) Colistin or CTC-004 (3mpk) E. coli Sepsis – 96 hour Survival (%) E. coli septicemia model (single dose, 1 hr. prior to infection). n=10.
Slide 161: Cloudbreak first vs. second generation mouse PK
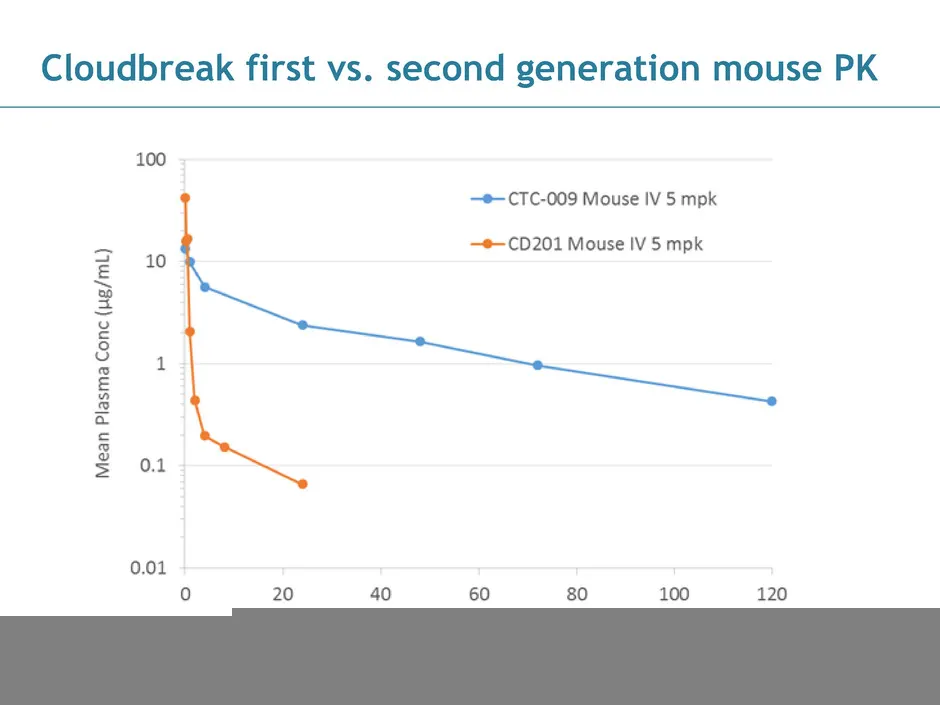
161 Cloudbreak first vs. second generation mouse PK

Slide 162: Wrap-up
162 Wrap-up CD201 development candidate being advanced under CARB-X funding Broad platform established with potential applications across ID Second generation antibacterial ADCs being pursued

Slide 163: Introducing Matt Onaitis
163 Introducing Matt Onaitis CFO and General Counsel, Cidara Therapeutics

Slide 164: Finance
Finance

Slide 165: Executive Summary
165 Executive Summary New information on programs, updated financial data (CD101 for prophylaxis and CD201 for multi- drug resistant Gram-negative bacterial infections) Caveat: All timelines, cost and revenue estimates are subject to change based on regulatory, non-clinical, clinical and other d
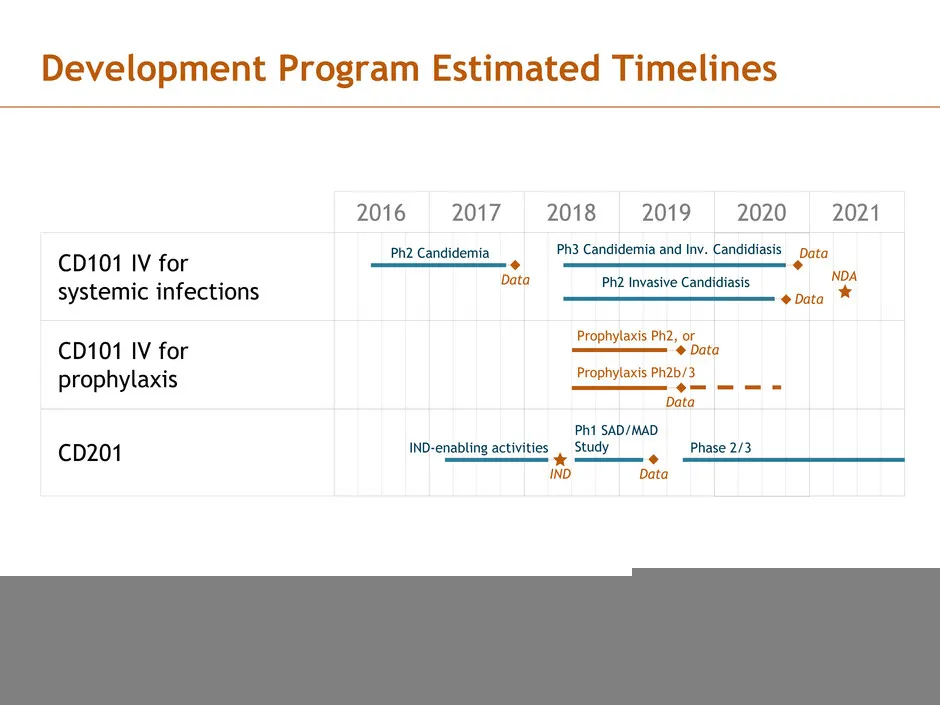
Slide 166: Development Program Estimated Timelines
166 Development Program Estimated Timelines 2016 2017 2018 2019 2020 2021 CD101 IV for systemic infections CD101 IV for prophylaxis CD201 Ph2 Candidemia Ph3 Candidemia and Inv. Candidiasis Ph2 Invasive CandidiasisData Data NDA IND-enabling activities IND Ph1 SAD/MAD Study Data Phase 2/3 Data Prophyl

Slide 167: Cash burn
167 Cash burn 2016 year-end cash: $104.6M 2017 expected cash burn: ~$60-65M CD101 IV: Phase 3 candidemia and Phase 2 invasive candidiasis expected to cost approx. $50M total Approx. $10M of $45M savings from CD101 topical program to be reallocated to CD101 prophylaxis Phase 2 study CD201:
Slide 168: US Peak Sales Estimates
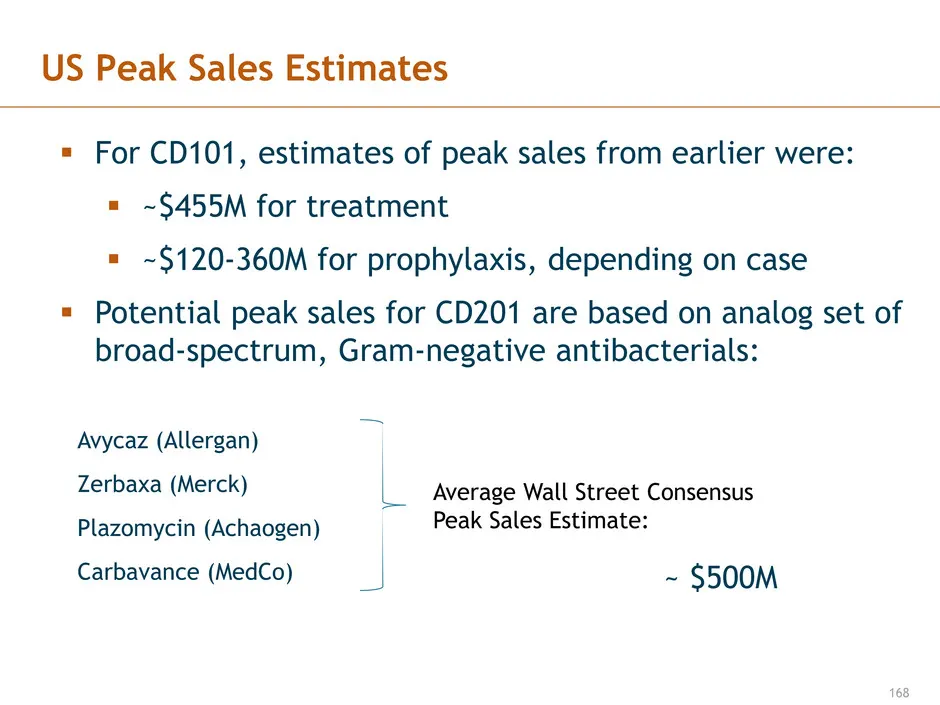
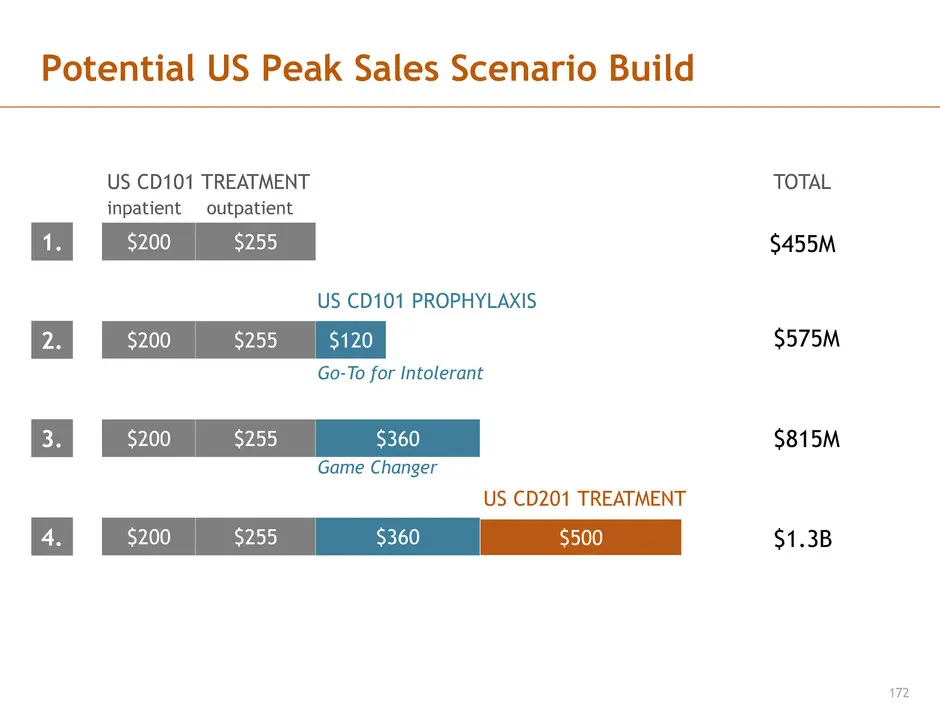
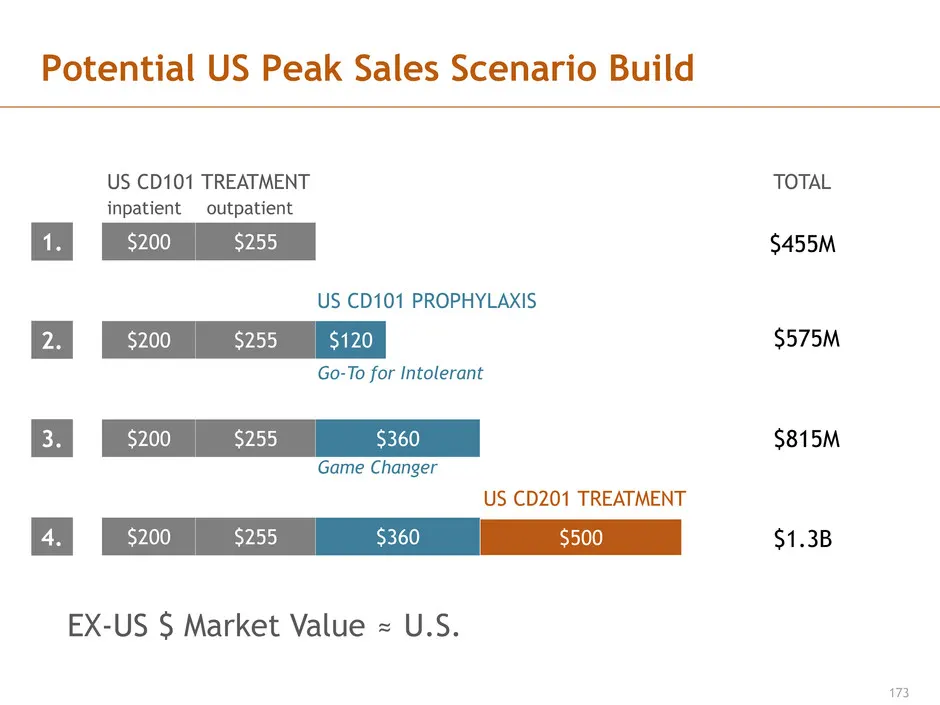
168 US Peak Sales Estimates For CD101, estimates of peak sales from earlier were: ~$455M for treatment ~$120-360M for prophylaxis, depending on case Potential peak sales for CD201 are based on analog set of broad-spectrum, Gram-negative antibacterials: Avycaz (Allergan) Zerbaxa (Merck) Plazo
Slide 169: Potential US Peak Sales Scenario Build
169 Potential US Peak Sales Scenario Build 1. $200 $255 US CD101 TREATMENT inpatient outpatient $455M TOTAL

Slide 170: Potential US Peak Sales Scenario Build
170 Potential US Peak Sales Scenario Build 1. 2. $200 $255 US CD101 TREATMENT inpatient outpatient US CD101 PROPHYLAXIS $200 $255 $120 Go-To for Intolerant $575M $455M TOTAL
Slide 171: Potential US Peak Sales Scenario Build
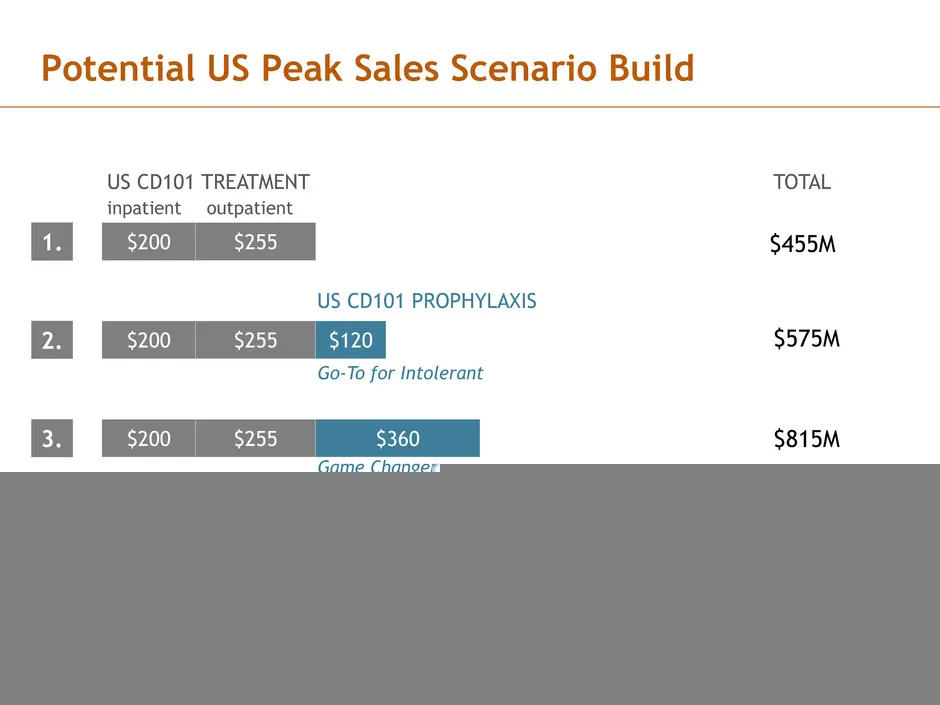
171 Potential US Peak Sales Scenario Build 1. 2. 3. $200 $255 US CD101 TREATMENT inpatient outpatient $200 $255 $360 US CD101 PROPHYLAXIS $200 $255 $120 Go-To for Intolerant Game Changer $815M $575M $455M TOTAL
Slide 172: Potential US Peak Sales Scenario Build
172 Potential US Peak Sales Scenario Build 1. 2. 3. 4. $200 $255 US CD101 TREATMENT inpatient outpatient $200 $255 $360 US CD101 PROPHYLAXIS $200 $255 $120 $200 $255 $360 [?] [?]$500 US CD201 TREATMENT Go-To for Intolerant Game Changer $1.3B $815M $575M $455M TOTAL
Slide 173: Potential US Peak Sales Scenario Build
173 Potential US Peak Sales Scenario Build 1. 2. 3. 4. $200 $255 US CD101 TREATMENT inpatient outpatient $200 $255 $360 US CD101 PROPHYLAXIS $200 $255 $120 $200 $255 $360 [?] [?]$500 US CD201 TREATMENT EX-US $ Market Value U.S.≈ Go-To for Intolerant Game Changer $1.3B $815M $575M $455M TOTAL

Slide 174: Conclusion and Q&A
Conclusion and Q&A
Source: SEC EDGAR · 8-K filed Apr 6, 2017
More decks from Cidara Therapeutics Inc
 Corporate Update (June 2025)12 slides · Jun 23, 2025
 Investor Presentation (May 2024)63 slides · May 3, 2024
 Investor Day (September 2023)58 slides · Sep 21, 2023
 Investor Day (July 2022)57 slides · Jul 7, 2022
 Technical Presentation (December 2021)24 slides · Dec 14, 2021
 Investor Day (September 2021)110 slides · Sep 21, 2021