Cidara Therapeutics — Investor Day (November 2019)
96 slides from Cidara Therapeutics's investor day presentation, Nov 14, 2019

Slide 1: New Hope for Serious Infections: Analyst – KOL Day
New Hope for Serious Infections Analyst – KOL Day Introduction November 14, 2019 © Cidara Therapeutics 2019

Slide 2: Forward-Looking Statements
Forward-Looking Statements Because such statements are subject to risks and uncertainties, actual single dose protection, represent an improvement over These slides and the results may differ materially from those expressed or implied by such existing therapies or will also be observed in human use;

Slide 3: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, Ph.D., CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto

Slide 4: Cidara overview
SB 12 Cidara overview Leading science on antifungal and antiviral prevention and treatment st st Rezafungin Developing 1 antifungal in 13 years for 1 line treatment and prophylaxis Treatment – Phase 3 Catalyst: Phase 3 readout in 2020 to support NDA Potential to transform prevention in high risk hem
Slide 5: Rezafungin overall phase development plan
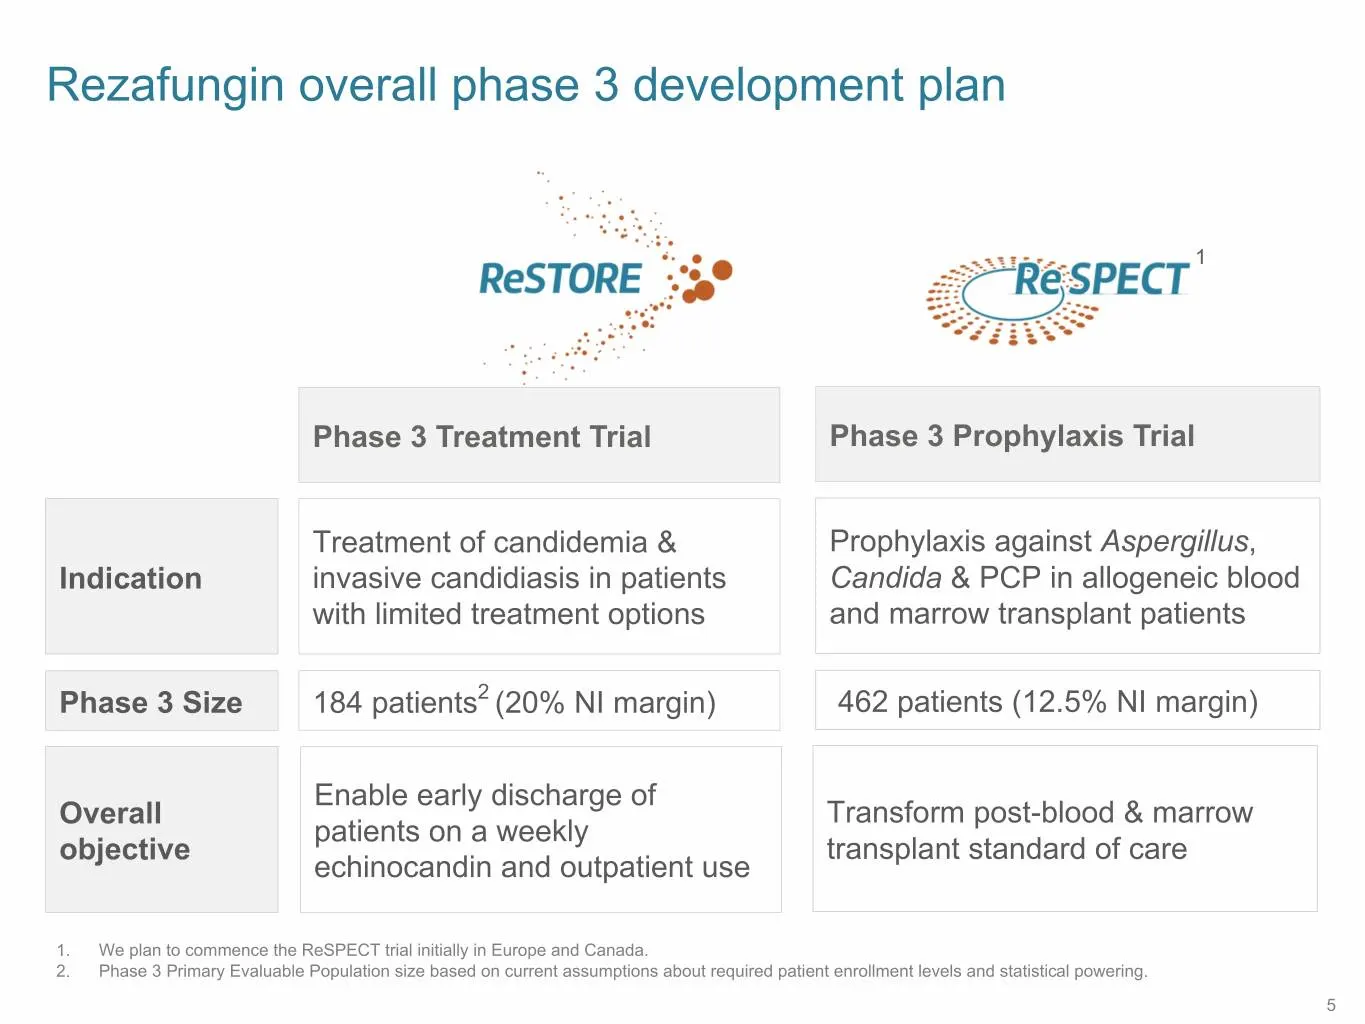
Rezafungin overall phase 3 development plan 1 Phase 3 Treatment Trial Phase 3 Prophylaxis Trial Treatment of candidemia & Prophylaxis against Aspergillus, Indication invasive candidiasis in patients Candida & PCP in allogeneic blood with limited treatment options and marrow transplant patients Phase

Slide 6: STRIVE B Phase data in candidemia & invasive candidiasis
STRIVE B Phase 2 data in candidemia & invasive candidiasis Corroborates STRIVE A results and supports ReSTORE Phase 3 6
Slide 7: P2 STRIVE Program: Candidemia & Invasive Candidiasis
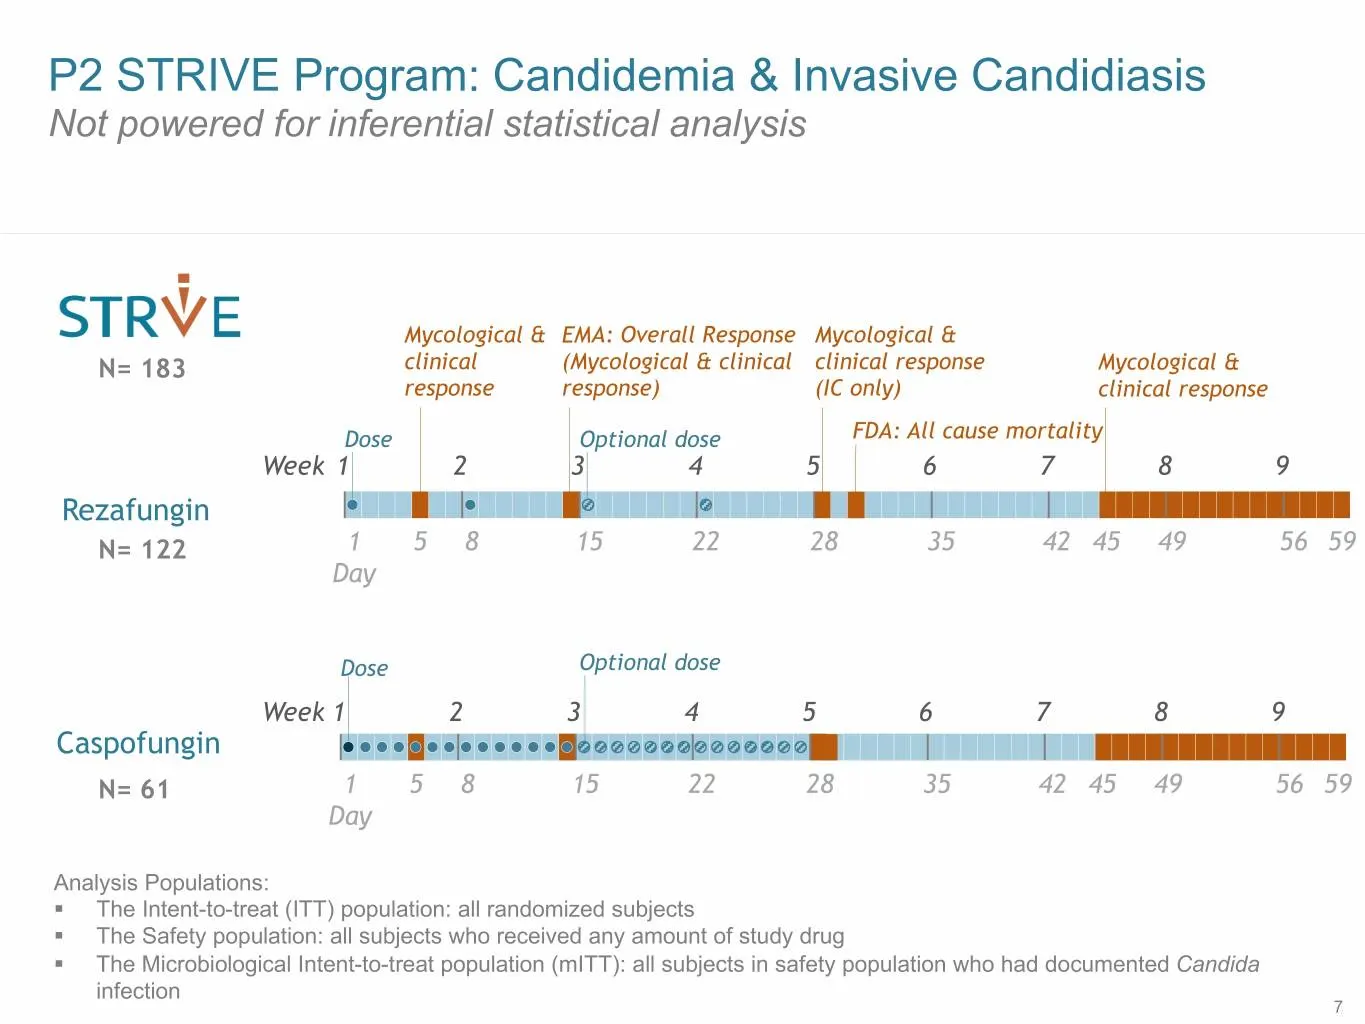
P2 STRIVE Program: Candidemia & Invasive Candidiasis Not powered for inferential statistical analysis Mycological & EMA: Overall Response Mycological & N= 183 clinical (Mycological & clinical clinical response Mycological & response response) (IC only) clinical response Dose Optional dose FDA: All c
Slide 8: Rezafungin: Superior on time to negative blood culture
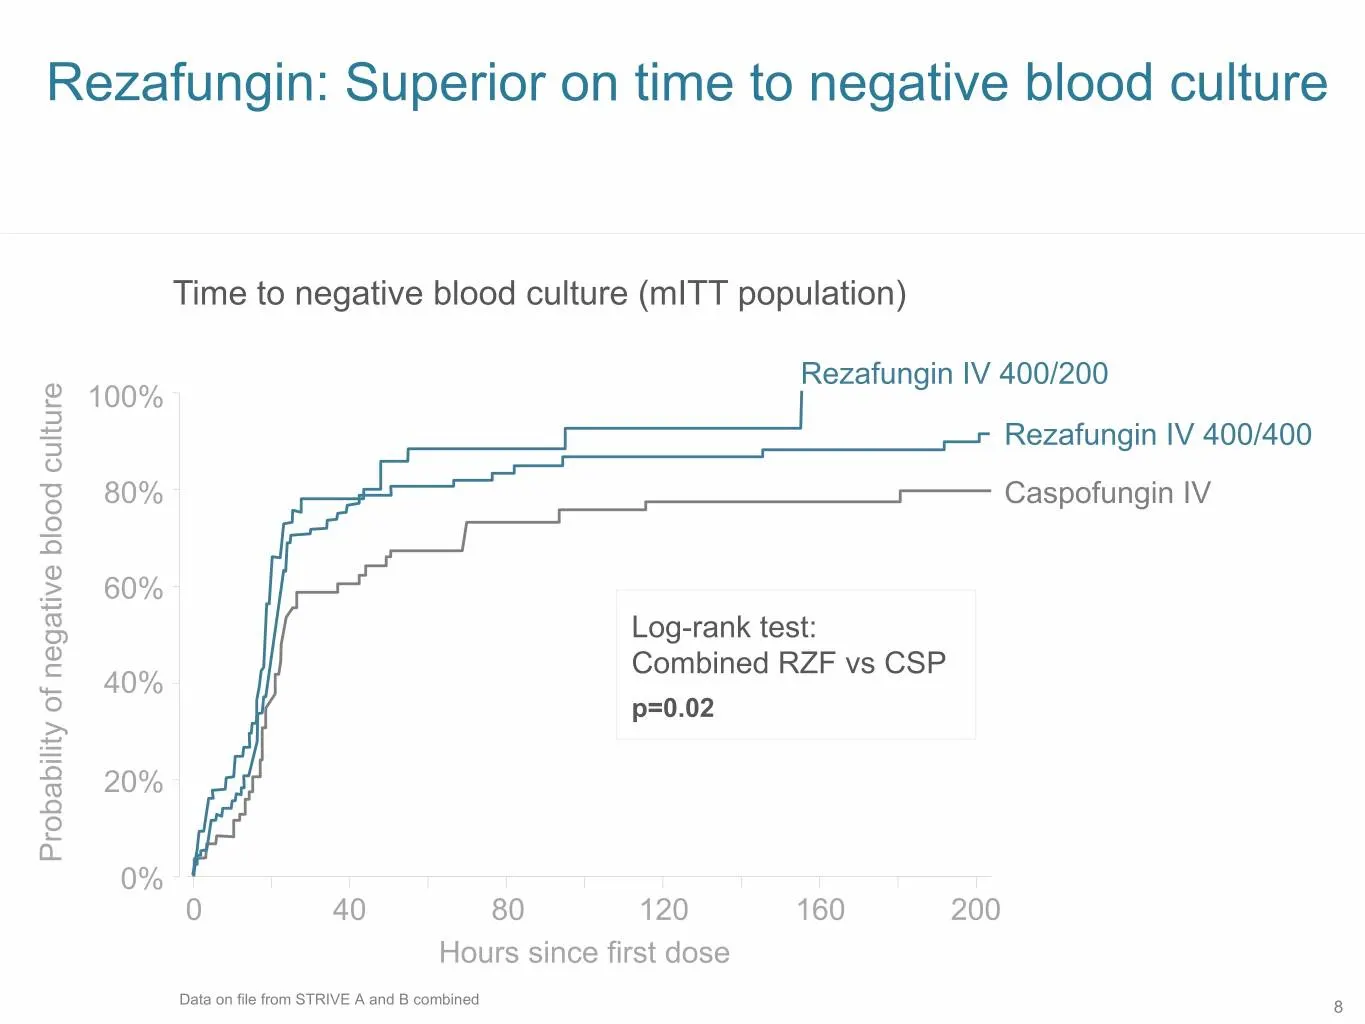
Rezafungin: Superior on time to negative blood culture Time to negative blood culture (mITT population) Rezafungin IV 400/200 100% Rezafungin IV 400/400 80% Caspofungin IV 60% Log-rank test: Combined RZF vs CSP 40% p=0.02 20% Probability of negative blood culture of blood negative Probability 0% 0 4
Slide 9: 30-Day All Cause Mortality – Post Hoc Analysis
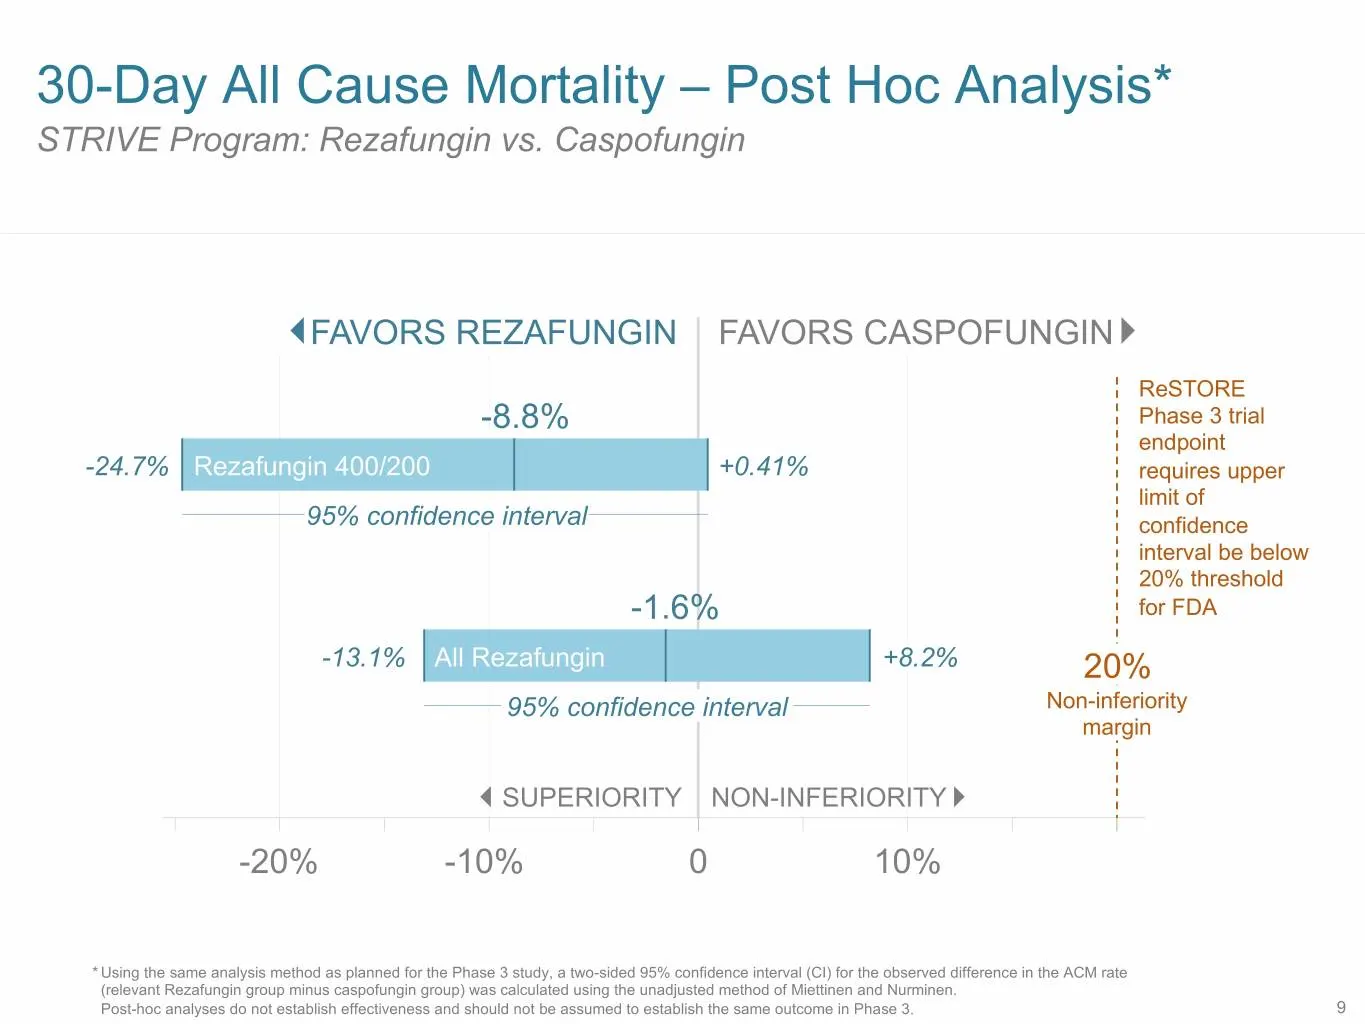
30-Day All Cause Mortality – Post Hoc Analysis* STRIVE Program: Rezafungin vs. Caspofungin FAVORS REZAFUNGIN FAVORS CASPOFUNGIN ReSTORE -8.8% Phase 3 trial endpoint -24.7% Rezafungin 400/200 +0.41% requires upper limit of 95% confidence interval confidence interval be below 20% threshold -1.6% for F
Slide 10: Day 14 Clinical Response – Post Hoc Analysis
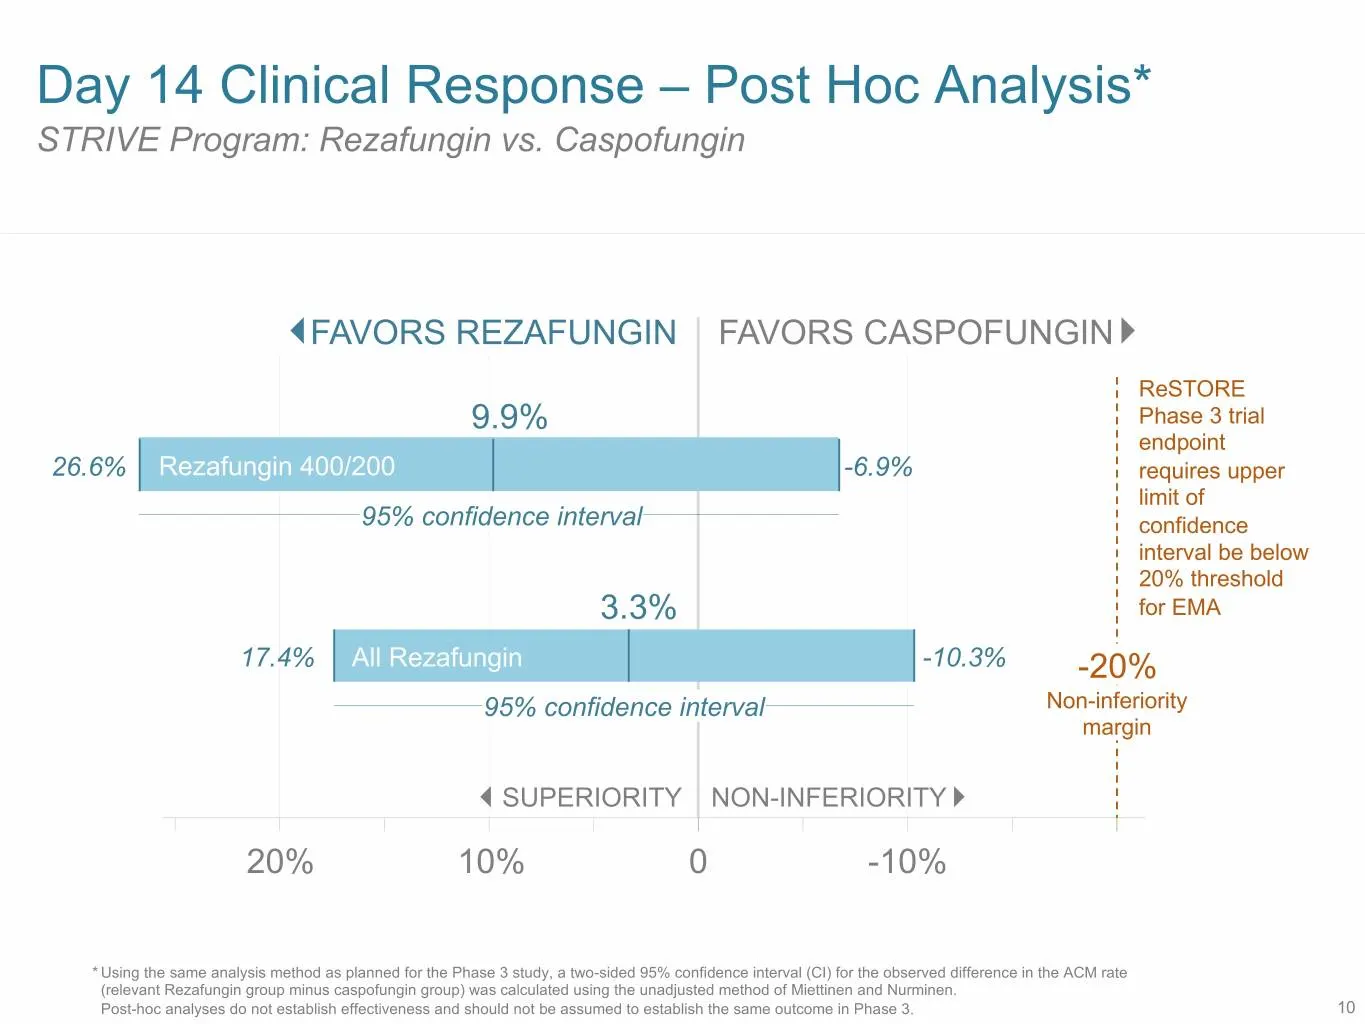
Day 14 Clinical Response – Post Hoc Analysis* STRIVE Program: Rezafungin vs. Caspofungin FAVORS REZAFUNGIN FAVORS CASPOFUNGIN ReSTORE 9.9% Phase 3 trial endpoint 26.6% Rezafungin 400/200 -6.9% requires upper limit of 95% confidence interval confidence interval be below 20% threshold 3.3% for EMA 17.
Slide 11: Rezafungin overall phase development plan
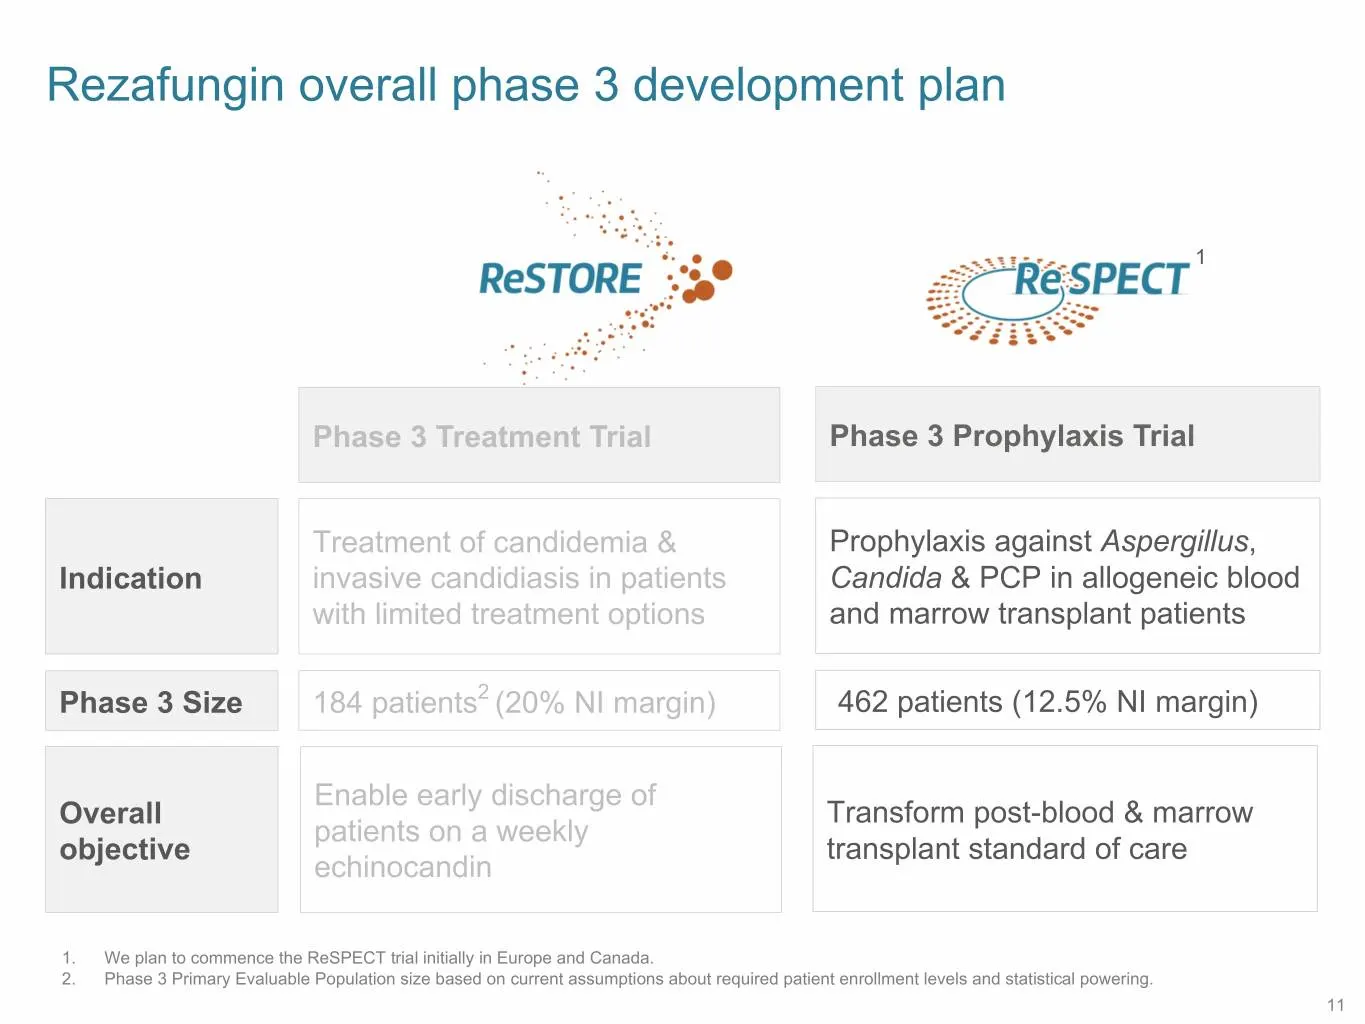
Rezafungin overall phase 3 development plan 1 Phase 3 Treatment Trial Phase 3 Prophylaxis Trial Treatment of candidemia & Prophylaxis against Aspergillus, Indication invasive candidiasis in patients Candida & PCP in allogeneic blood with limited treatment options and marrow transplant patients Phase
Slide 12: The current standard of care is inadequate
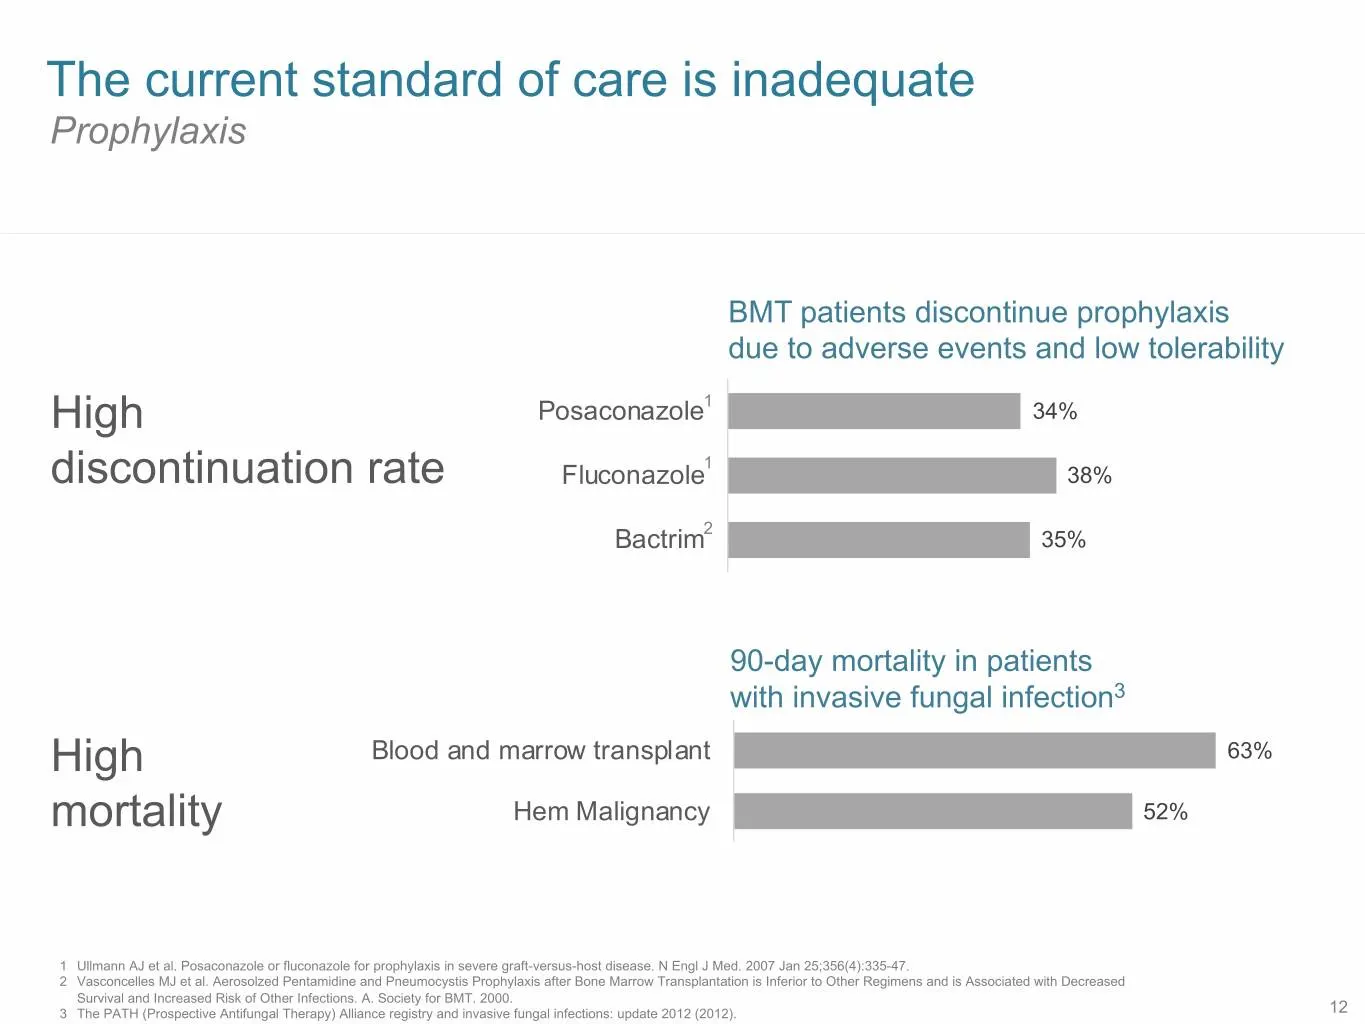
The current standard of care is inadequate Prophylaxis BMT patients discontinue prophylaxis due to adverse events and low tolerability High Posaconazole1 34% 1 discontinuation rate Fluconazole 38% 2 Bactrim 35% 90-day mortality in patients with invasive fungal infection3 High Blood and marrow transp
Slide 13: Rezafungin: potential simplified single drug paradigm
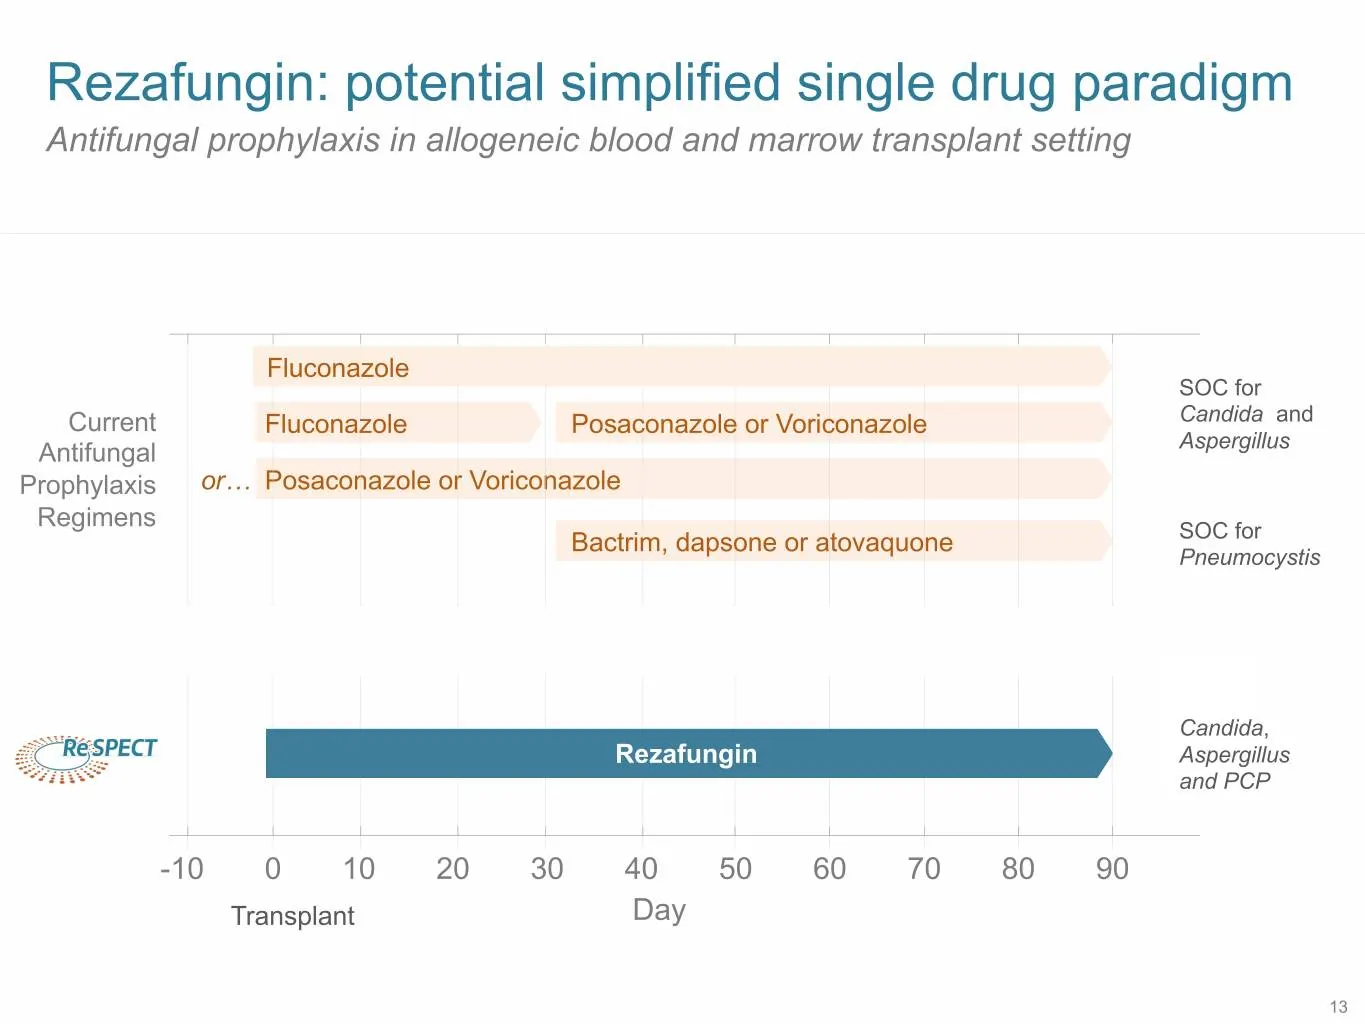
Rezafungin: potential simplified single drug paradigm Antifungal prophylaxis in allogeneic blood and marrow transplant setting Fluconazole SOC for Current Fluconazole Posaconazole or Voriconazole Candida and Antifungal Aspergillus Prophylaxis or… Posaconazole or Voriconazole Regimens Bactrim, dapson
Slide 14: Our partner for rezafungin
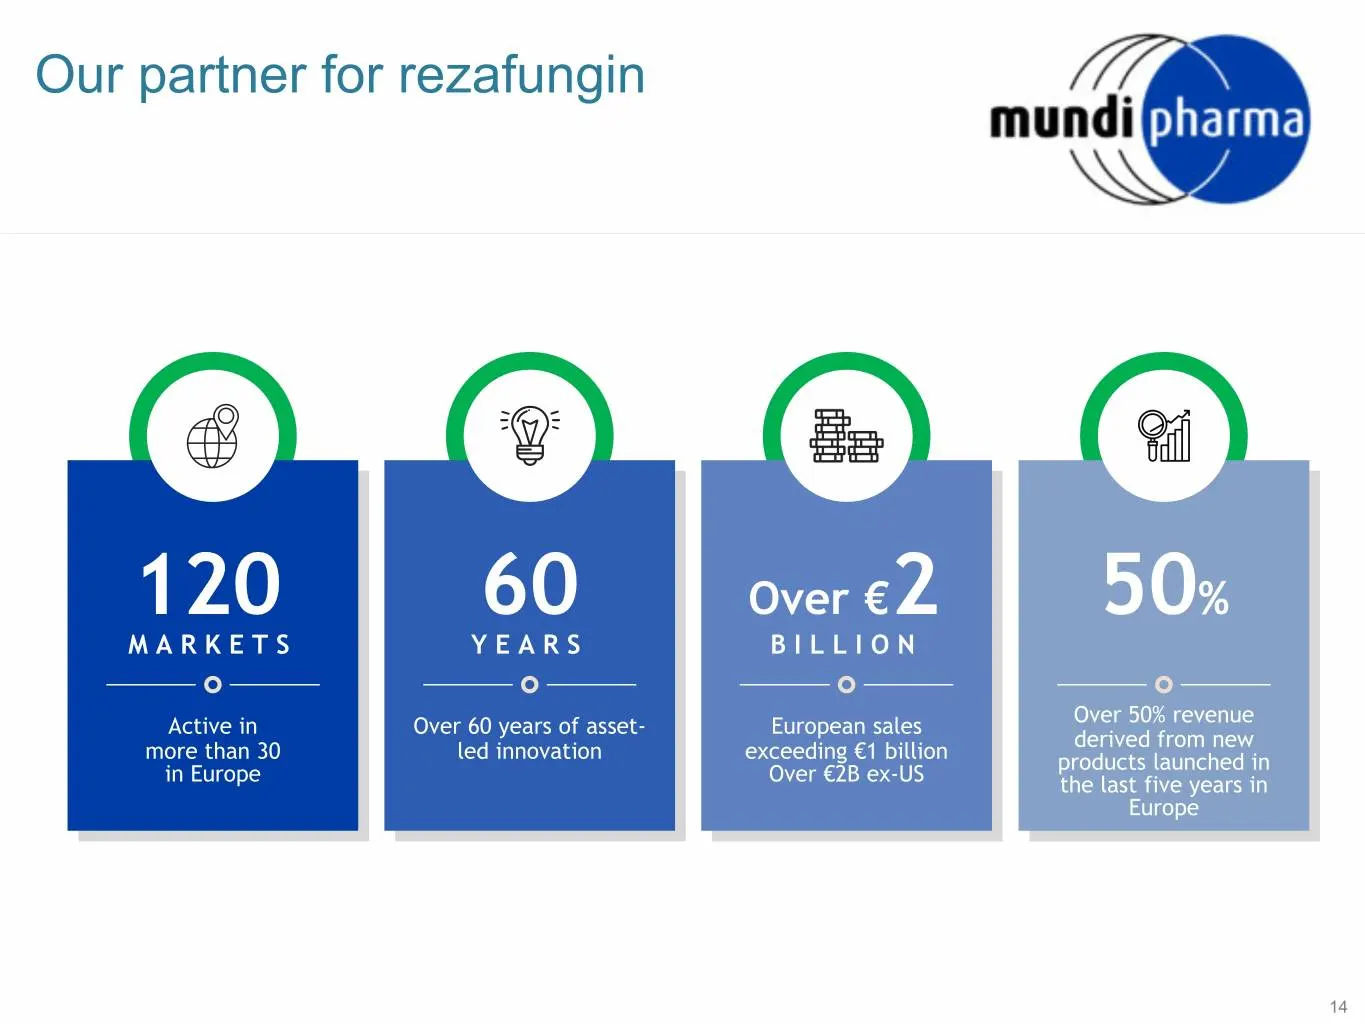
Our partner for rezafungin 120 60 Over €2 50% MARKETS YEARS BILLION Active in Over 60 years of asset- European sales Over 50% revenue derived from new more than 30 led innovation exceeding €1 billion products launched in in Europe Over €2B ex-US the last five years in Europe 14
Slide 15: Antifungals are valued higher than antibiotics
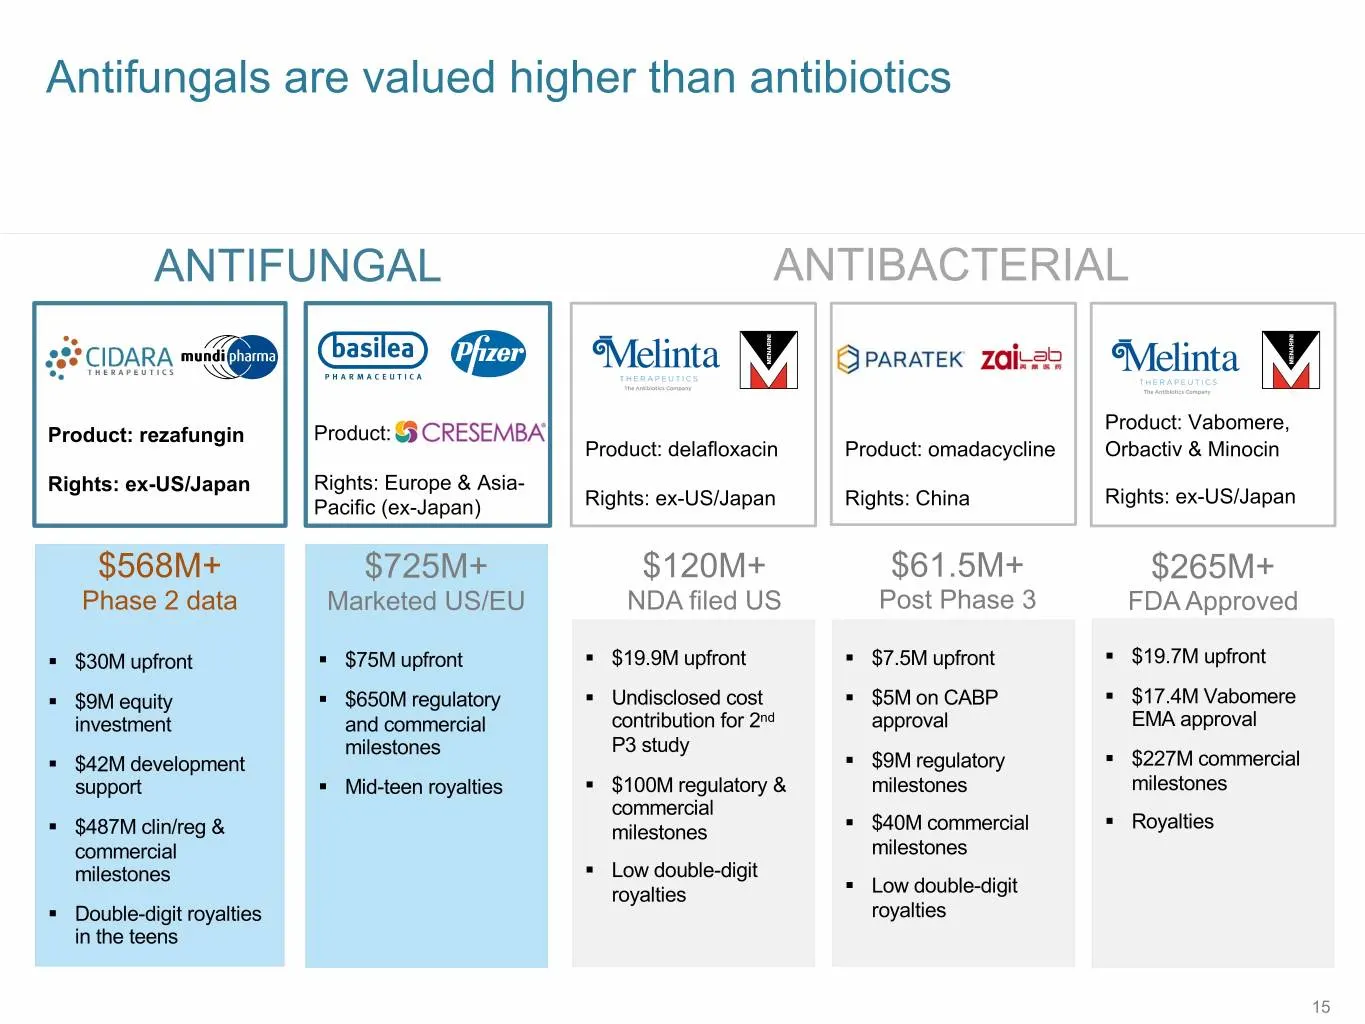
Antifungals are valued higher than antibiotics ANTIFUNGAL ANTIBACTERIAL Product: Vabomere, Product: rezafungin Product: Product: delafloxacin Product: omadacycline Orbactiv & Minocin Rights: ex-US/Japan Rights: Europe & Asia- Rights: ex-US/Japan Pacific (ex-Japan) Rights: ex-US/Japan Rights: China $

Slide 16: Cidara's pipeline targets multiple unmet medical needs
Cidara’s pipeline targets multiple unmet medical needs Rezafungin Cloudbreak 16

Slide 17: Cloudbreak antiviral conjugates (AVCs) for influenza
Cloudbreak antiviral conjugates (AVCs) for influenza: Potential single dose universal protection and treatment of seasonal and pandemic influenza 17

Slide 18: A perfect universal vaccine: more aspirational than realistic
SB 17 A perfect universal vaccine: “more aspirational than realistic”1 Anthony Fauci, NIAID 2009 H1N1 FLU 284,000 deaths WW A strain like the Spanish flu could kill 33 million people in the first 6 months, roughly the amount of time it takes to produce an influenza vaccine.1,2 “…would leave us cripp
Slide 19: Cloudbreak Platform: Antiviral Conjugates (AVCs)
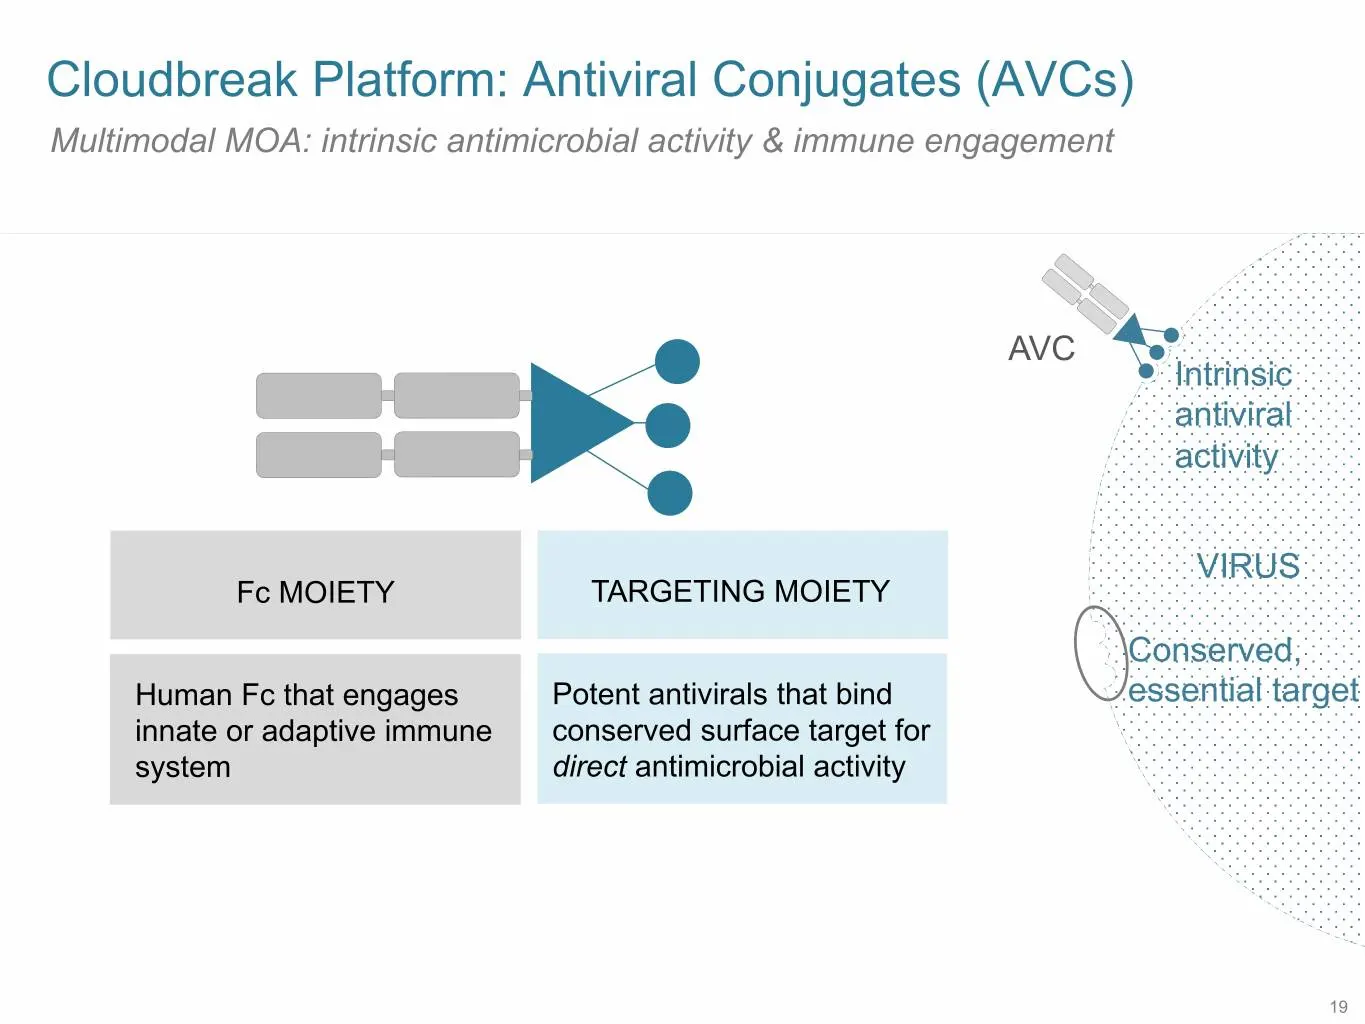
SB 9 Cloudbreak Platform: Antiviral Conjugates (AVCs) Multimodal MOA: intrinsic antimicrobial activity & immune engagement AVC Intrinsic antiviral activity VIRUS Fc MOIETY TARGETING MOIETY Conserved, Human Fc that engages Potent antivirals that bind essential target innate or adaptive immune conserv

Slide 20: What would an ideal influenza product look like?
SB 12 What would an “ideal” influenza product look like? AVCs (pre-clinical Vaccines Drugs* in vivo data) Superior resistance profile ü Expanded efficacy window ü Long duration of action ü ü Broad spectrum, universal coverage üXofluza ü Protection for high-risk populations ü ü Rapid onset of activit
Slide 21: Reduced resistance potential
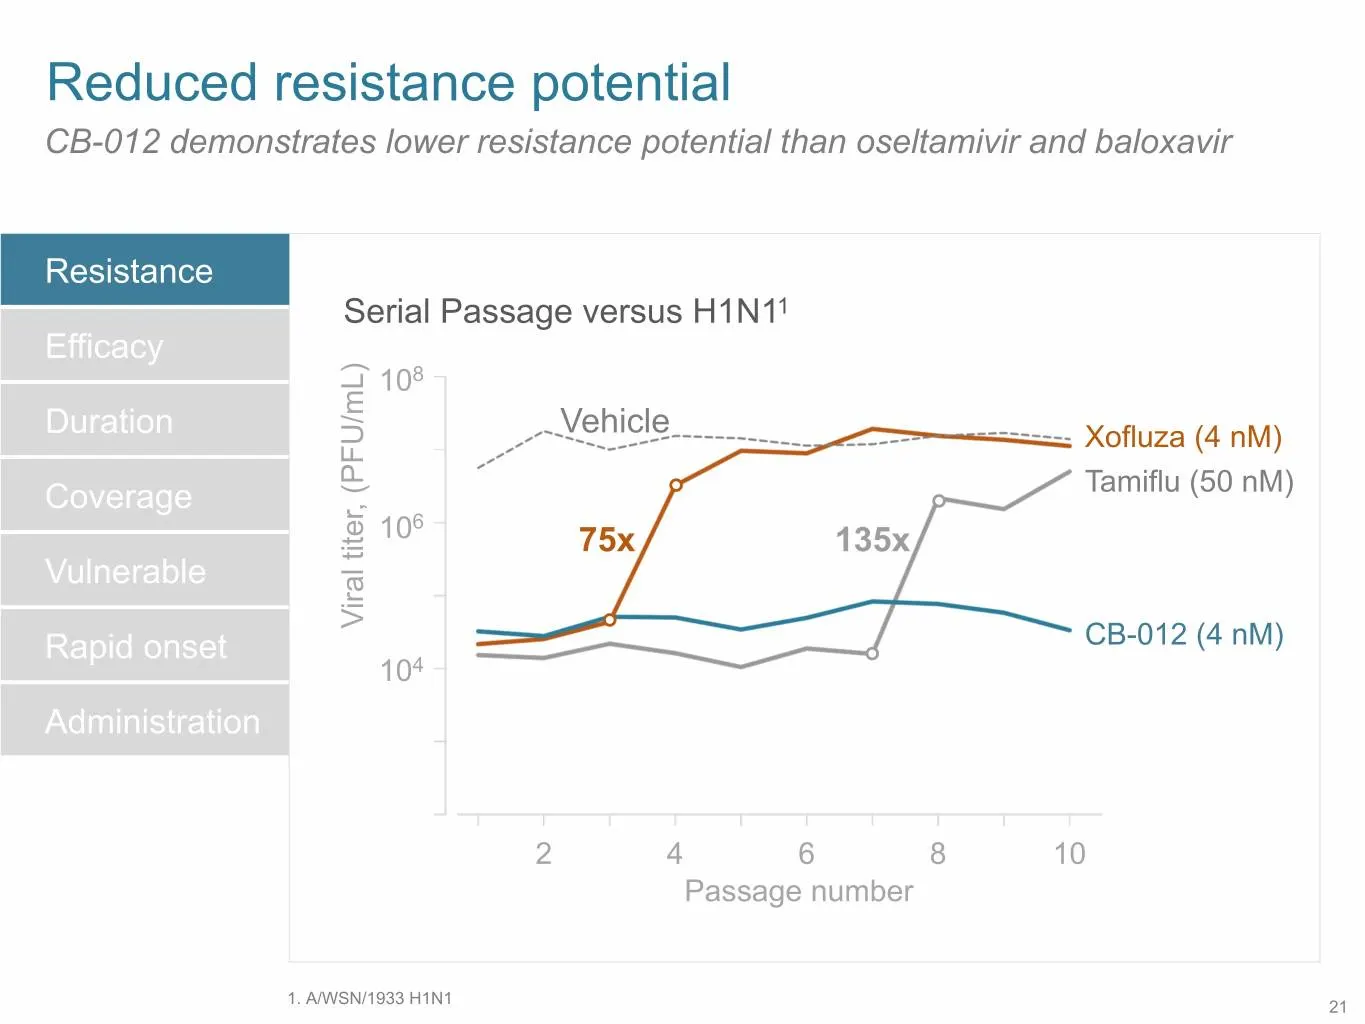
SB 14 Reduced resistance potential CB-012 demonstrates lower resistance potential than oseltamivir and baloxavir Resistance Serial Passage versus H1N11 Efficacy 108 Duration Vehicle Xofluza (4 nM) Coverage Tamiflu (50 nM) 6 10 75x 135x Vulnerable Viral titer, (PFU/mL) Rapid onset CB-012 (4 nM) 104 A
Slide 22: Potential expansion of the treatment window
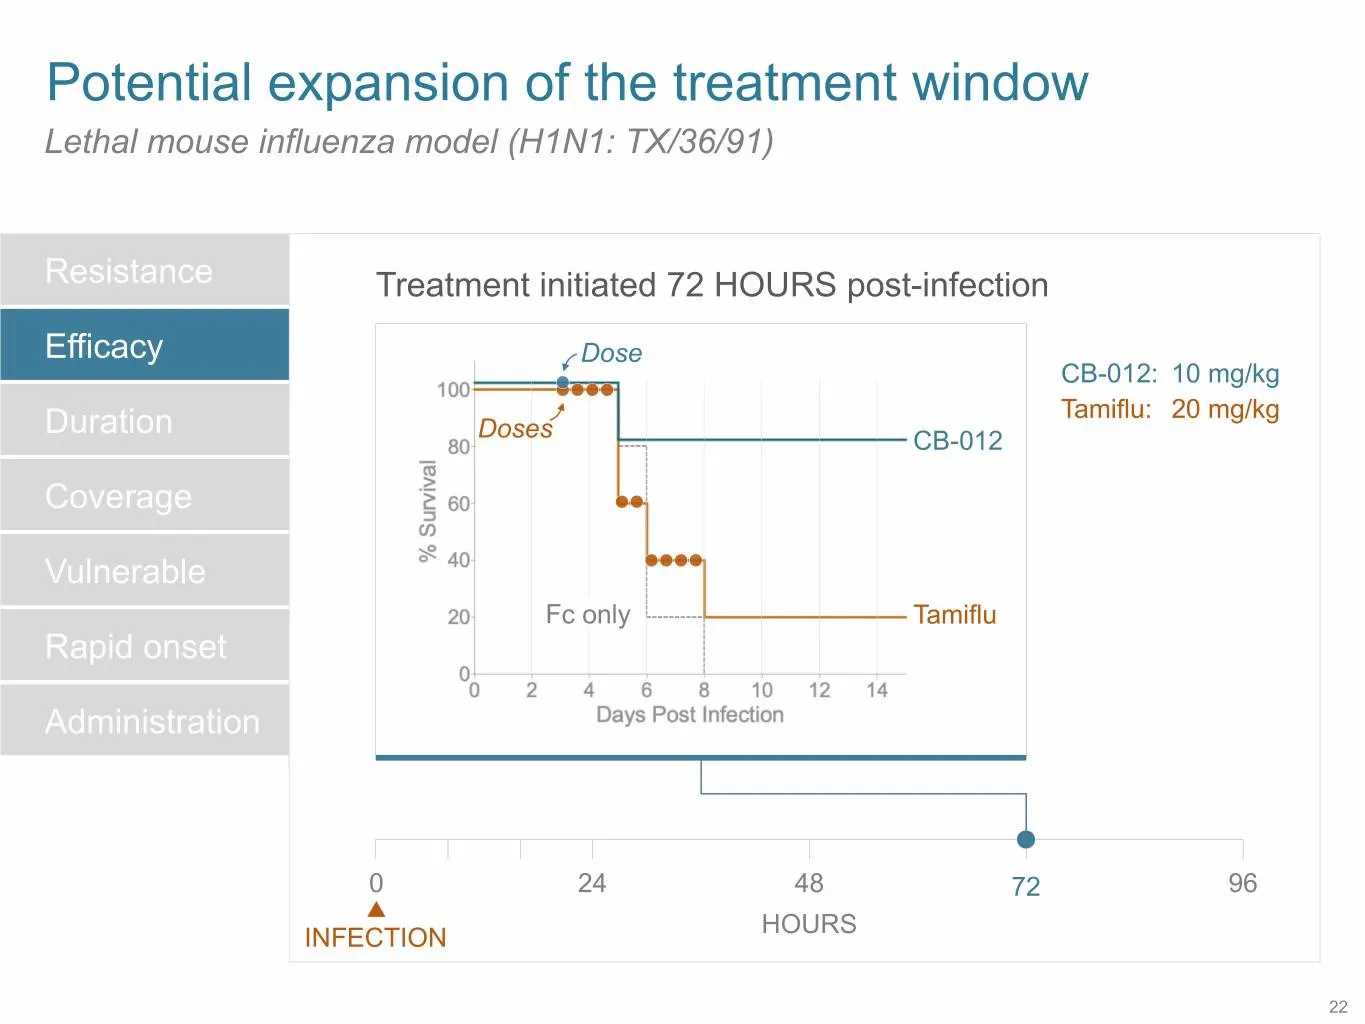
SB 14 Potential expansion of the treatment window Lethal mouse influenza model (H1N1: TX/36/91) Resistance Treatment initiated 72 HOURS post-infection Efficacy Dose CB-012: 10 mg/kg Duration Tamiflu: 20 mg/kg Doses CB-012 Coverage Vulnerable Fc only Tamiflu Rapid onset Administration 0 24 48 72 96 H
Slide 23: Potential for long-term single dose protection
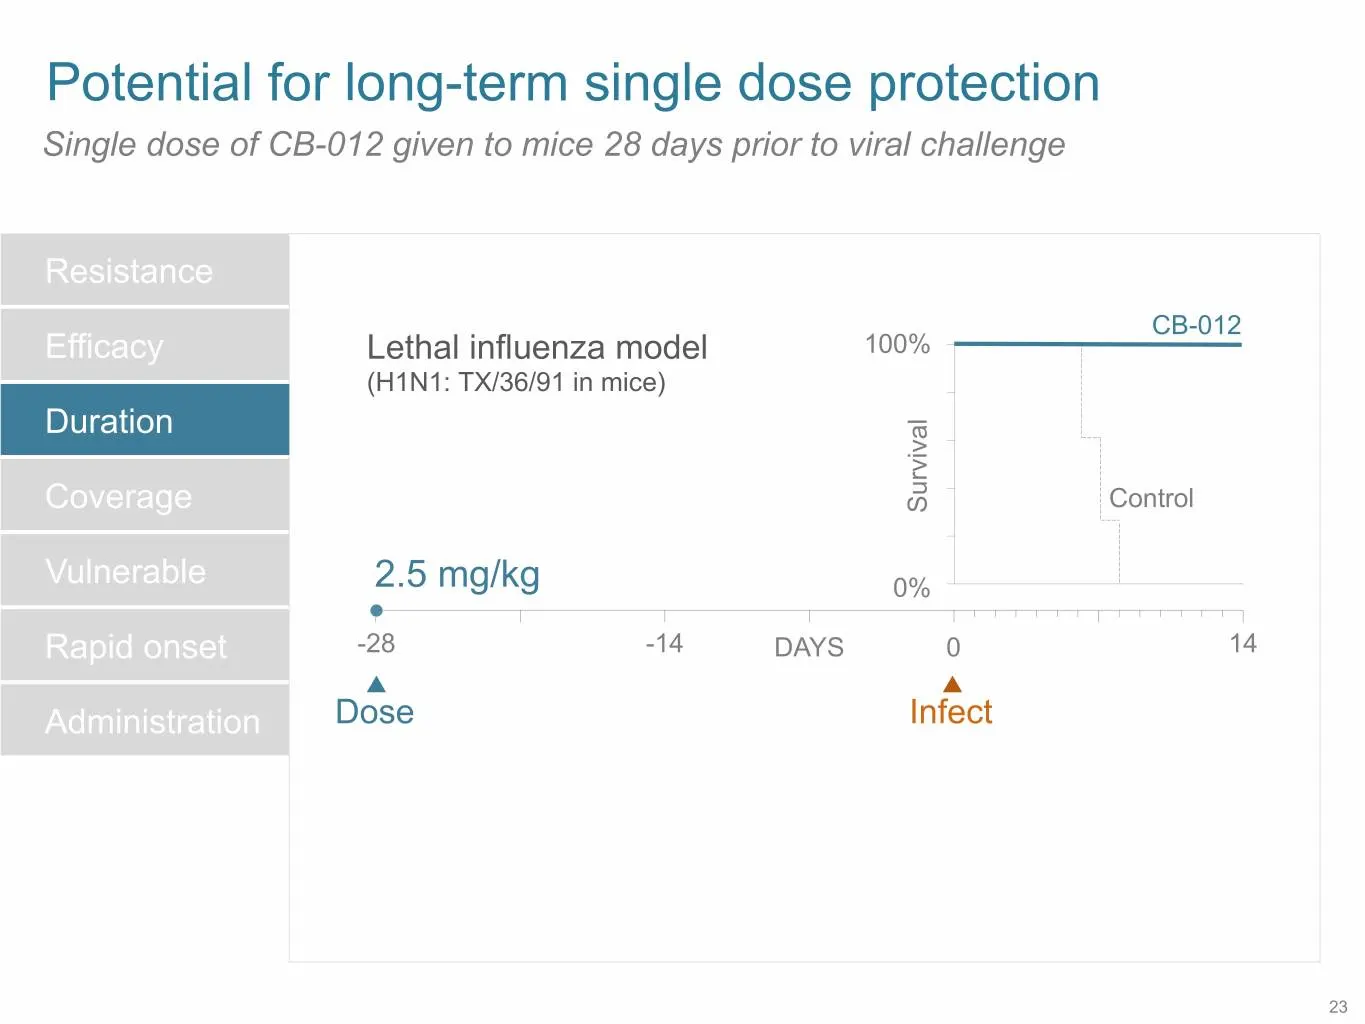
SB 14 Potential for long-term single dose protection Single dose of CB-012 given to mice 28 days prior to viral challenge Resistance CB-012 Efficacy Lethal influenza model 100% (H1N1: TX/36/91 in mice) Duration Control Coverage Survival Vulnerable 2.5 mg/kg 0% Rapid onset -28 -14 DAYS 0 14 Administr
Slide 24: Cloudbreak platform: potential applications beyond influenza
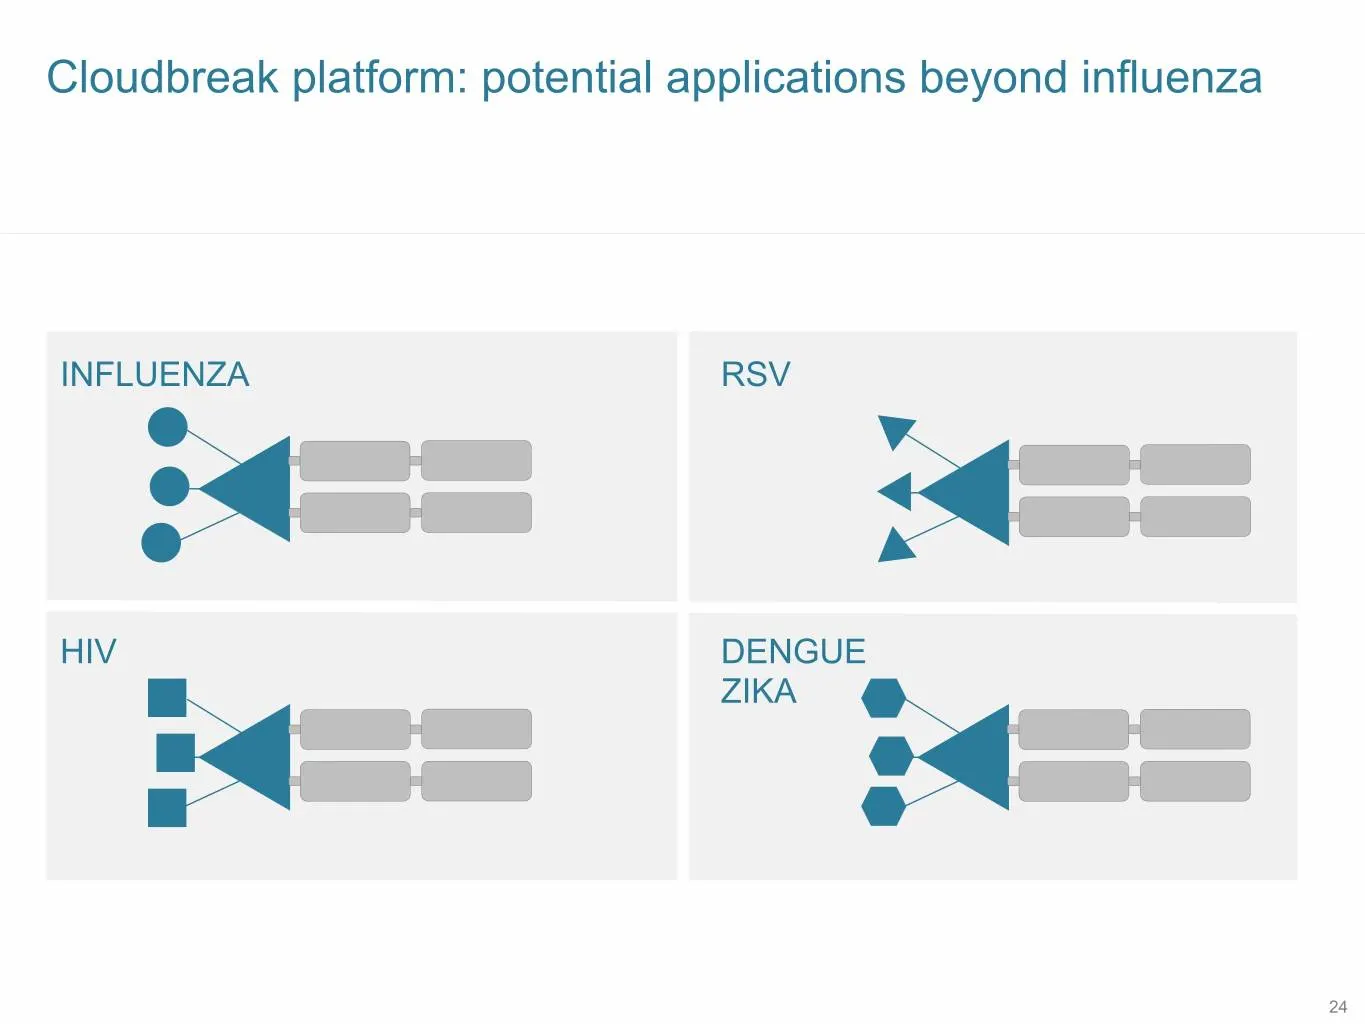
Cloudbreak platform: potential applications beyond influenza INFLUENZA RSV HIV DENGUE ZIKA 24

Slide 25: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 26: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 27: Unmet needs in treatment of invasive fungal disease
Unmet needs in treatment of invasive fungal disease Cornelius J. (Neil) Clancy, M.D. University of Pittsburgh Pittsburgh, PA Cidara Analyst Day NYC, NY 14 November 2019

Slide 28: Fungal infections at UPMC-PUH
Fungal infections at UPMC-PUH
Slide 29: Fungal infections at UPMC-PUH
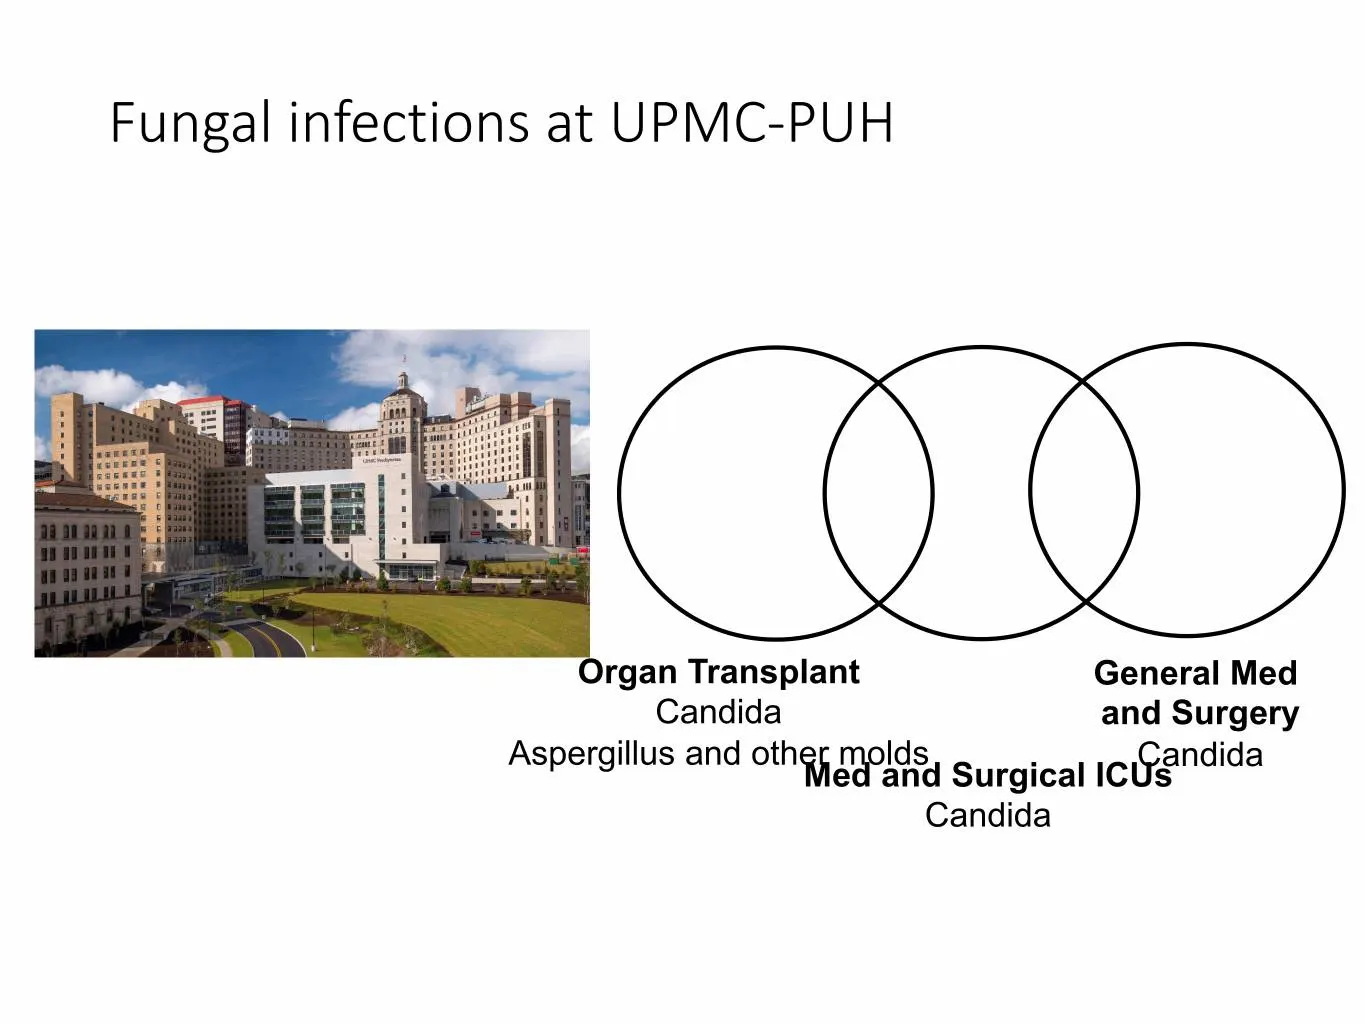
Fungal infections at UPMC-PUH Organ Transplant General Med Candida and Surgery Aspergillus and other molds Candida Med and Surgical ICUs Candida
Slide 30: Infections in US hospitals
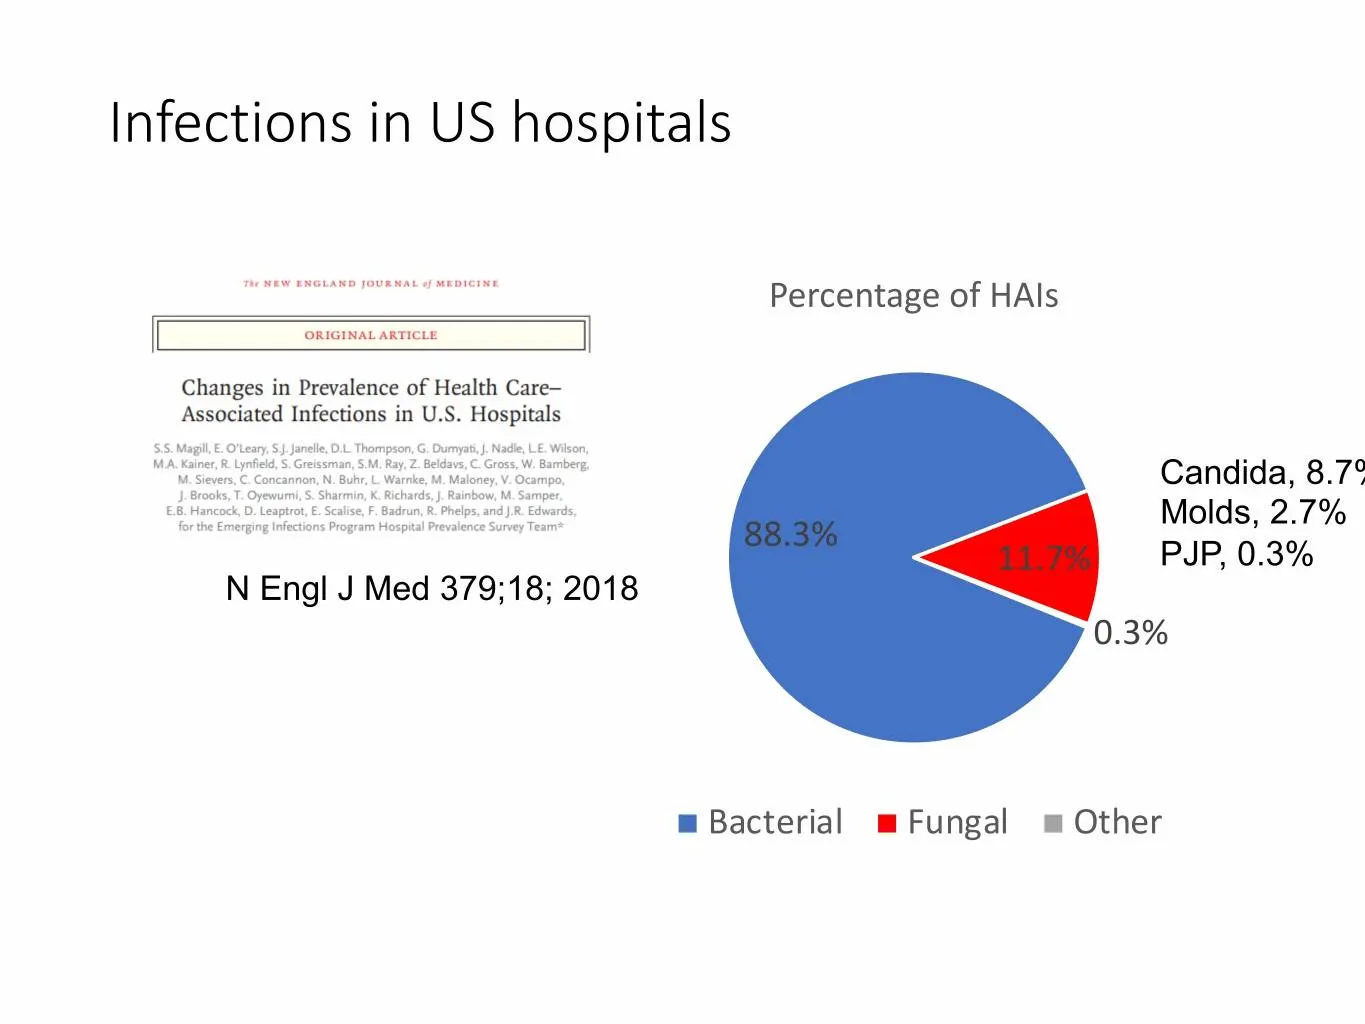
Infections in US hospitals Percentage of HAIs Candida, 8.7% Molds, 2.7% 88.3% 11.7% PJP, 0.3% N Engl J Med 379;18; 2018 0.3% Bacterial Fungal Other
Slide 31: Antimicrobial expenditures in hospitals
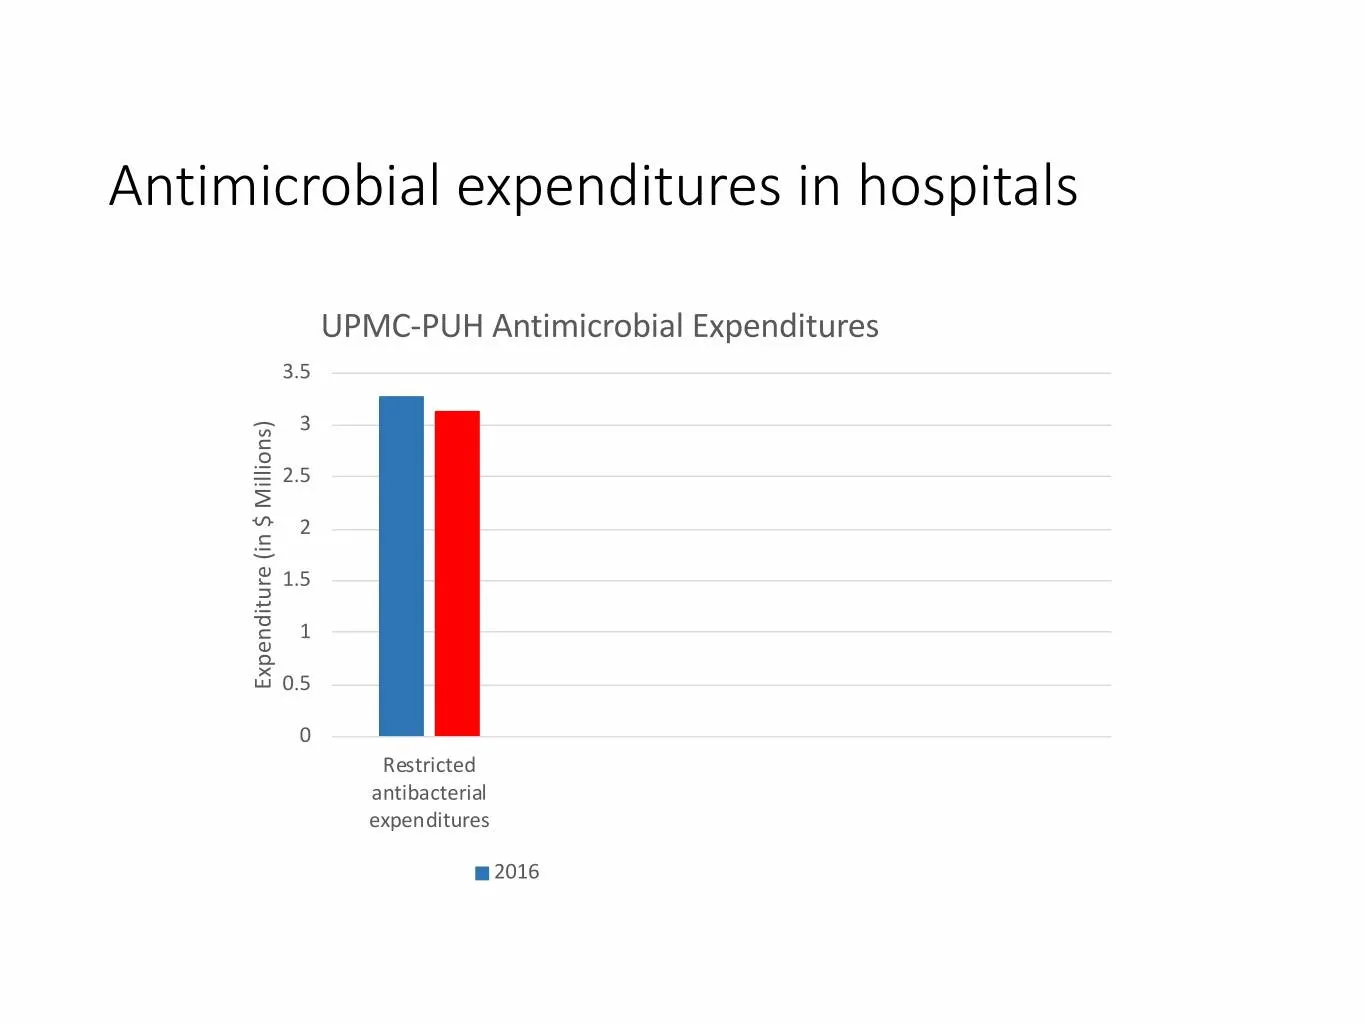
Antimicrobial expenditures in hospitals UPMC-PUH Antimicrobial Expenditures 3.5 3 2.5 2 1.5 1 Expenditure (in $ Millions) $ (in Expenditure 0.5 0 Restricted antibacterial expenditures 2016
Slide 32: Antimicrobial expenditures in hospitals
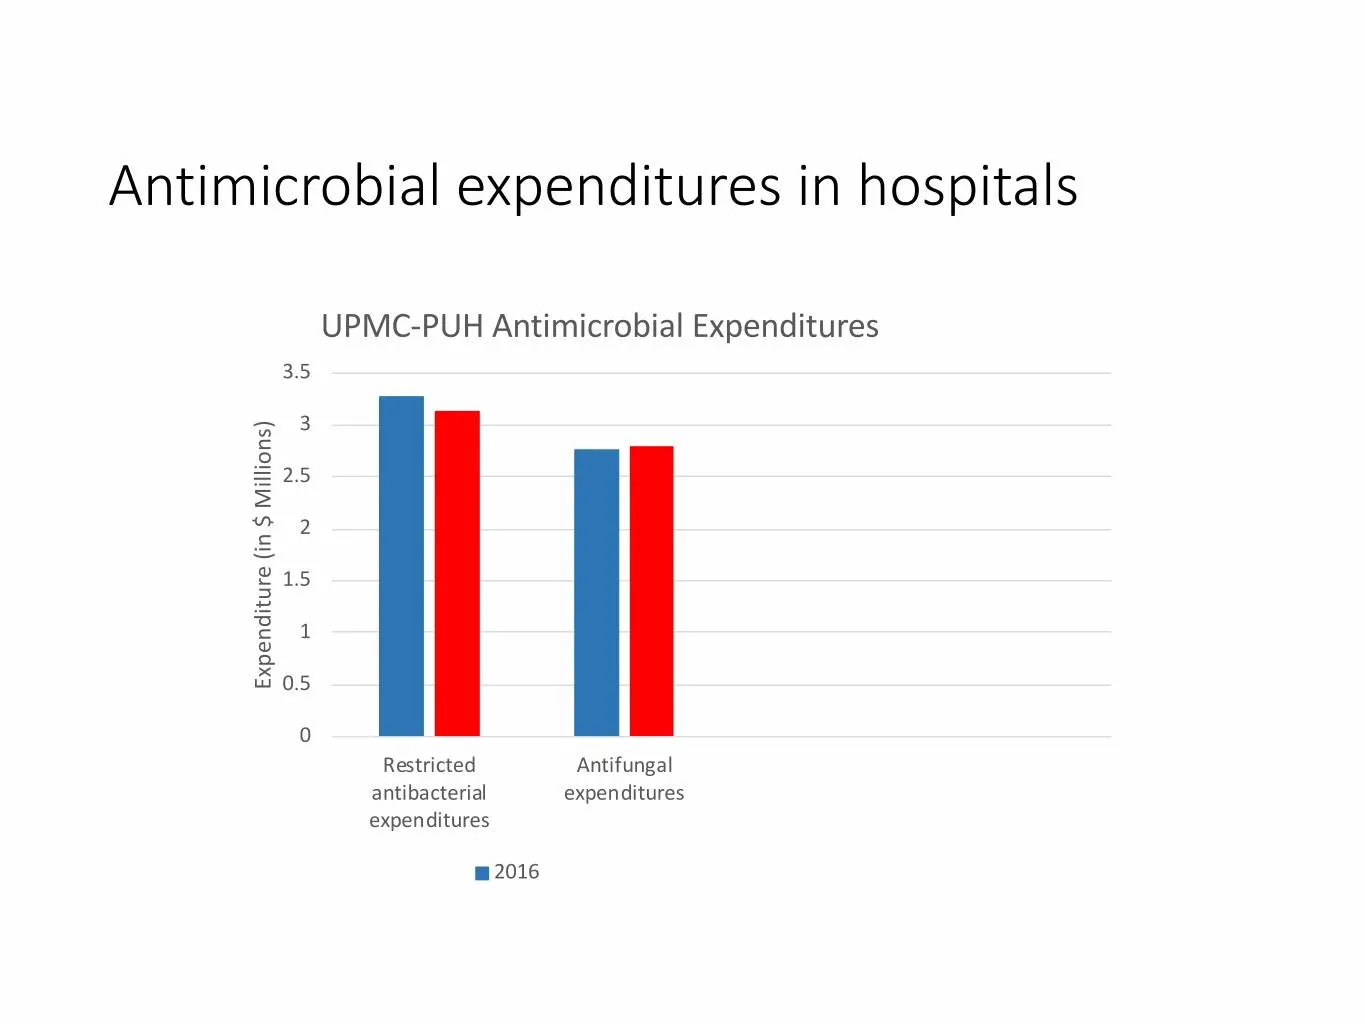
Antimicrobial expenditures in hospitals UPMC-PUH Antimicrobial Expenditures 3.5 3 2.5 2 1.5 1 Expenditure (in $ Millions) $ (in Expenditure 0.5 0 Restricted Antifungal antibacterial expenditures expenditures 2016

Slide 33: Why do hospitals spend so much on antifungals?
Why do hospitals spend so much on antifungals?

Slide 34: Why do hospitals spend so much on antifungals?
Why do hospitals spend so much on antifungals? 1. Patients often receive antifungal prophylaxis and treatment for weeks to months • Organ transplant recipients at UPMC receive 1-4 months of prophylaxis • Invasive aspergillosis and other mold infections are usually treated “for a minimum of 6-12 week

Slide 35: Why do hospitals spend so much on antifungals?
Why do hospitals spend so much on antifungals? 1. Patients often receive antifungal prophylaxis and treatment for weeks to months • Organ transplant recipients at UPMC receive 3-4 months of prophylaxis • Invasive aspergillosis and other mold infections are usually treated “for a minimum of 6-12 week
Slide 36: Why do hospitals spend so much on antifungals?
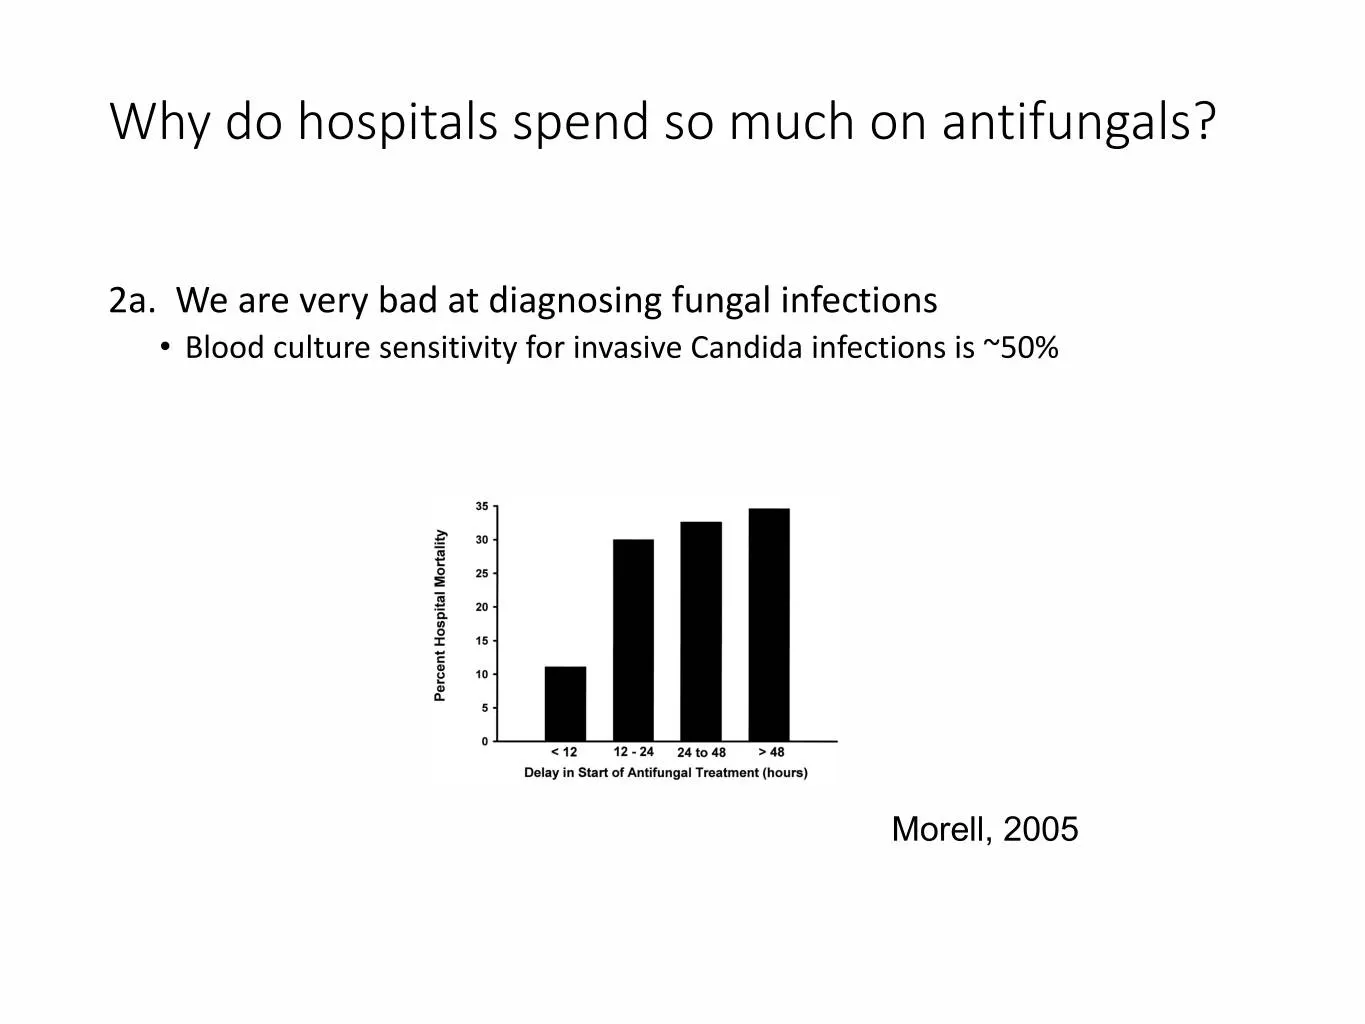
Why do hospitals spend so much on antifungals? 2a. We are very bad at diagnosing fungal infections • Blood culture sensitivity for invasive Candida infections is ~50% Morell, 2005

Slide 37: Why do hospitals spend so much on antifungals?
Why do hospitals spend so much on antifungals? 2b. Empiric and pre-emptive treatment are common • Empiric, pre-emptive and prophylactic antifungal use dwarfs treatment of documented infections Many hospitalized patients are at-risk for fungal infections • It’s not just cancer patients and transplant

Slide 38: Why do hospitals spend so much on antifungals?
Why do hospitals spend so much on antifungals? 2b. Empiric and pre-emptive treatment are common • Empiric, pre-emptive and prophylactic antifungal use exceeds treatment of documented infections 3. Many hospitalized patients are at-risk for fungal infections • It’s not just cancer patients and transp

Slide 39: What are unmet needs in treatment of invasive fungal disease?
What are unmet needs in treatment of invasive fungal disease?

Slide 40: What are unmet needs in treatment of invasive fungal disease?
What are unmet needs in treatment of invasive fungal disease? • We need better drugs! • Mortality rates (12 m) • Stem cell transplant • 75% molds • 67% Candida • Organ transplant • 40% molds • 33% Candida bad at diagnosing fungal infections • Blood culture sensitivity for invasive Candida infections

Slide 41: Echinocandins are agents of choice in invasive candidiasis
Echinocandins are agents of choice in treatment of invasive candidiasis • Mortality rate (30 d) is still 27% 41

Slide 42: Echinocandins are agents of choice in invasive candidiasis
Echinocandins are agents of choice in treatment of invasive candidiasis • Mortality rate (30 d) is still 27% WHY? 42
Slide 43: Antifungal levels in tissues
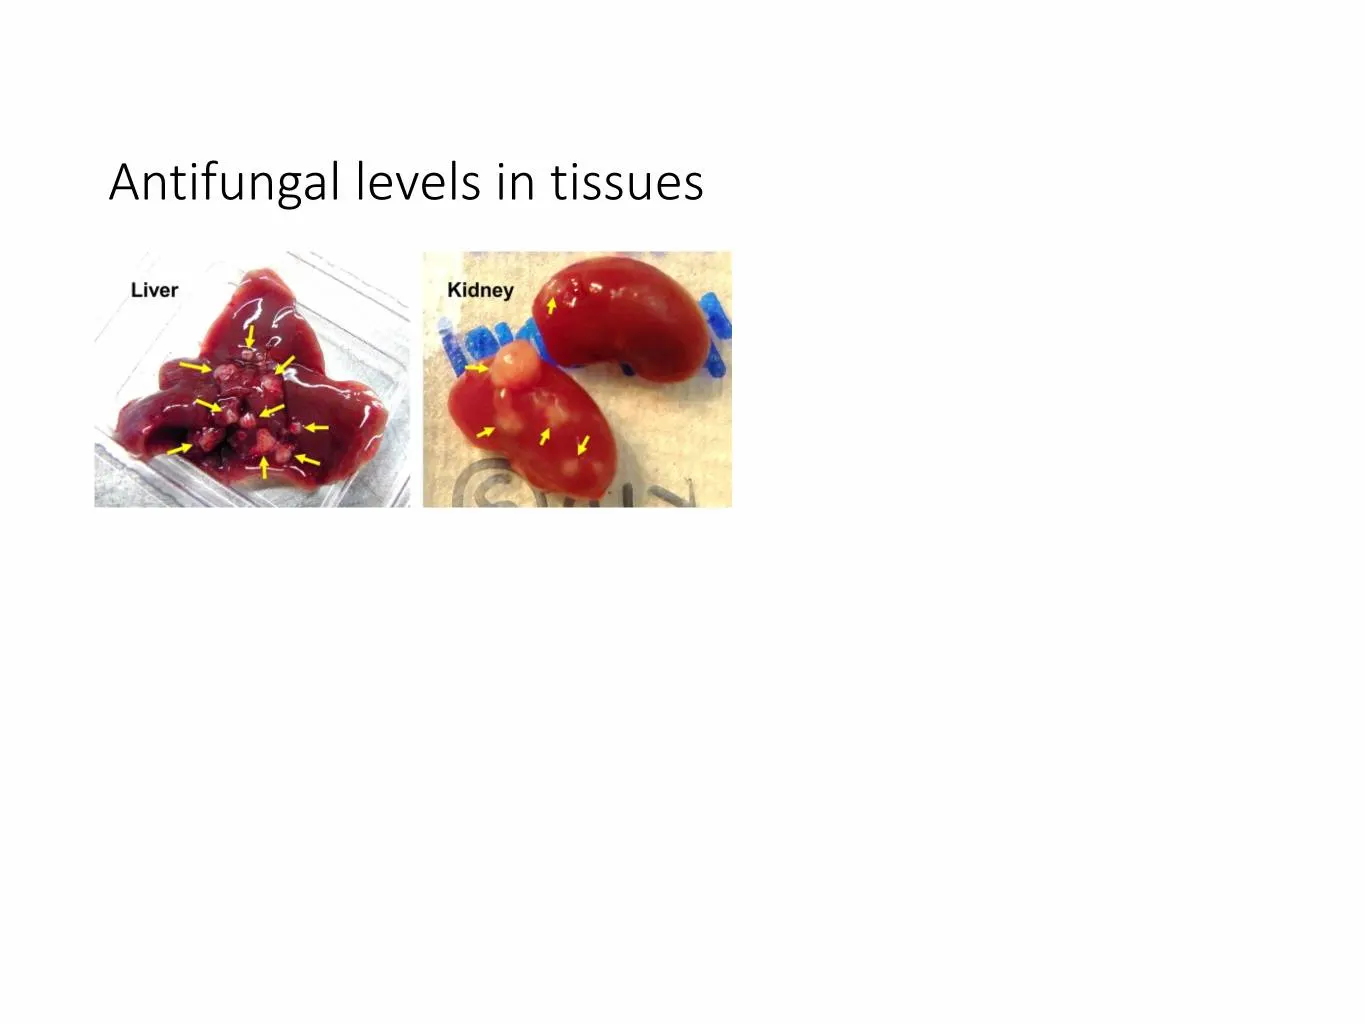
Antifungal levels in tissues
Slide 44: Antifungal levels in tissues
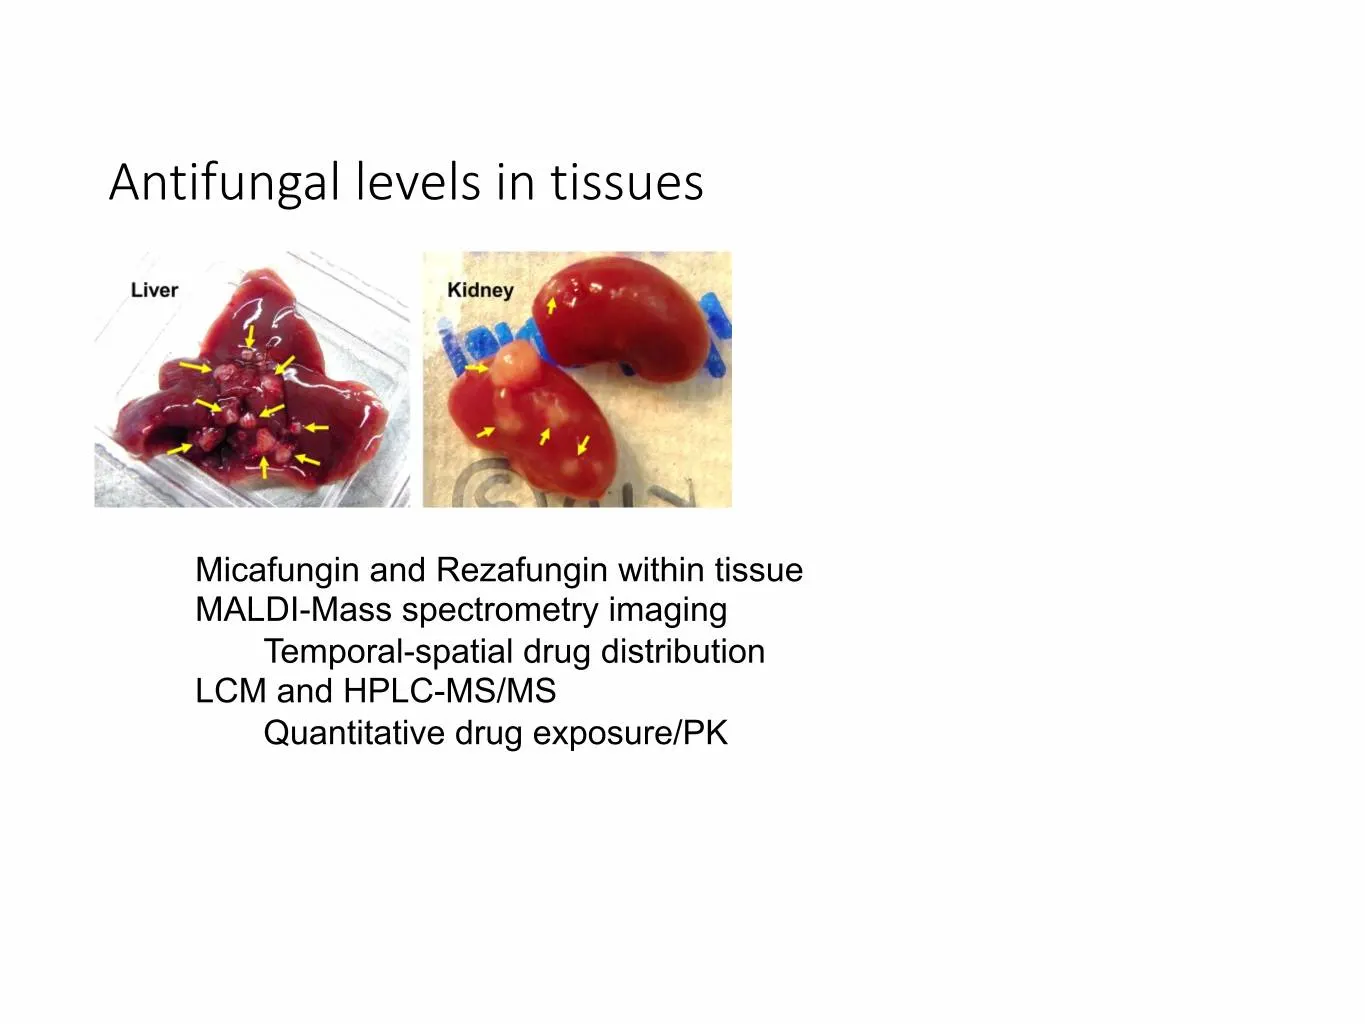
Antifungal levels in tissues Micafungin and Rezafungin within tissue MALDI-Mass spectrometry imaging Temporal-spatial drug distribution LCM and HPLC-MS/MS Quantitative drug exposure/PK
Slide 45: Antifungal levels in tissues
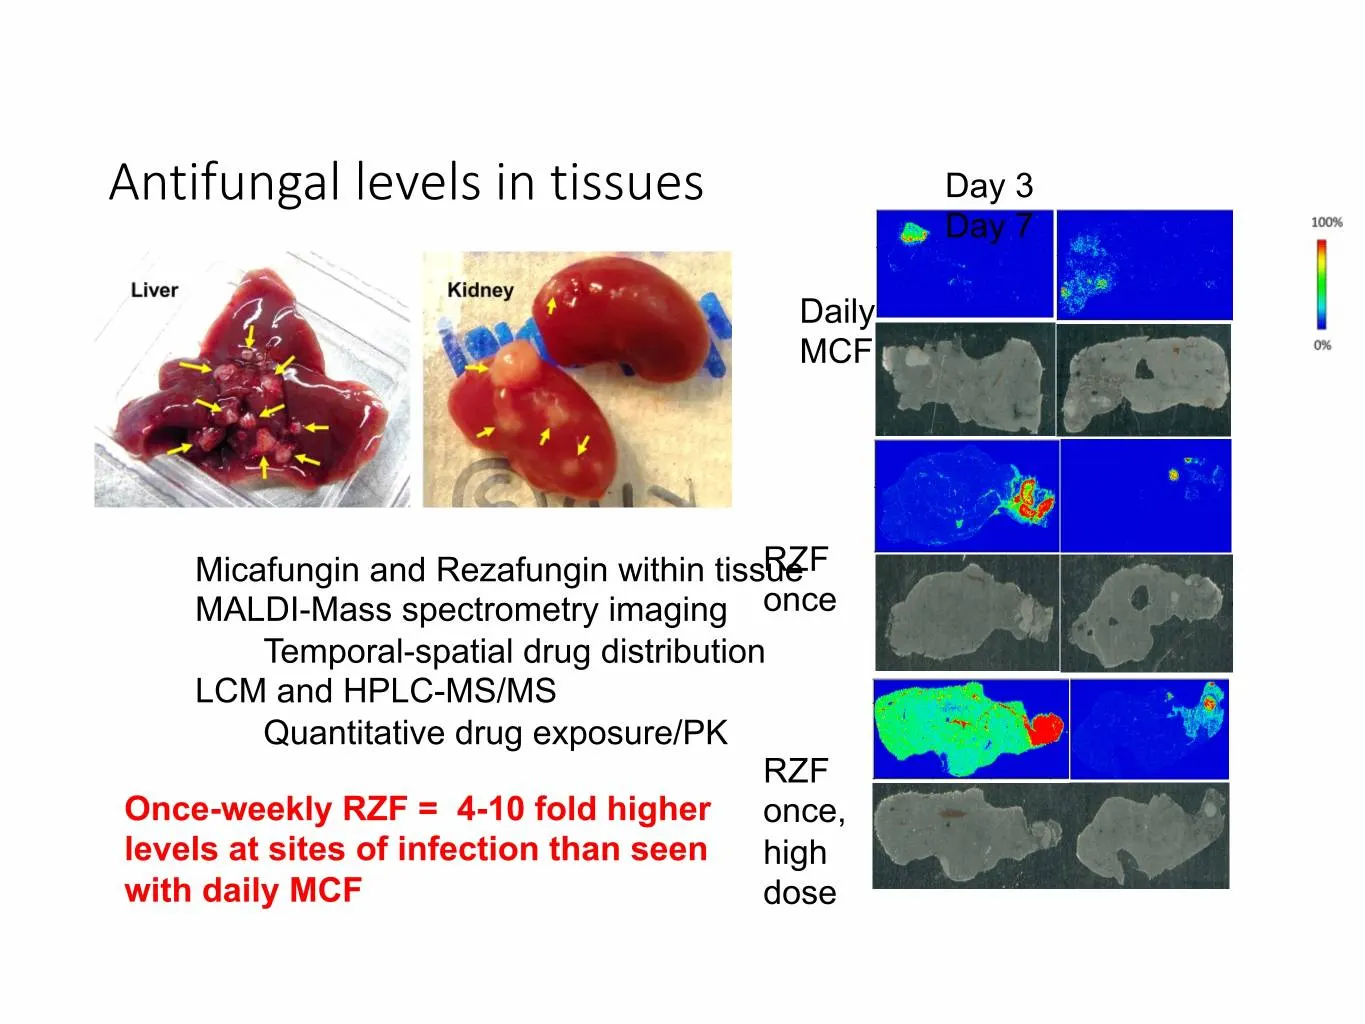
Antifungal levels in tissues Day 3 Day 7 Daily MCF Micafungin and Rezafungin within tissueRZF MALDI-Mass spectrometry imaging once Temporal-spatial drug distribution LCM and HPLC-MS/MS Quantitative drug exposure/PK RZF Once-weekly RZF = 4-10 fold higher once, levels at sites of infection than seen h

Slide 46: What does Rezafungin offer?
What does Rezafungin offer? • Superior penetration and drug levels at tissue sites of infection, compared to current standard of care • Once-weekly dosing, excellent safety and drug-drug interaction profiles • Changing epidemiology of Candida

Slide 47: What does Rezafungin offer?
What does Rezafungin offer? • Presents opportunities for new treatment paradigms • Organ transplant • Below the diaphragm transplant • Prophylaxis • Definitive treatment of candidiasis • Above the diaphragm transplants • Alternative to azoles • Azole intolerance in 20-40%

Slide 48: What does Rezafungin offer?
What does Rezafungin offer? • Presents opportunities for new treatment paradigms • ICUs, Pre-emptive, empiric treatment • Need: Time to sort things out • Once-weekly dosing allows you several days to make definitive diagnoses, while not tying up an intravenous line

Slide 49: What does Rezafungin offer?
What does Rezafungin offer? • Presents opportunities for new treatment paradigms • Definitive treatment • Inpatient need: Effectiveness, safety and convenience • Post-discharge need: Effective and convenient dosing strategies in outpatient setting • May be able to administer a terminal dose prior to

Slide 50: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 51: Unmet Needs in Heme - BMT
Unmet Needs in Heme - BMT Kieren Marr MD, MBA Professor and Vice Chair of Medicine for Innovation in Healthcare Implementation Director, Transplant and Oncology Infectious Diseases 51 51
Slide 52: Modern Medicine Leverages Immune Manipulation to Treat Many Diseases
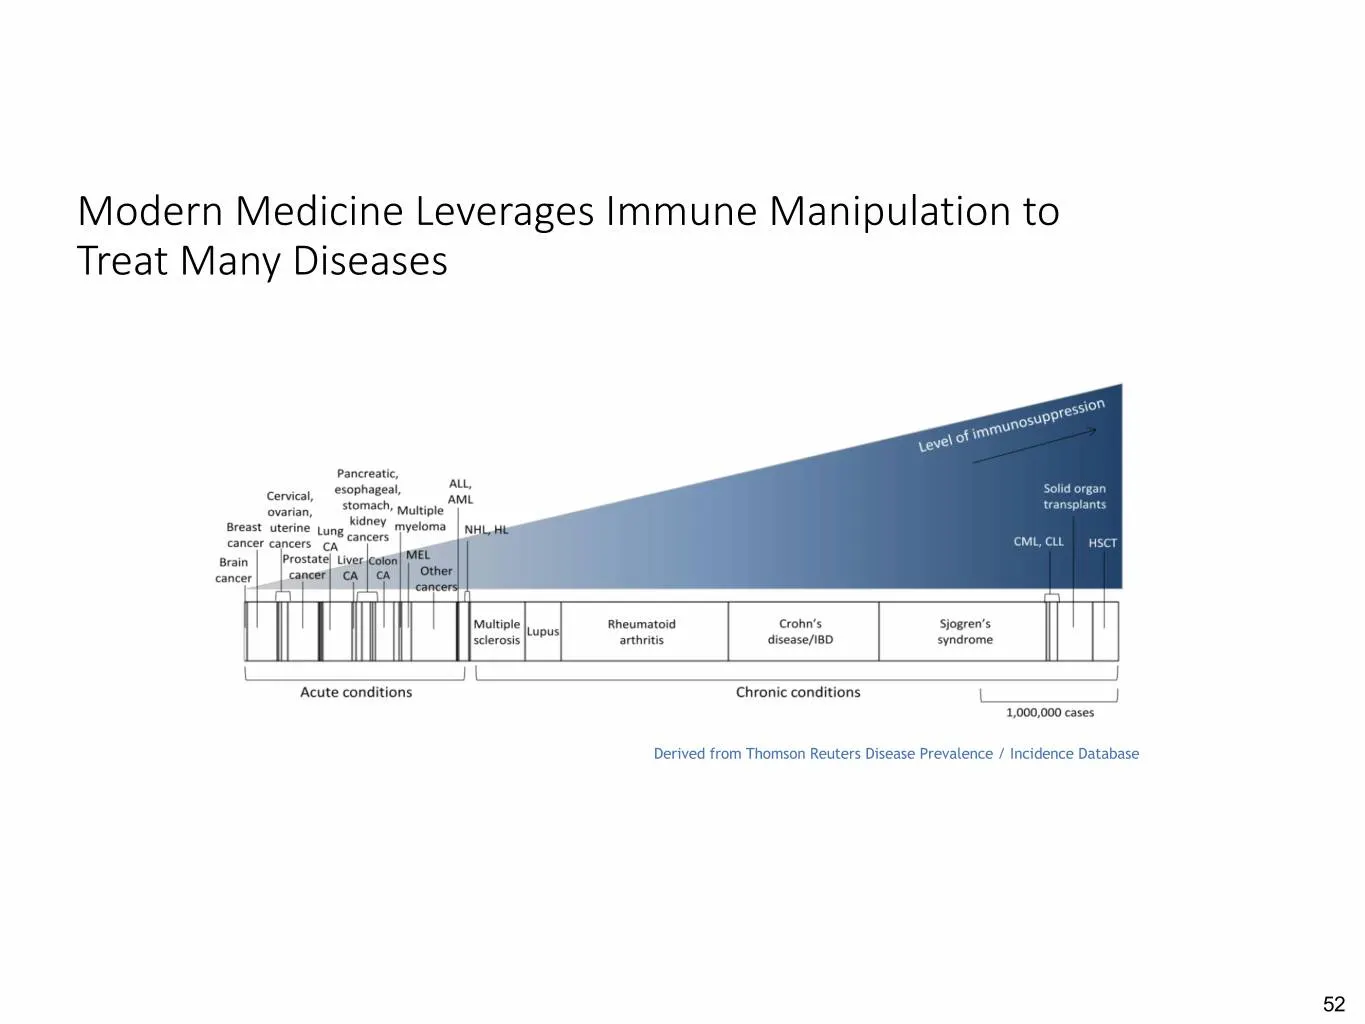
Modern Medicine Leverages Immune Manipulation to Treat Many Diseases Derived from Thomson Reuters Disease Prevalence / Incidence Database 52
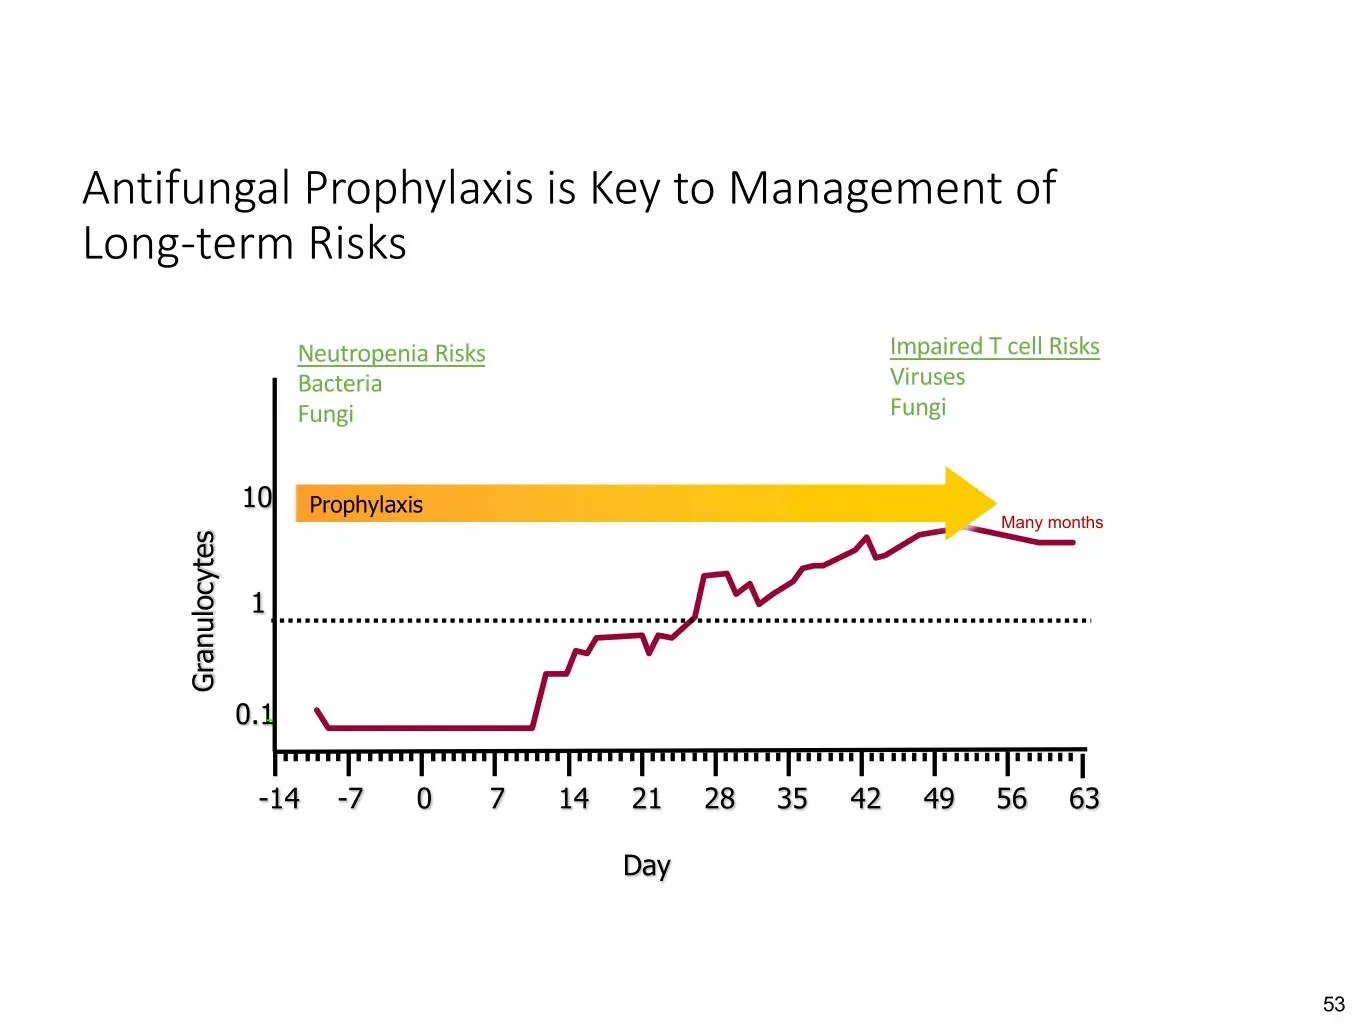
Slide 53: Antifungal Prophylaxis is Key to Management of Long-term Risks
Antifungal Prophylaxis is Key to Management of Long-term Risks Neutropenia Risks Impaired T cell Risks Bacteria Viruses Fungi Fungi 10 Prophylaxis Many months 1 Granulocytes 0.1 -14 -7 0 7 14 21 28 35 42 49 56 63 Day 53
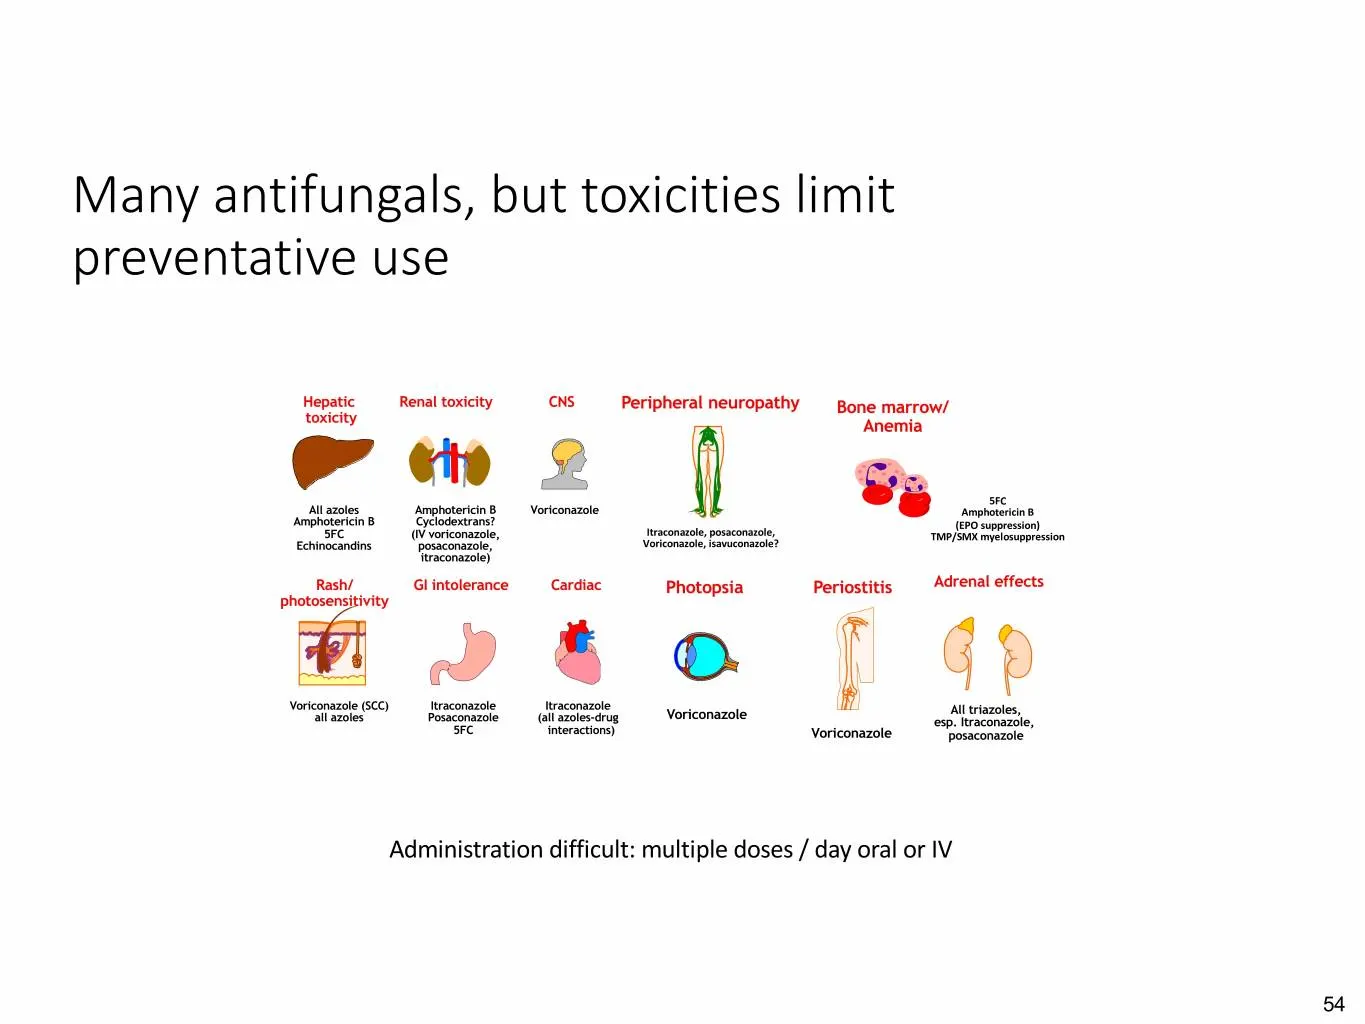
Slide 54: Many antifungals, but toxicities limit preventative use
Many antifungals, but toxicities limitPeripheral neuropathy Periostitis preventative use Voriconazole Peripheral neuropathy Periostitis Hepatic Renal toxicity CNS Peripheral neuropathy PeriostitisBone marrow/ Adrenal effects toxicity Anemia 5FC All azoles Amphotericin B Voriconazole AmphotericinVori
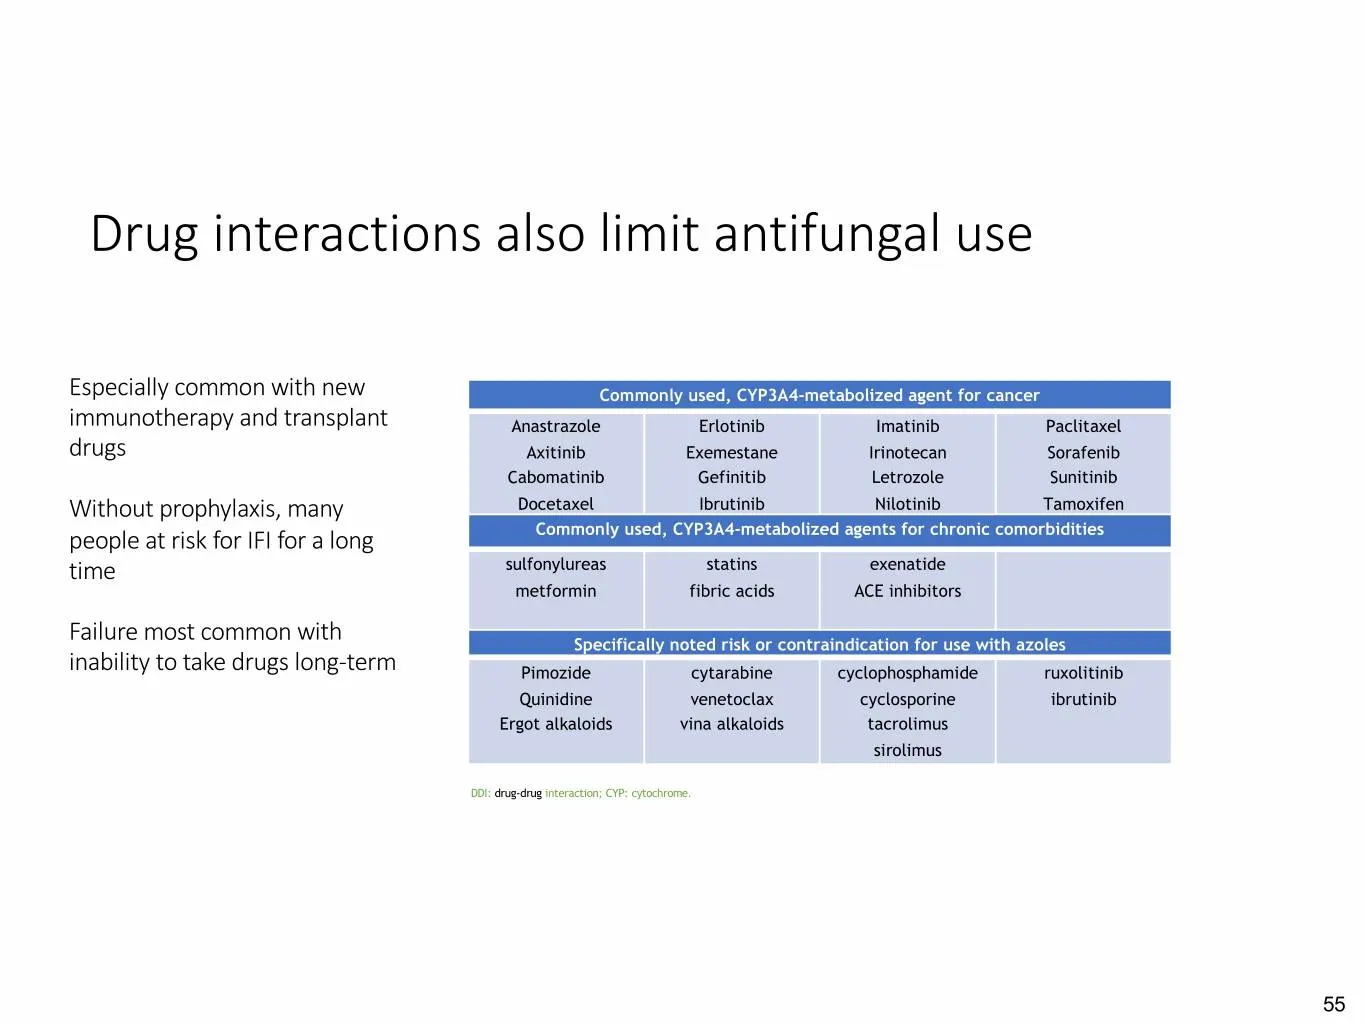
Slide 55: Drug interactions also limit antifungal use
Drug interactions also limit antifungal use Especially common with new Commonly used, CYP3A4-metabolized agent for cancer immunotherapy and transplant Anastrazole Erlotinib Imatinib Paclitaxel drugs Axitinib Exemestane Irinotecan Sorafenib Cabomatinib Gefinitib Letrozole Sunitinib Without prophylaxi

Slide 56: Unmet Needs in Hematology are Growing
Unmet Needs in Hematology are Growing New chemotherapic agents already in use • A new drug or coming in Hematology introduced every 3.5 AML ALL 1. FLT3-inhibitors (Quizartinib, Midostaurin, weeks 1. Monoclonal antibodies Sorafenib) a. anti-CD19 (Blinatuzumab) 2. Monoclonal antibodies anti-CD33 b. an

Slide 57: Unmet Needs
Unmet Needs • Long-term alternative with broad coverage for BMT • Anti-Candida, Anti-Aspergillus and Anti-PJP • Antifungal drug with broad coverage in people who are receiving one of many anti-cancer drugs metabolized by P450 system. Especially common for: • Leukemias • Lymphomas • Expanding numbers

Slide 58: Rezafungin One-drug Antifungal Prophylaxis
Rezafungin One-drug Antifungal Prophylaxis • Once – weekly infusion • No liver cytochrome P450 interactions • Preclinical, clinical activity against Candida spp. (most common during neutropenia) • Preclinical activity against Aspergillus & Pneumocystis (most common during impaired T cell responses)

Slide 59: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 60: Gaps in the prevention of influenza
Gaps in the prevention of influenza Allison McGeer, MSc, MD, FRCPC, FAMMI, FSHEA Sinai Health System University of Toronto 60

Slide 61: 61
61
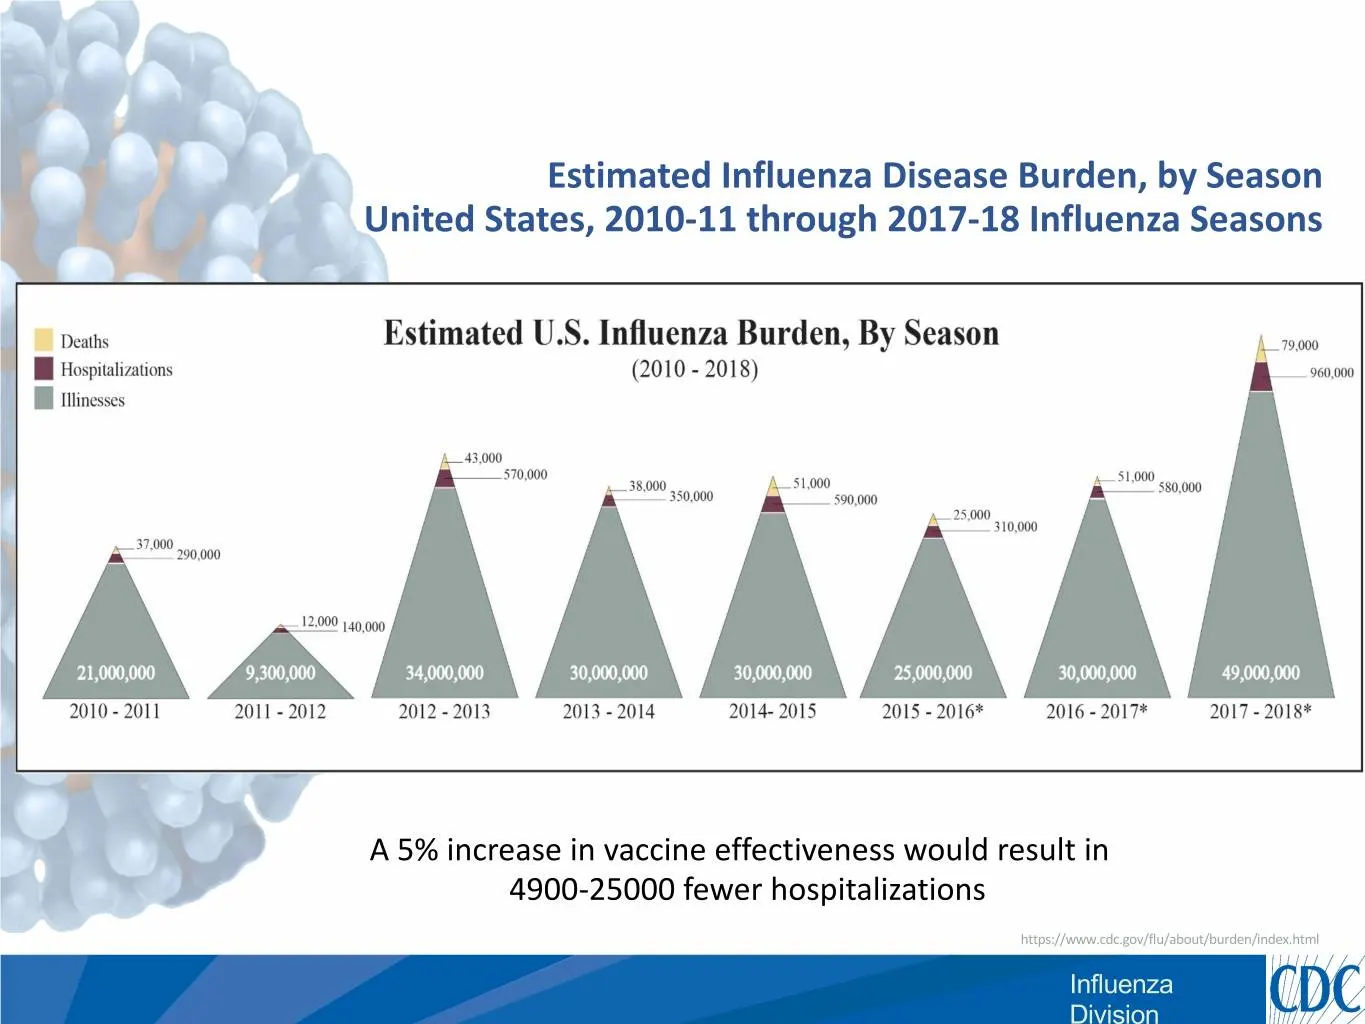
Slide 62: Estimated Influenza Disease Burden, by Season
Estimated Influenza Disease Burden, by Season United States, 2010-11 through 2017-18 Influenza Seasons A 5% increase in vaccine effectiveness would result in 4900-25000 fewer hospitalizations https://www.cdc.gov/flu/about/burden/index.html Influenza Division
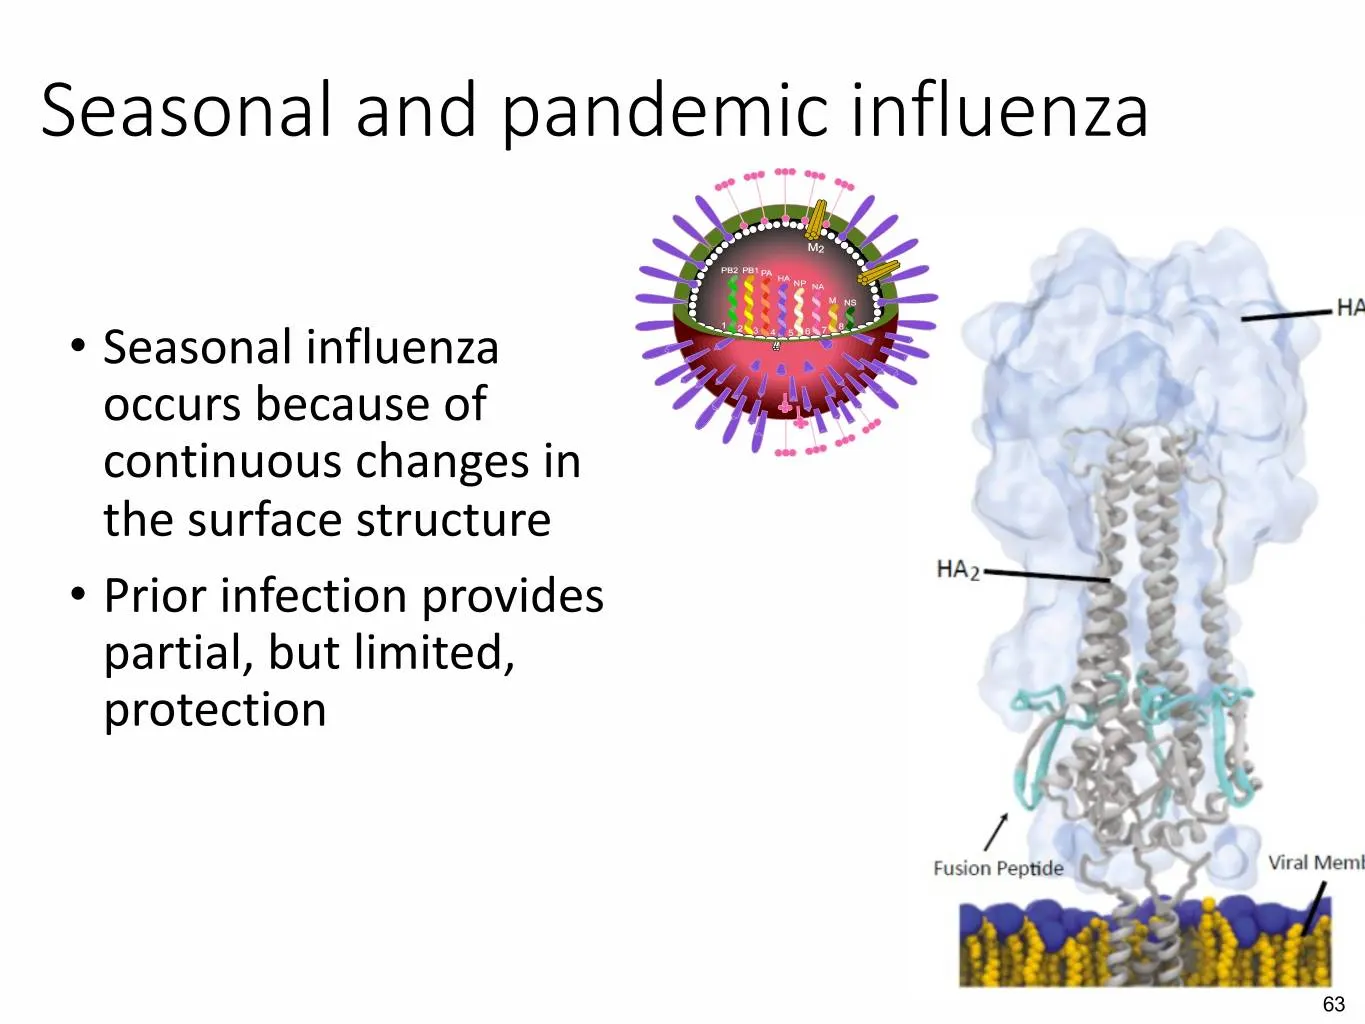
Slide 63: Seasonal and pandemic influenza
Seasonal and pandemic influenza • Seasonal influenza occurs because of continuous changes in the surface structure • Prior infection provides partial, but limited, protection 63
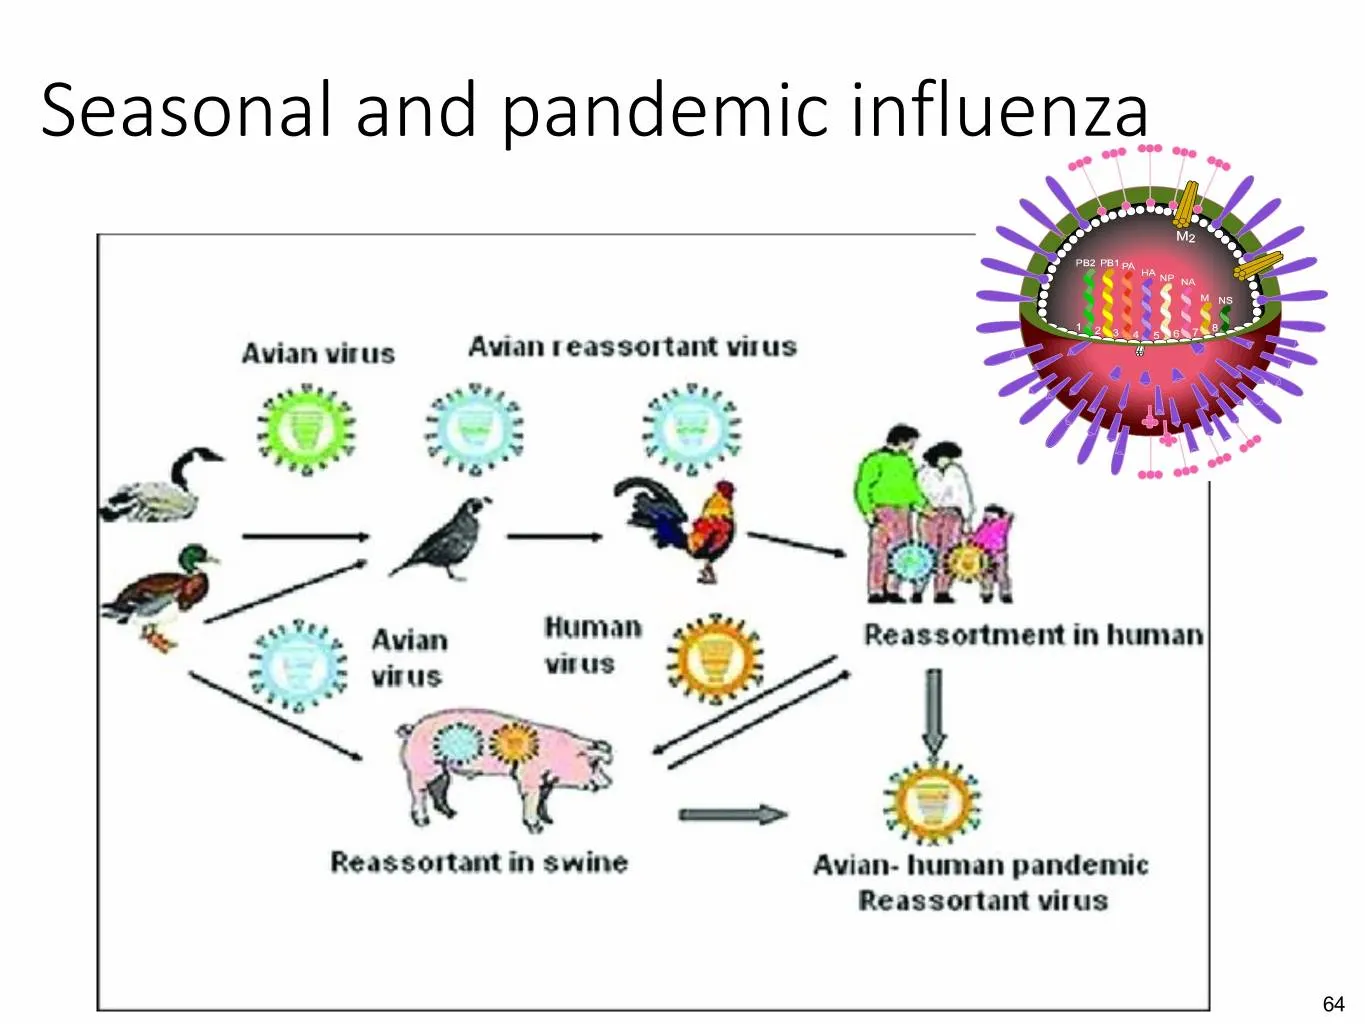
Slide 64: Seasonal and pandemic influenza
Seasonal and pandemic influenza 64
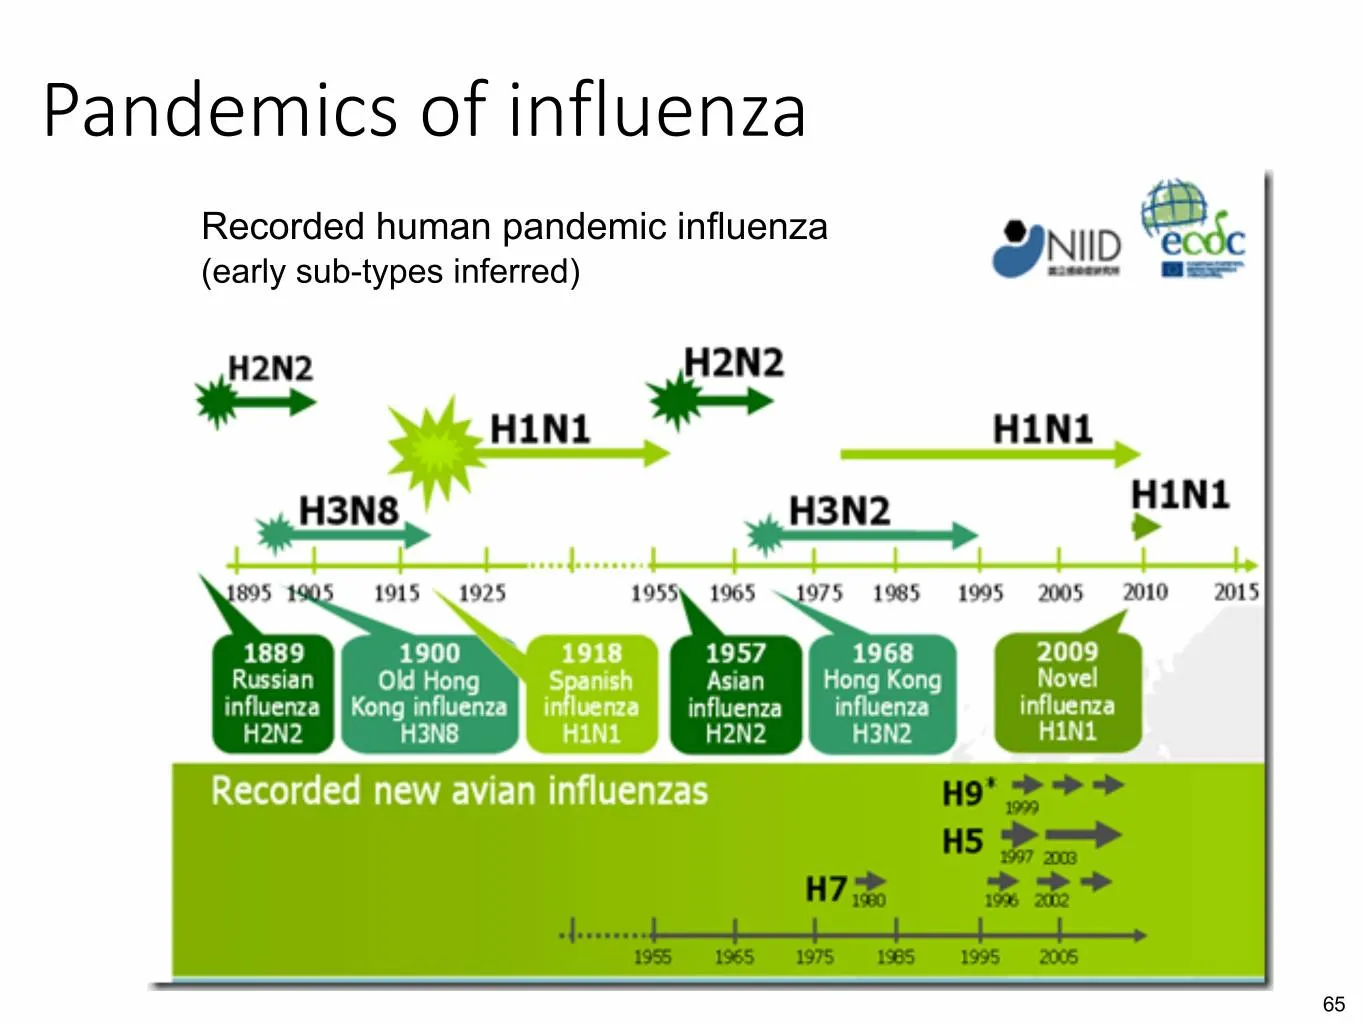
Slide 65: Pandemics of influenza
Pandemics of influenza Recorded human pandemic influenza (early sub-types inferred) 65
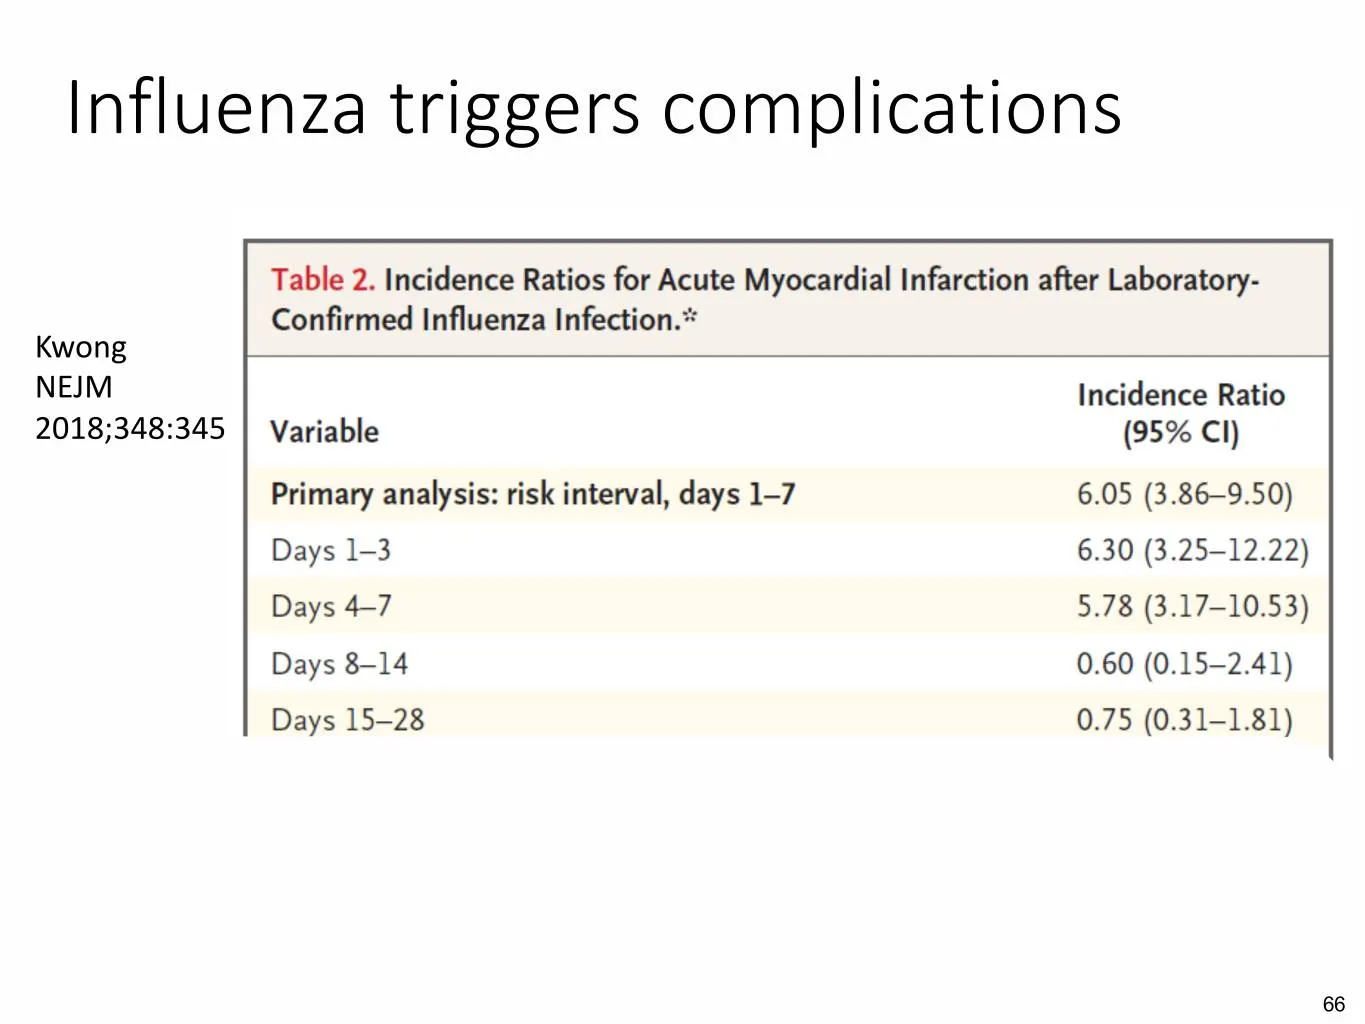
Slide 66: Influenza triggers complications
Influenza triggers complications Kwong NEJM 2018;348:345 66

Slide 67: Influenza treatment
Influenza treatment • Current: • Neuraminidase inhibitors • Baloxavir marboxil (cap-dependent endonuclease inhibitor) • New • Several molecules and monoclonal antibodies in phase 2 trials • Issues • Effectiveness • Cost • Delivery systems • Antibiotic resistance 67

Slide 68: Seasonal influenza prevention
Seasonal influenza prevention • Current: • Inactivated influenza vaccines: dose, adjuvant • Live attenuated vaccines • New • Broad spectrum vaccines (M-001 in phase 3 trial) • Issues • Vaccine efficacy 68

Slide 69: Pandemic influenza prevention
Pandemic influenza prevention • Current • Antivirals (?stockpiles) • New • Vaccines with shorter delay to production • Broad spectrum vaccines • Issues • Investing in prevention • How much shorter? • How broad spectrum? 69

Slide 70: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 71: Commercial Outlook: Rezafungin, Cloudbreak - Influenza
Commercial Outlook Rezafungin Cloudbreak - Influenza 71

Slide 72: Disclaimer
Disclaimer Certain information about sample revenue on the following slides (e.g. slide #s 80-85 and 92-94) include projections and other forward-looking information based on our estimates and assumptions, including estimated patient populations, market share and pricing assumptions, which are made
Slide 73: Antifungals are historically big drugs globally
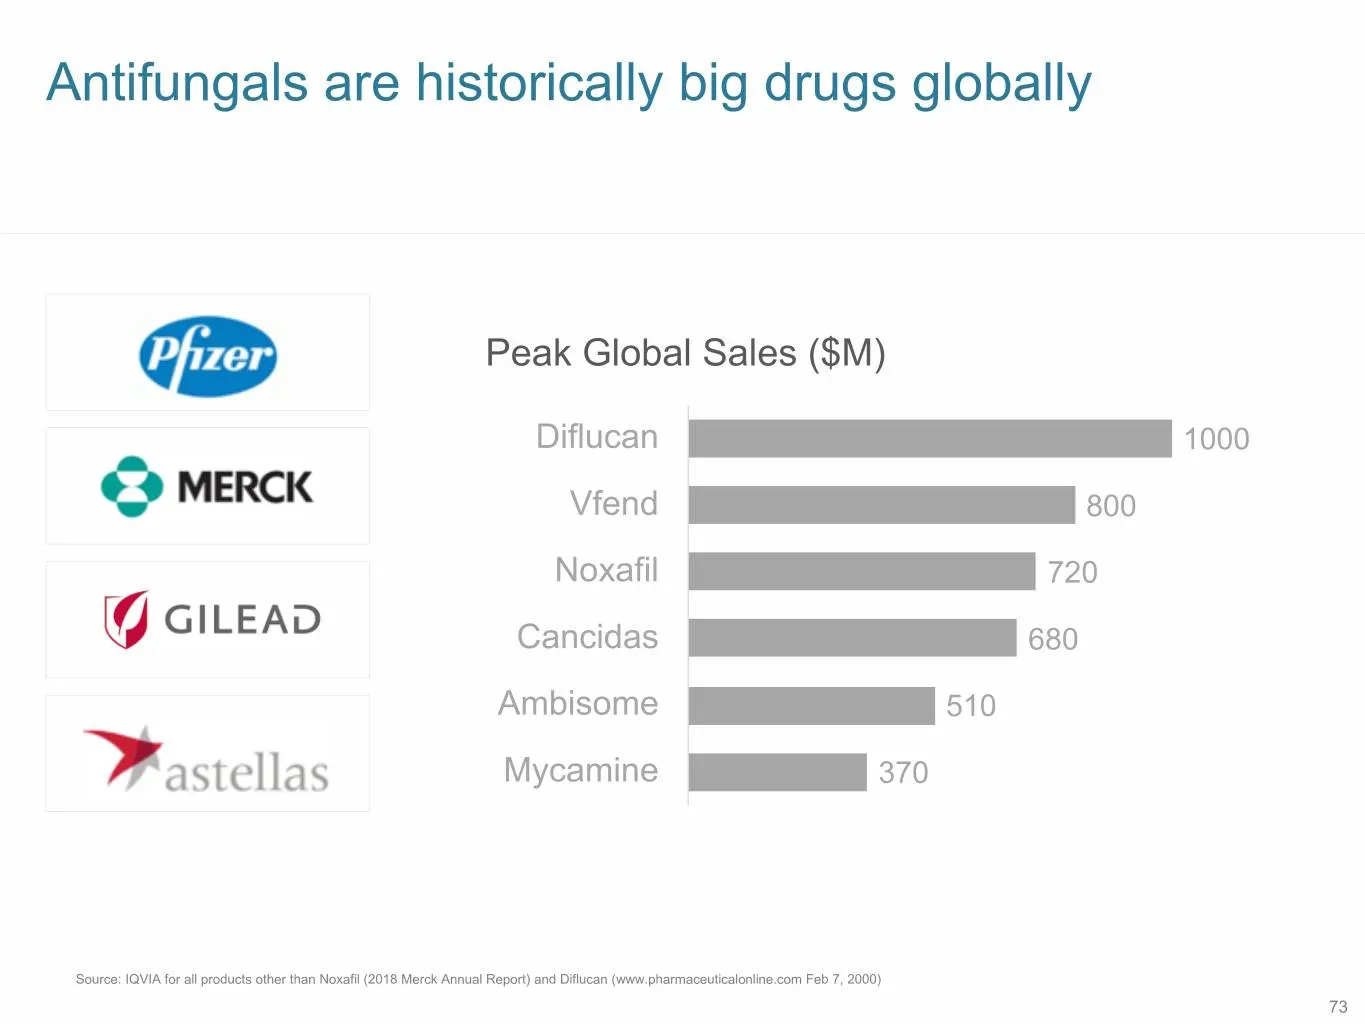
Antifungals are historically big drugs globally Peak Global Sales ($M) Diflucan 1000 Vfend 800 Noxafil 720 Cancidas 680 Ambisome 510 Mycamine 370 Source: IQVIA for all products other than Noxafil (2018 Merck Annual Report) and Diflucan (www.pharmaceuticalonline.com Feb 7, 2000) 73

Slide 74: Antifungal drug development has dwindled
Antifungal drug development has dwindled Number of New Antifungals 5 5 1 1980 1990 2000 2010 2020 amphotericin POLYENES lipid forms (3) itraconazole posaconazole AZOLES fluconazole voriconazole micafungin ECHINOCANDINS caspofungin anidulafungin 74
Slide 75: Recent antifungal launch outpaces antibacterials despite limitations
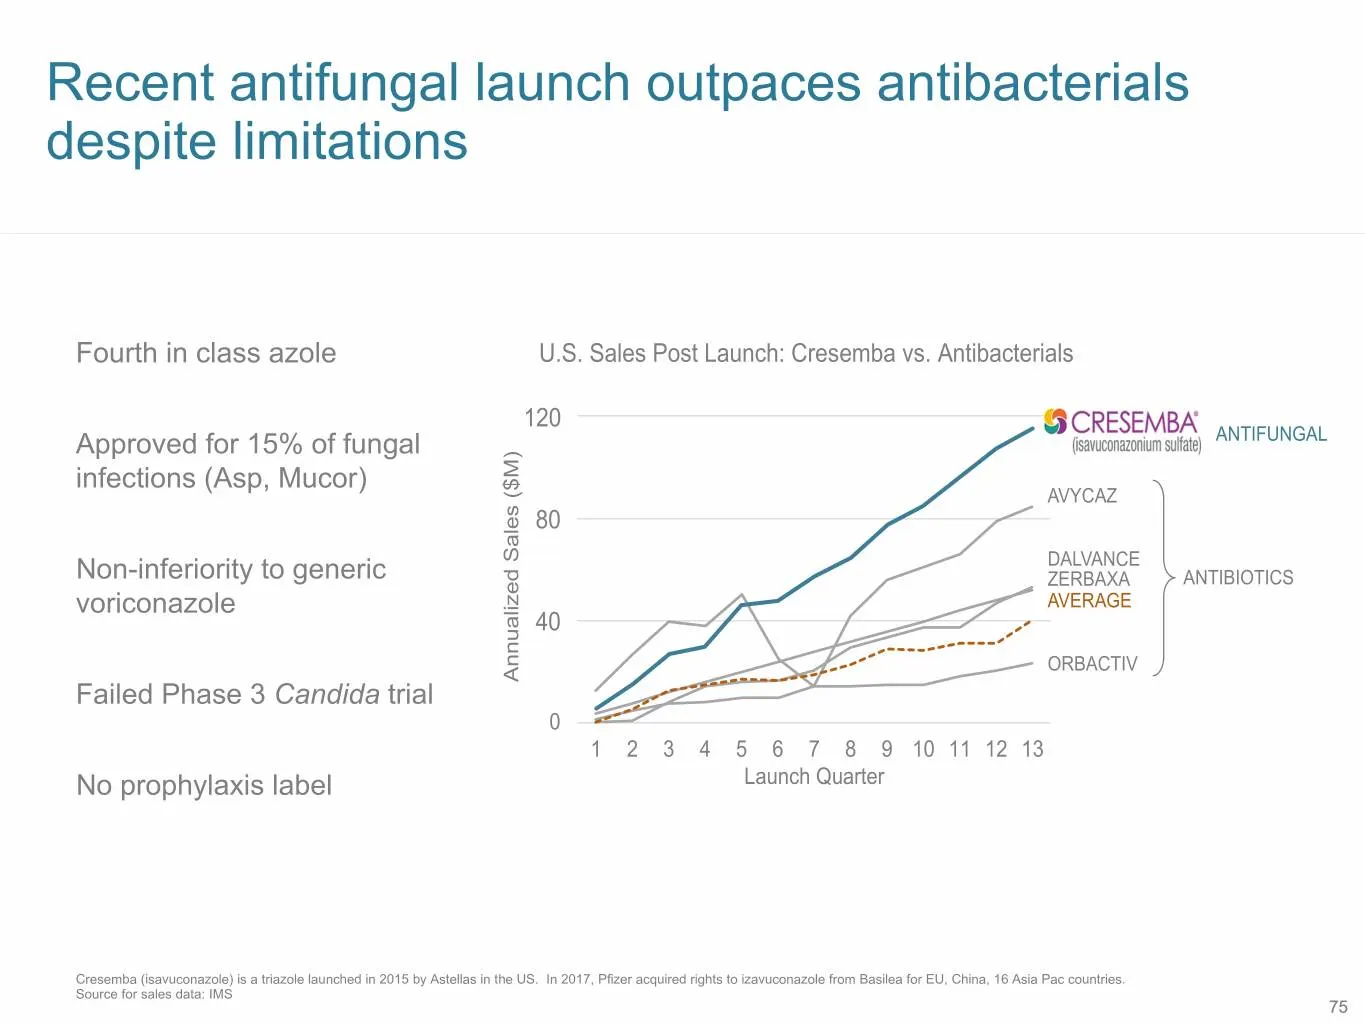
Recent antifungal launch outpaces antibacterials despite limitations Fourth in class azole U.S. Sales Post Launch: Cresemba vs. Antibacterials 12030 Approved for 15% of fungal ANTIFUNGAL infections (Asp, Mucor) AVYCAZ 8020 DALVANCE Non-inferiority to generic ZERBAXA ANTIBIOTICS voriconazole AVERAGE
Slide 76: Echinocandins are constrained today
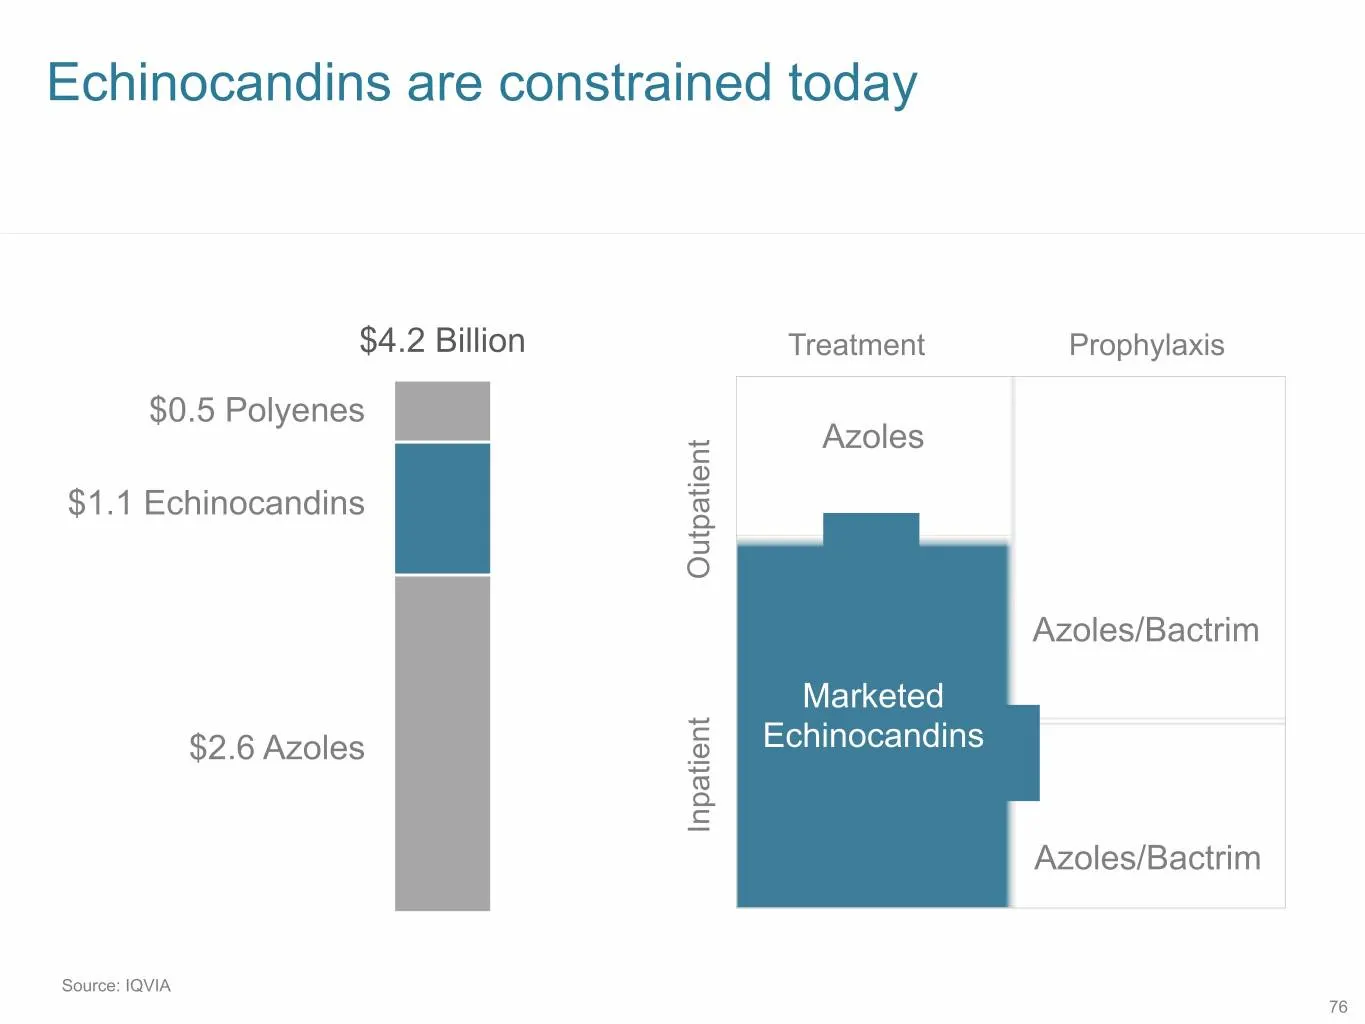
Echinocandins are constrained today $4.2 Billion Treatment Prophylaxis $0.5 Polyenes Azoles $1.1 Echinocandins Outpatient Azoles/Bactrim Marketed $2.6 Azoles Echinocandins Inpatient Azoles/Bactrim Source: IQVIA 76
Slide 77: An approval with non-inferiority enables rezafungin
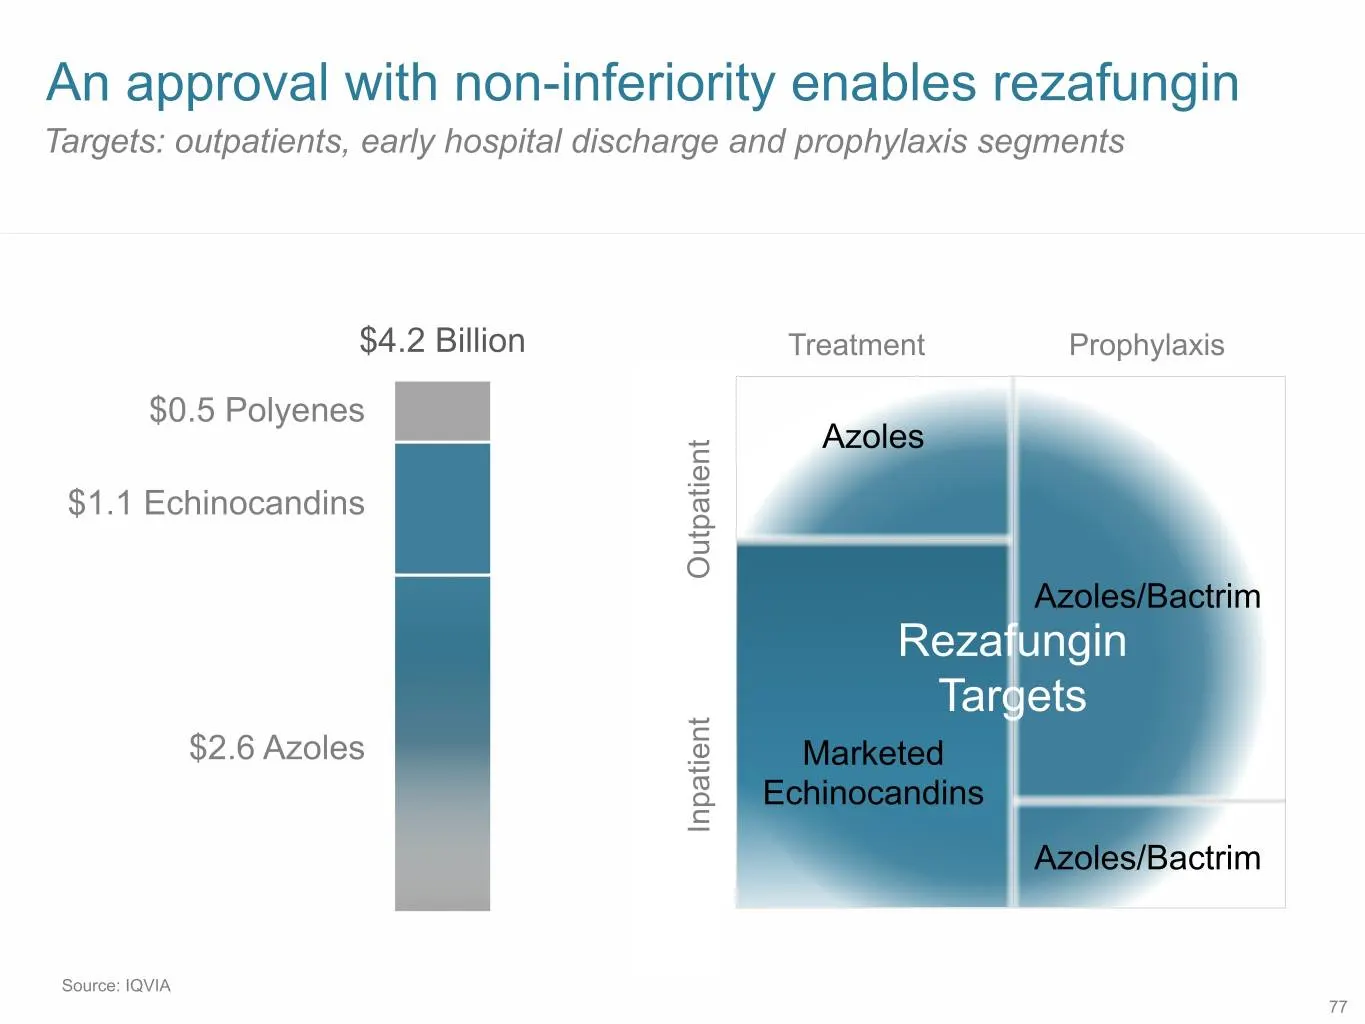
An approval with non-inferiority enables rezafungin Targets: outpatients, early hospital discharge and prophylaxis segments $4.2 Billion Treatment Prophylaxis $0.5 Polyenes Azoles $1.1 Echinocandins Outpatient Azoles/Bactrim Rezafungin Targets $2.6 Azoles Marketed Echinocandins Inpatient Azoles/Bact

Slide 78: The Rezafungin opportunity spans ID and hematology
The Rezafungin opportunity spans ID and hematology The $4.2 billion global antifungal market Infectious Disease Hematology Mostly Treatment Mostly Prophylaxis Cancidas (caspofungin) Noxafil (posaconazole) ~$700M global sales ~$700M global sales Source: Cancidas – IQVIA; Noxafil – 2018 Merck Annual R

Slide 79: Recent analogies for US sales of antifungals
Recent analogies for US sales of antifungals • Isavuconazole – Treatment Indications – Year 3 – $116M1 • Posaconazole – Prophylaxis Indications – Peak ~$360M2 1. IQVIA 2. IQVIA: 336M US sales in 2018. Internal estimate of ~360M in 2019, last full year before patent expiry 79
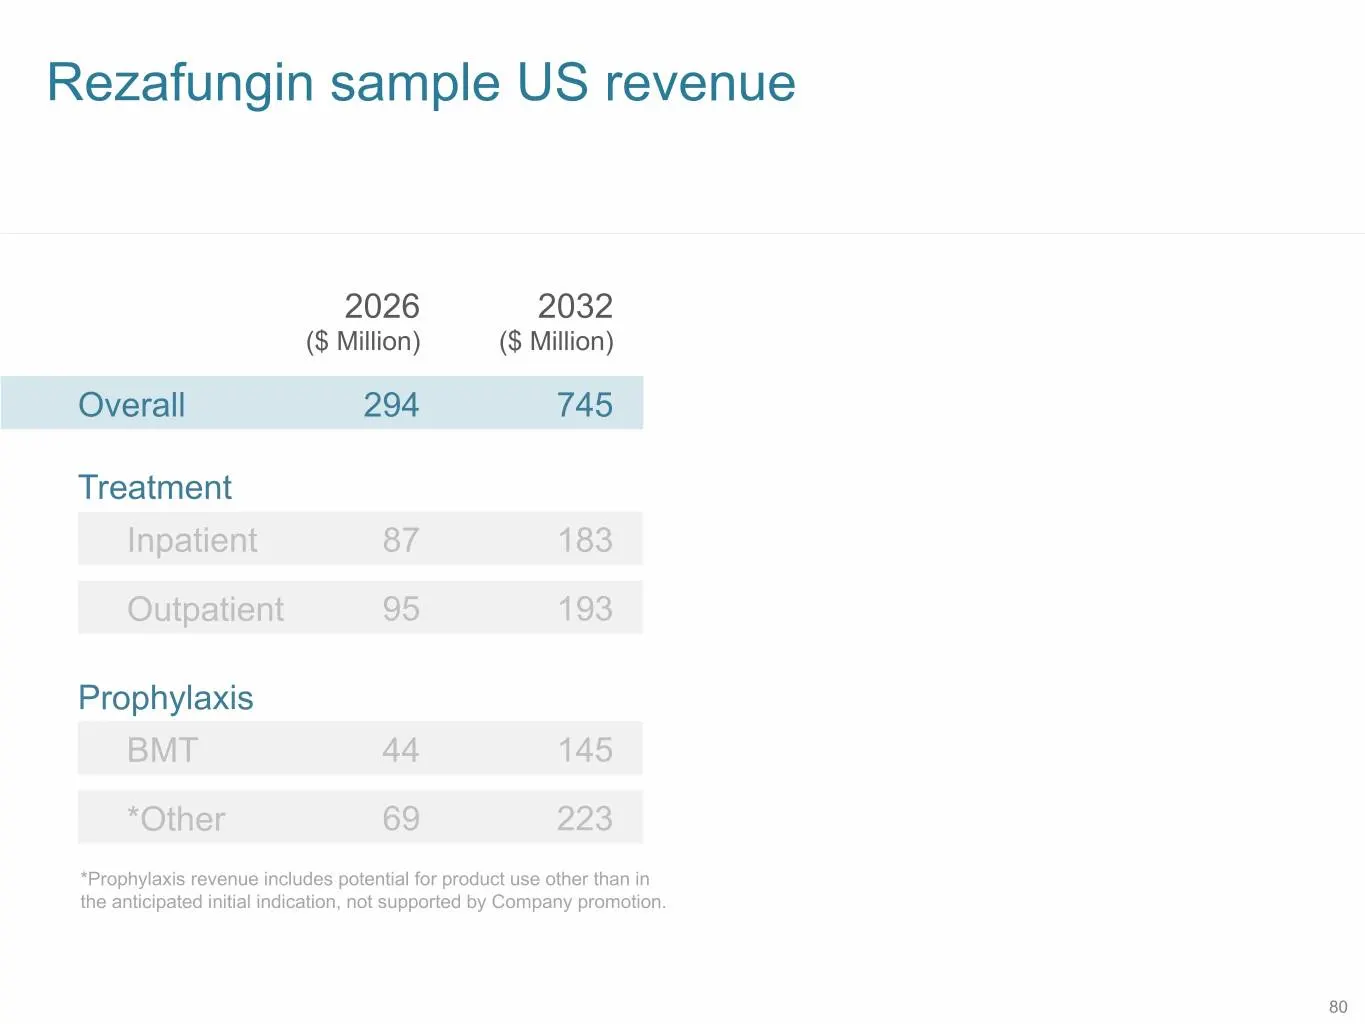
Slide 80: Rezafungin sample US revenue
Rezafungin sample US revenue 2026 2032 ($ Million) ($ Million) Overall 294 745 Treatment Inpatient 87 183 Outpatient 95 193 Prophylaxis BMT 44 145 *Other 69 223 *Prophylaxis revenue includes potential for product use other than in the anticipated initial indication, not supported by Company promotio
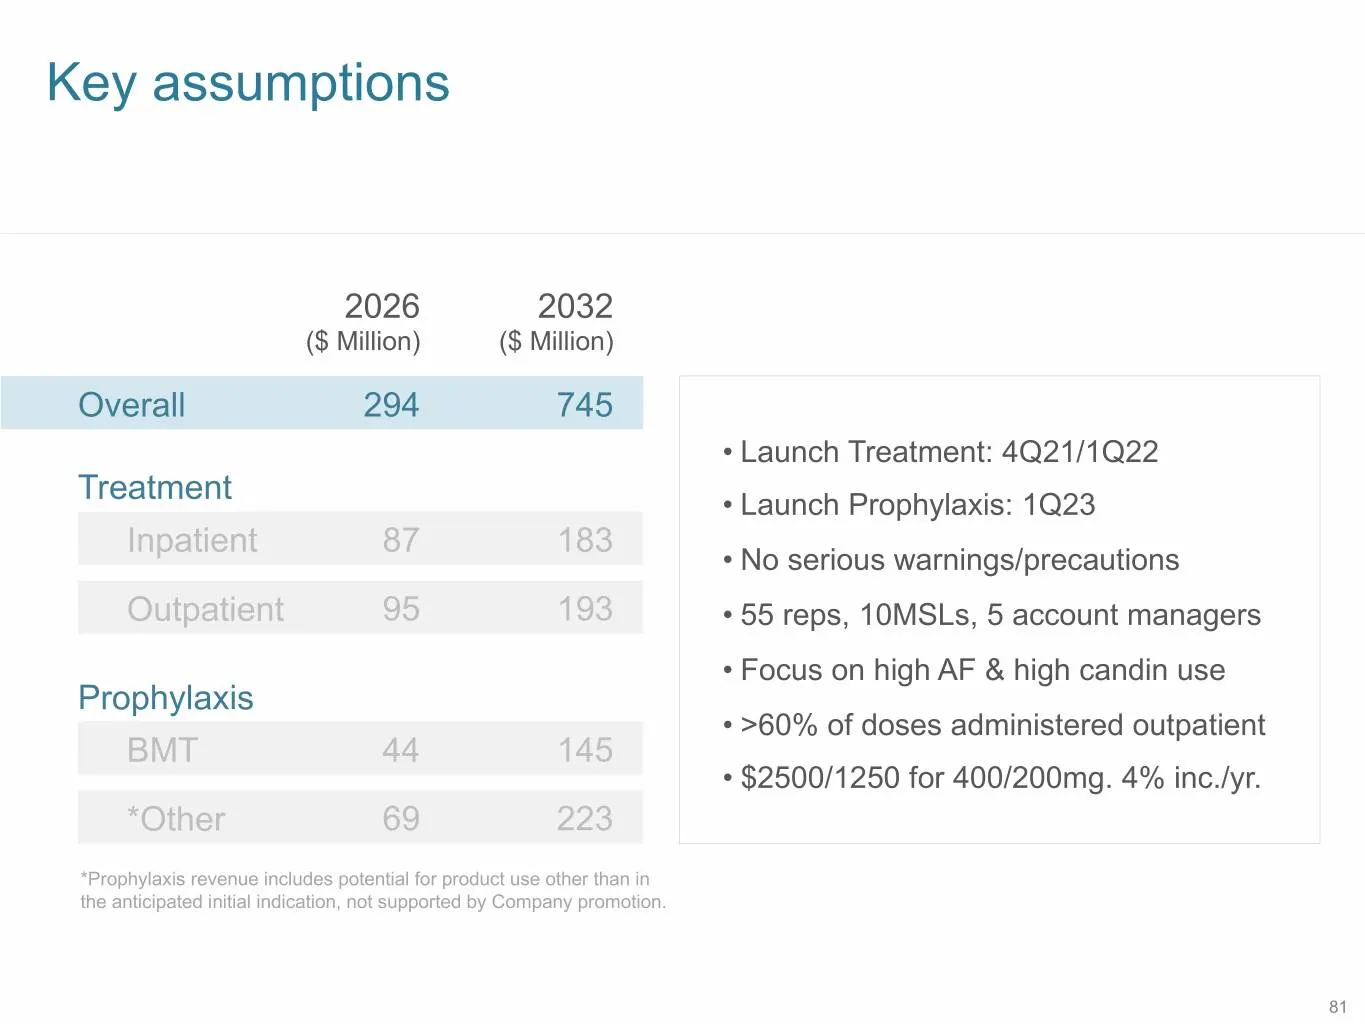
Slide 81: Key assumptions
Key assumptions 2026 2032 ($ Million) ($ Million) Overall 294 745 • Launch Treatment: 4Q21/1Q22 Treatment • Launch Prophylaxis: 1Q23 Inpatient 87 183 • No serious warnings/precautions Outpatient 95 193 • 55 reps, 10MSLs, 5 account managers • Focus on high AF & high candin use Prophylaxis • >60% of d
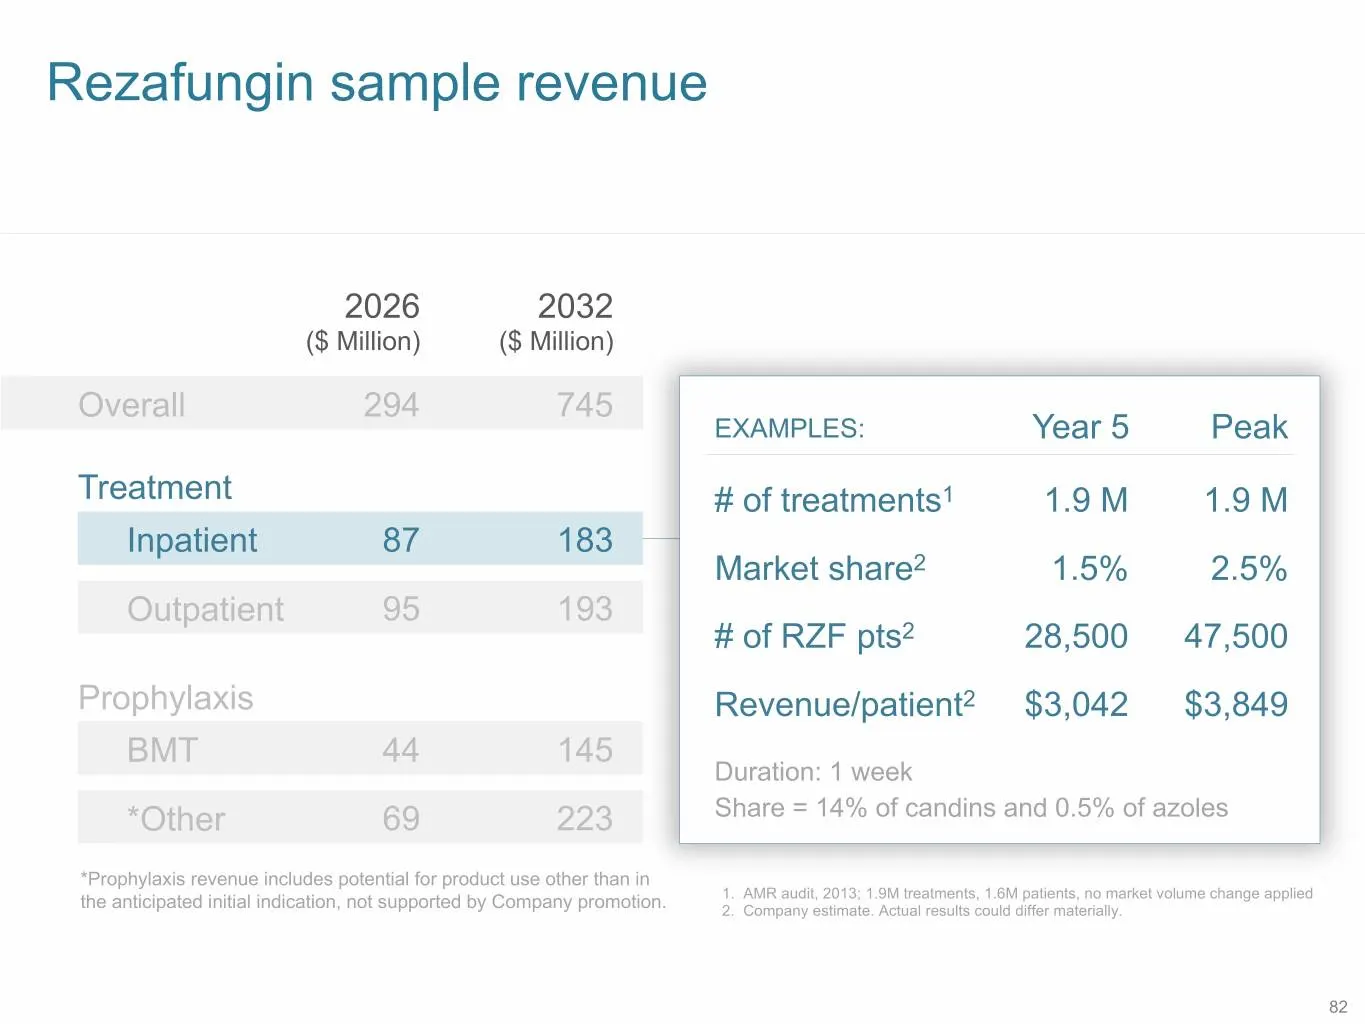
Slide 82: Rezafungin sample revenue
Rezafungin sample revenue 2026 2032 ($ Million) ($ Million) Overall 294 745 EXAMPLES: Year 5 Peak Treatment # of treatments1 1.9 M 1.9 M Inpatient 87 183 Market share2 1.5% 2.5% Outpatient 95 193 # of RZF pts2 28,500 47,500 Prophylaxis Revenue/patient2 $3,042 $3,849 BMT 44 145 Duration: 1 week *Othe
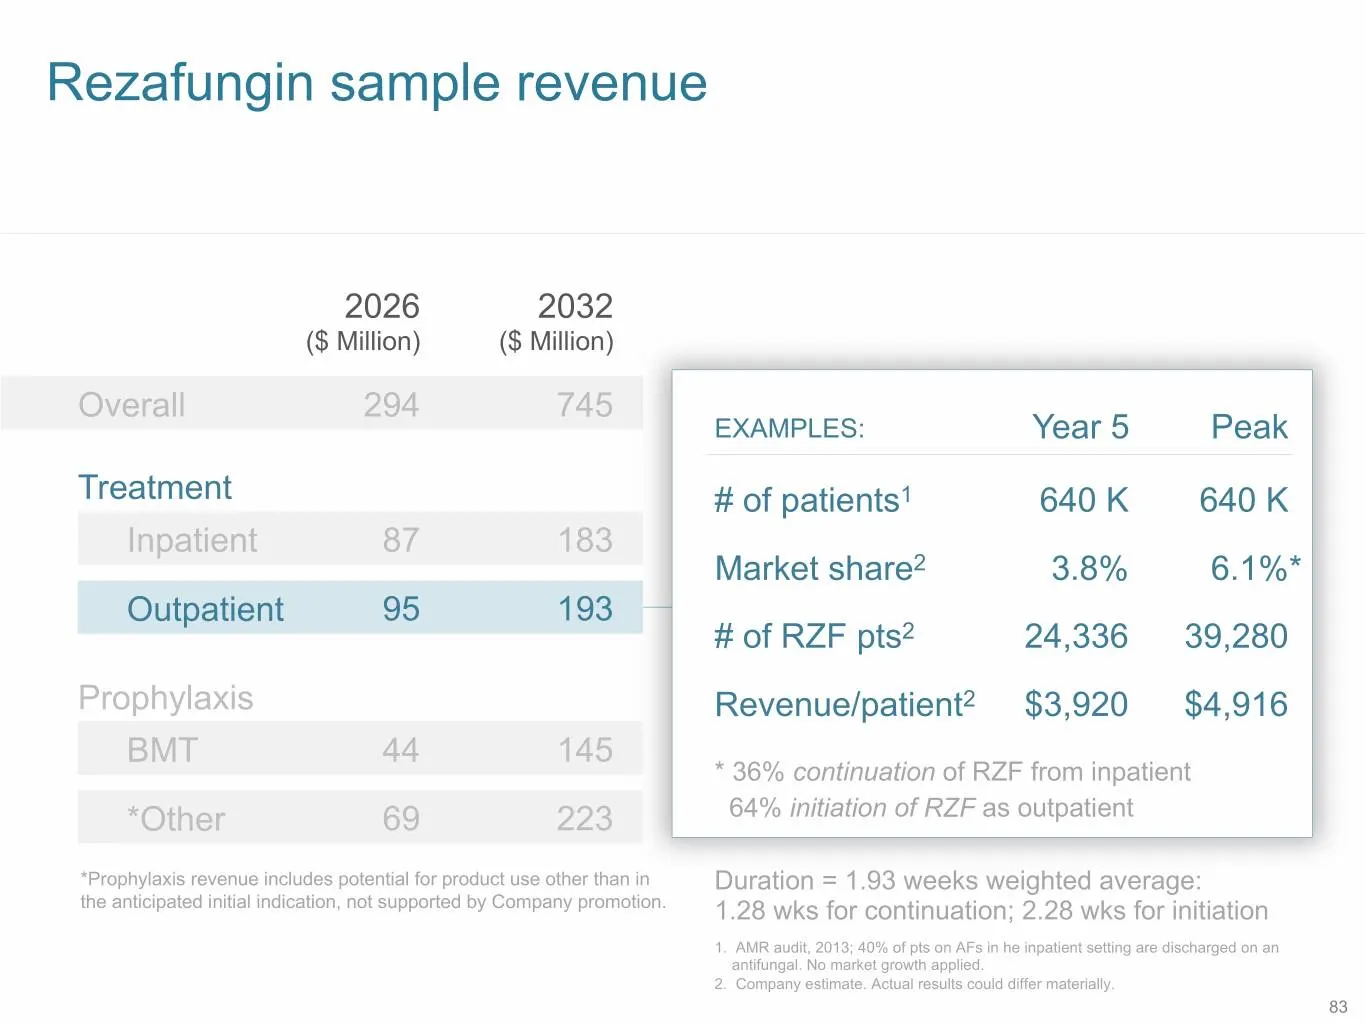
Slide 83: Rezafungin sample revenue
Rezafungin sample revenue 2026 2032 ($ Million) ($ Million) Overall 294 745 EXAMPLES: Year 5 Peak Treatment # of patients1 640 K 640 K Inpatient 87 183 Market share2 3.8% 6.1%* Outpatient 95 193 # of RZF pts2 24,336 39,280 Prophylaxis Revenue/patient2 $3,920 $4,916 BMT 44 145 * 36% continuation of R
Slide 84: Rezafungin sample revenue
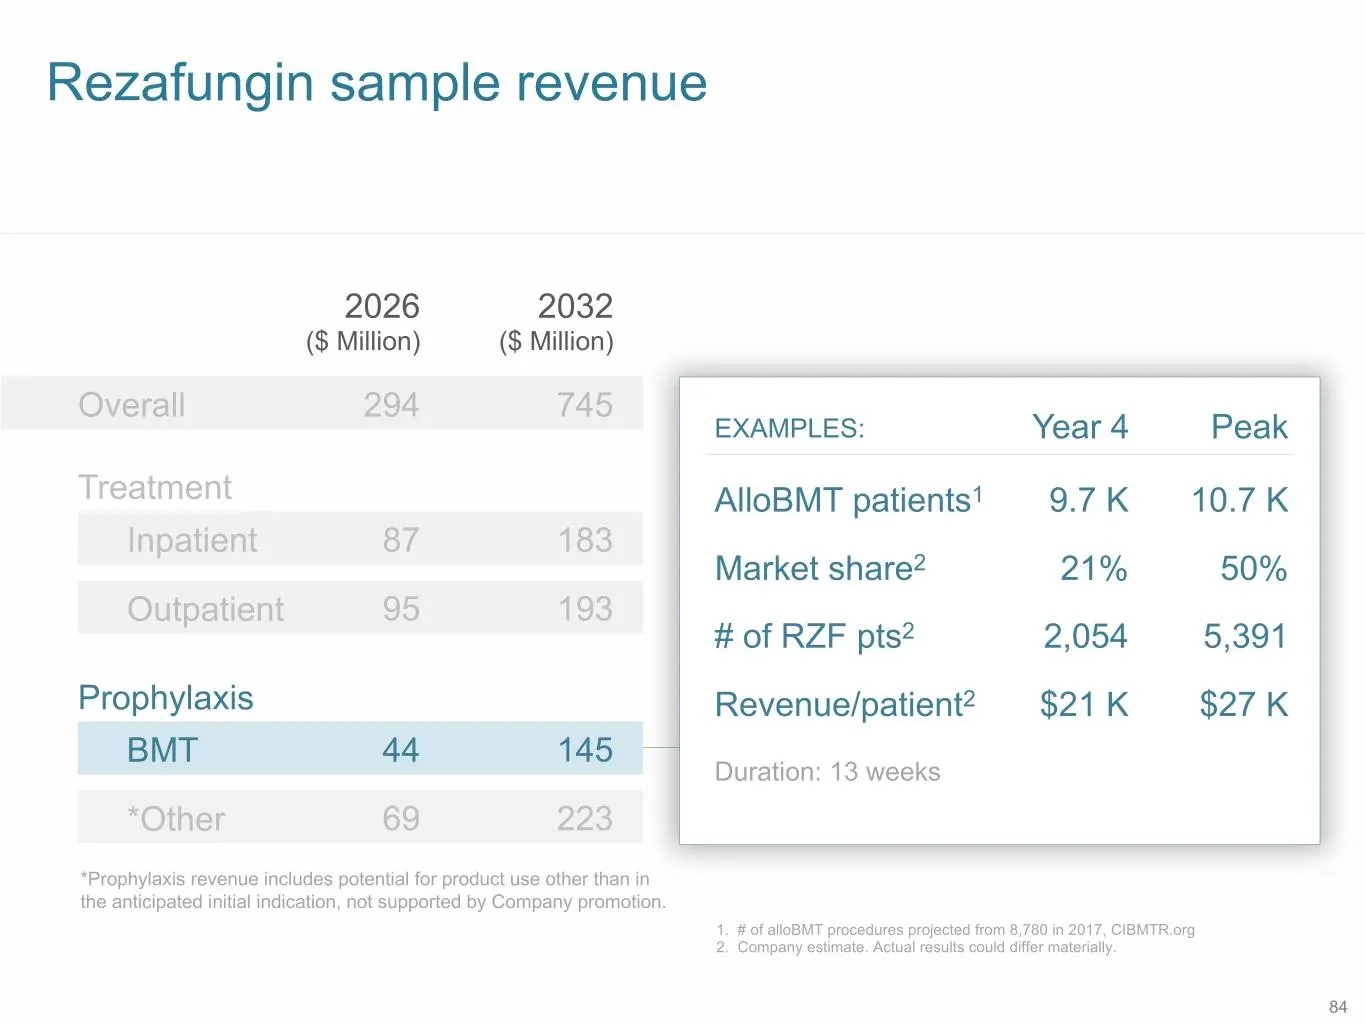
Rezafungin sample revenue 2026 2032 ($ Million) ($ Million) Overall 294 745 EXAMPLES: Year 4 Peak Treatment AlloBMT patients1 9.7 K 10.7 K Inpatient 87 183 Market share2 21% 50% Outpatient 95 193 # of RZF pts2 2,054 5,391 Prophylaxis Revenue/patient2 $21 K $27 K BMT 44 145 Duration: 13 weeks *Other
Slide 85: Rezafungin sample revenue
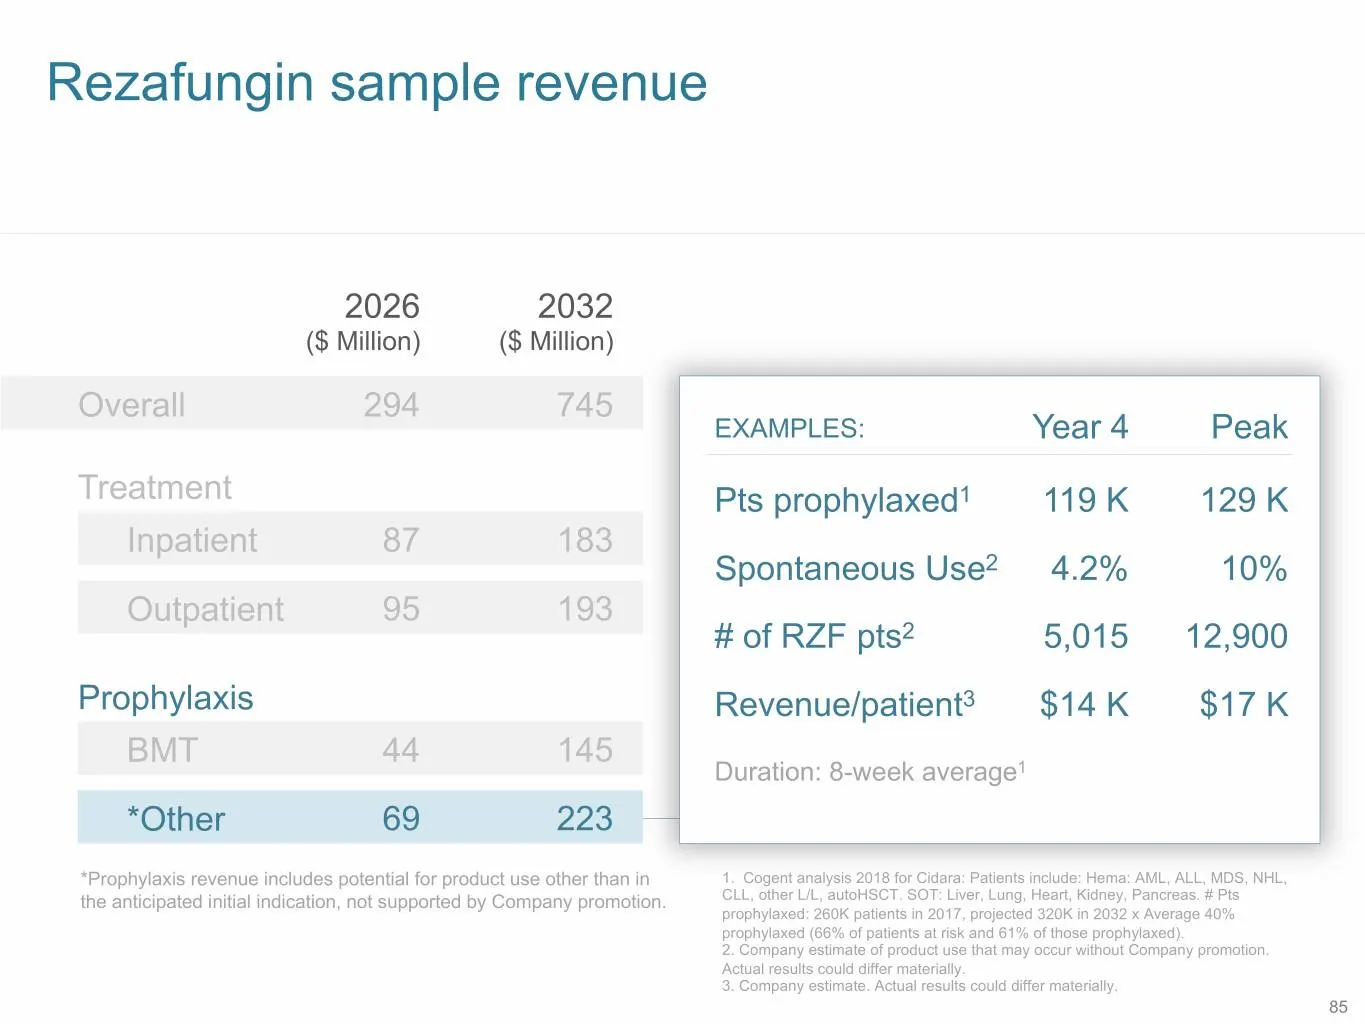
Rezafungin sample revenue 2026 2032 ($ Million) ($ Million) Overall 294 745 EXAMPLES: Year 4 Peak Treatment Pts prophylaxed1 119 K 129 K Inpatient 87 183 Spontaneous Use2 4.2% 10% Outpatient 95 193 # of RZF pts2 5,015 12,900 Prophylaxis Revenue/patient3 $14 K $17 K BMT 44 145 Duration: 8-week averag
Slide 86: ~$745M opportunity in US, in ID and hematology
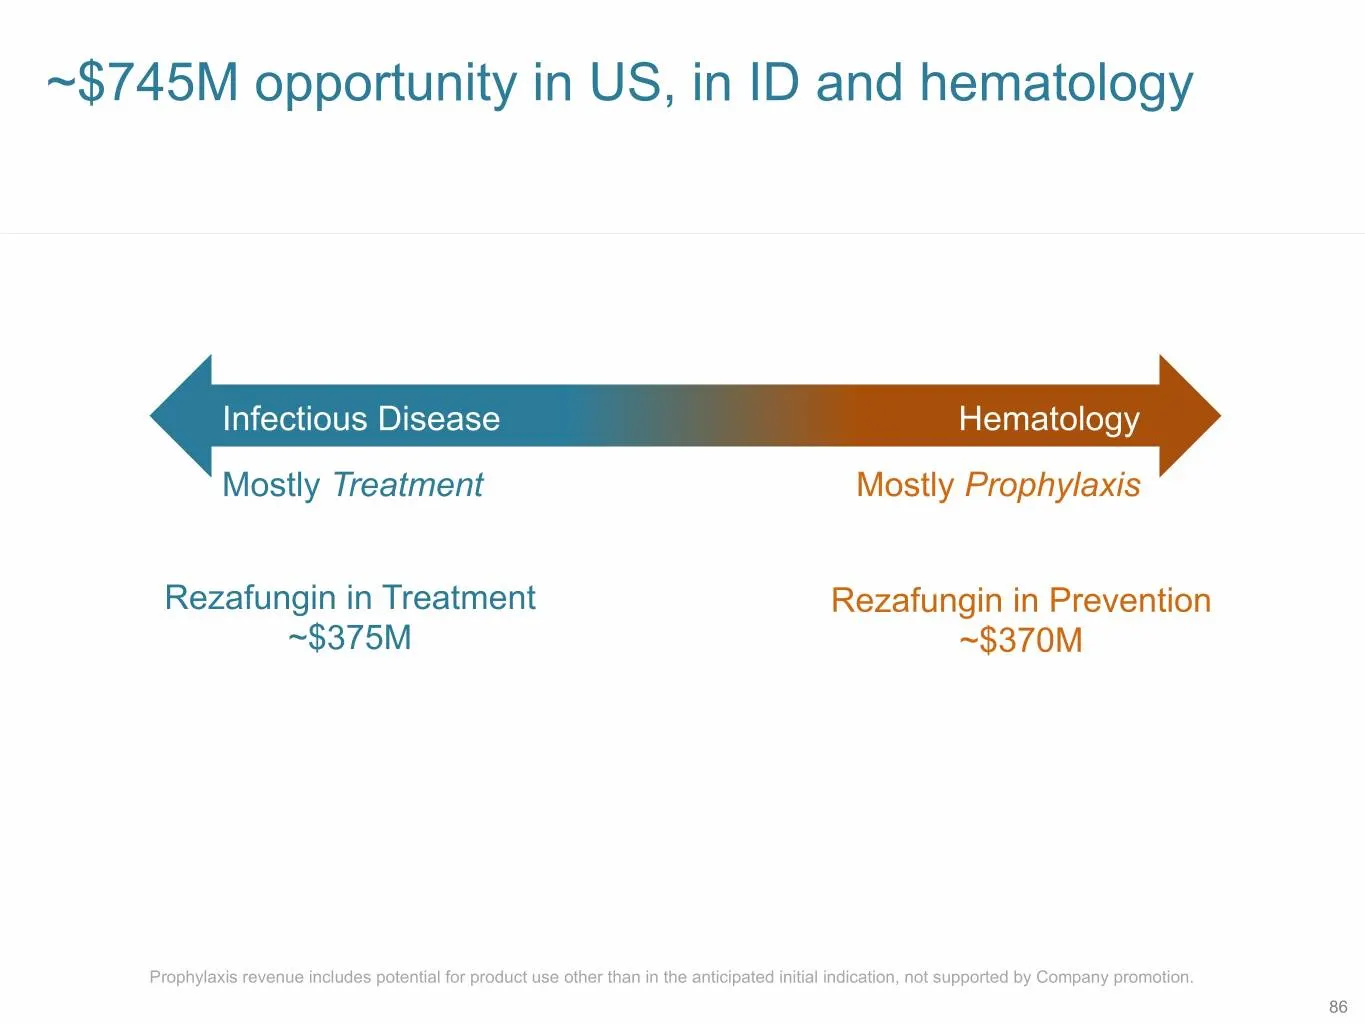
~$745M opportunity in US, in ID and hematology Infectious Disease Hematology Mostly Treatment Mostly Prophylaxis Rezafungin in Treatment Rezafungin in Prevention ~$375M ~$370M Prophylaxis revenue includes potential for product use other than in the anticipated initial indication, not supported by Co

Slide 87: Commercial Outlook: Rezafungin, Cloudbreak - Influenza
Commercial Outlook Rezafungin Cloudbreak - Influenza 87
Slide 88: Influenza: ~320M people should be vaccinated/year
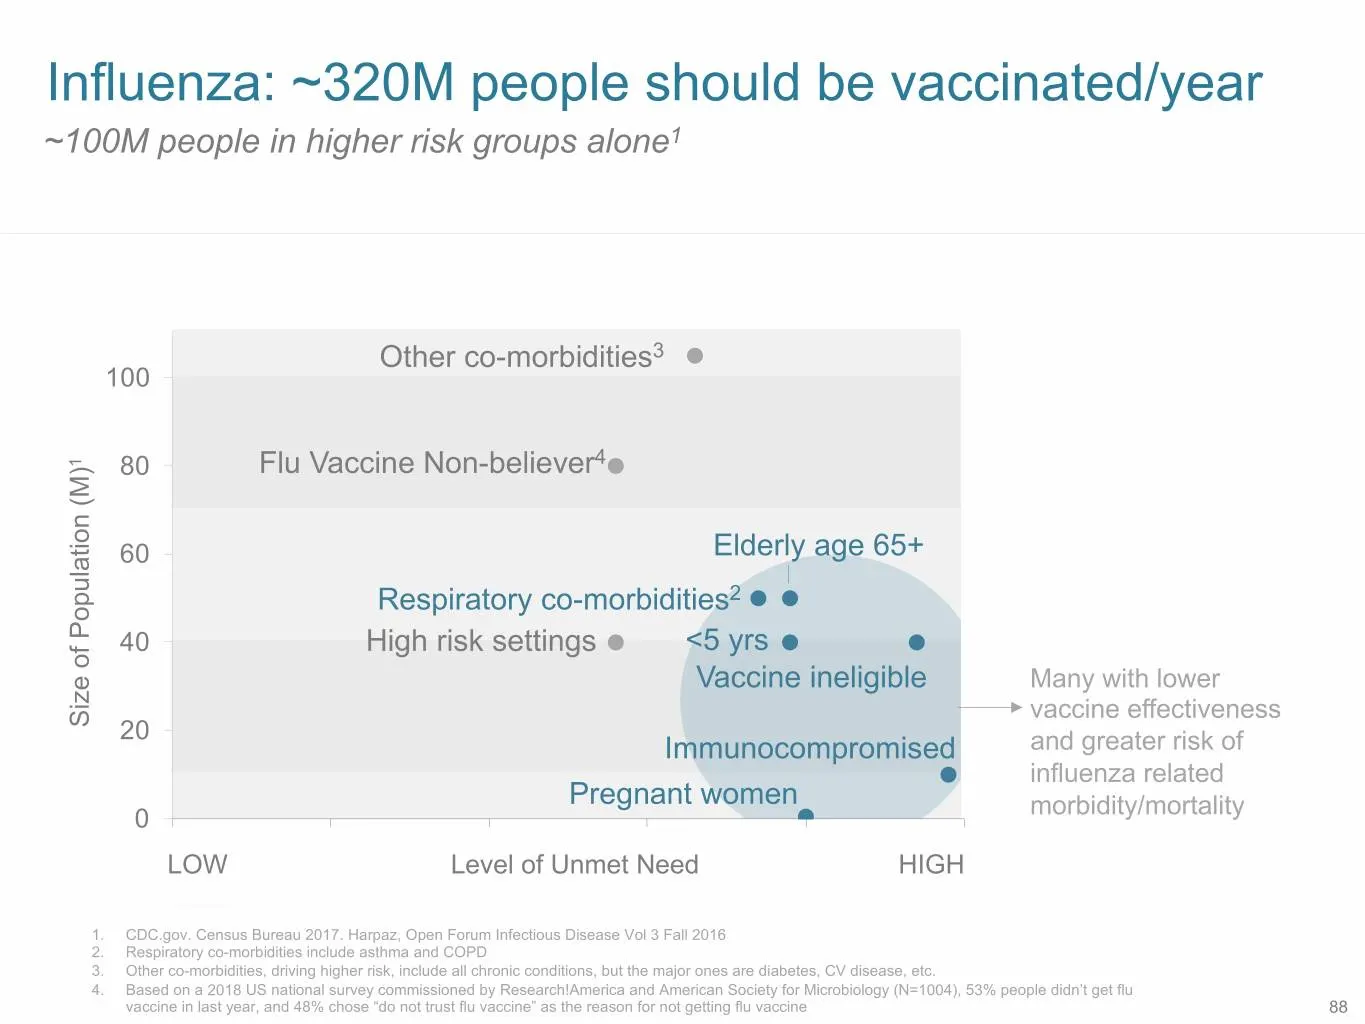
Influenza: ~320M people should be vaccinated/year ~100M people in higher risk groups alone1 Other co-morbidities3 100 1 80 Flu Vaccine Non-believer4 60 Elderly age 65+ Respiratory co-morbidities2 40 High risk settings <5 yrs Vaccine ineligible Many with lower vaccine effectiveness Size of Population
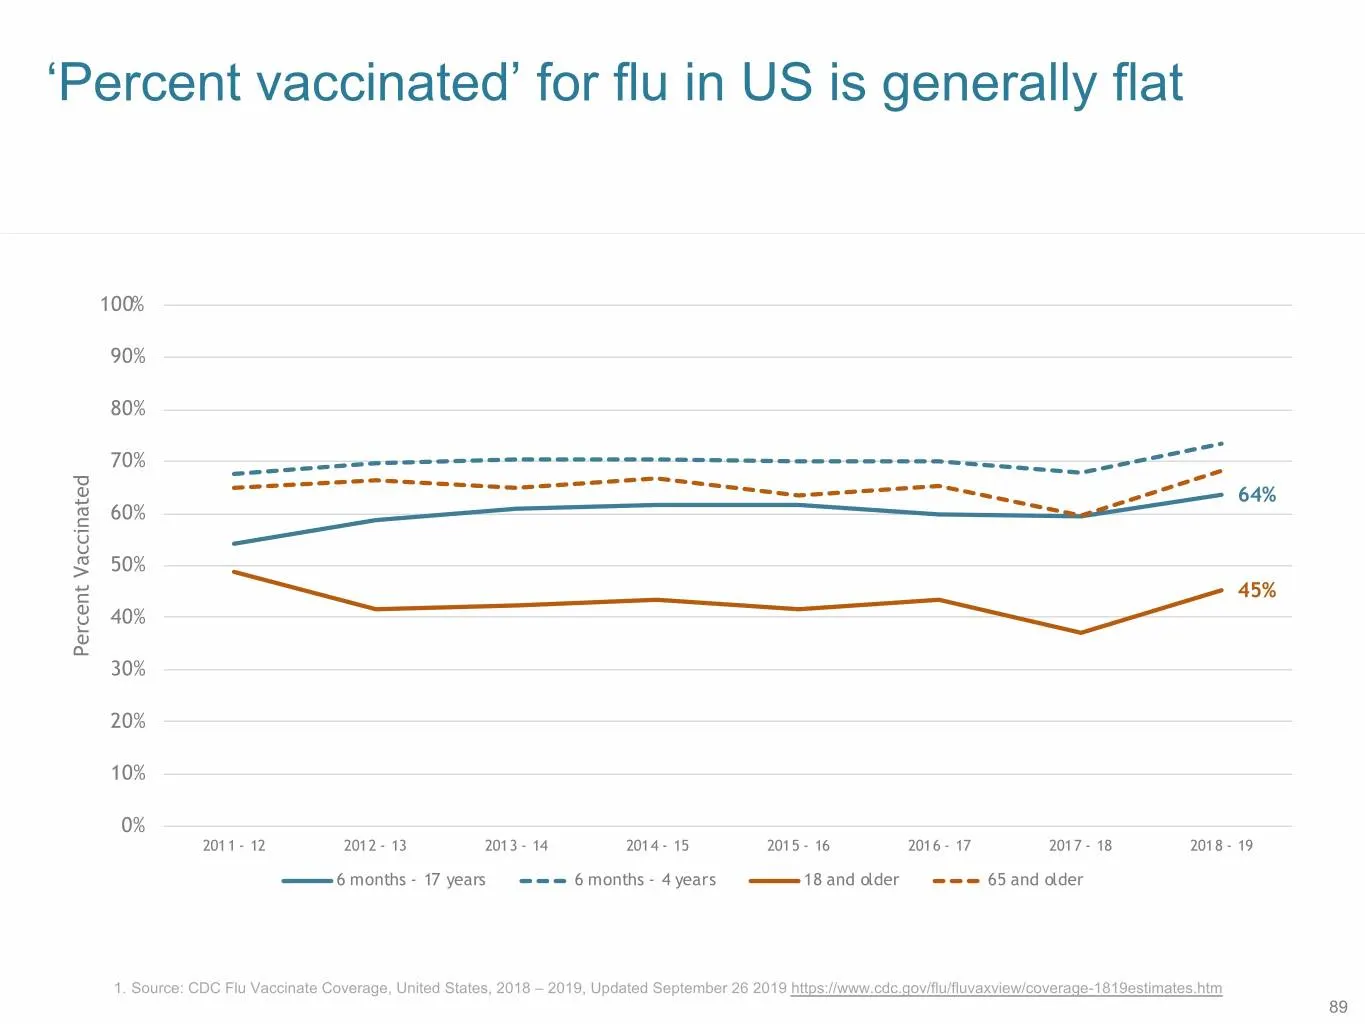
Slide 89: Percent vaccinated for flu in US is generally flat
‘Percent vaccinated’ for flu in US is generally flat 100% 90% 80% 70% 64% 60% 50% 45% 40% Percent Vaccinated 30% 20% 10% 0% 2011 - 12 2012 - 13 2013 - 14 2014 - 15 2015 - 16 2016 - 17 2017 - 18 2018 - 19 6 months - 17 years 6 months - 4 years 18 and older 65 and older 1. Source: CDC Flu Vaccinate Co
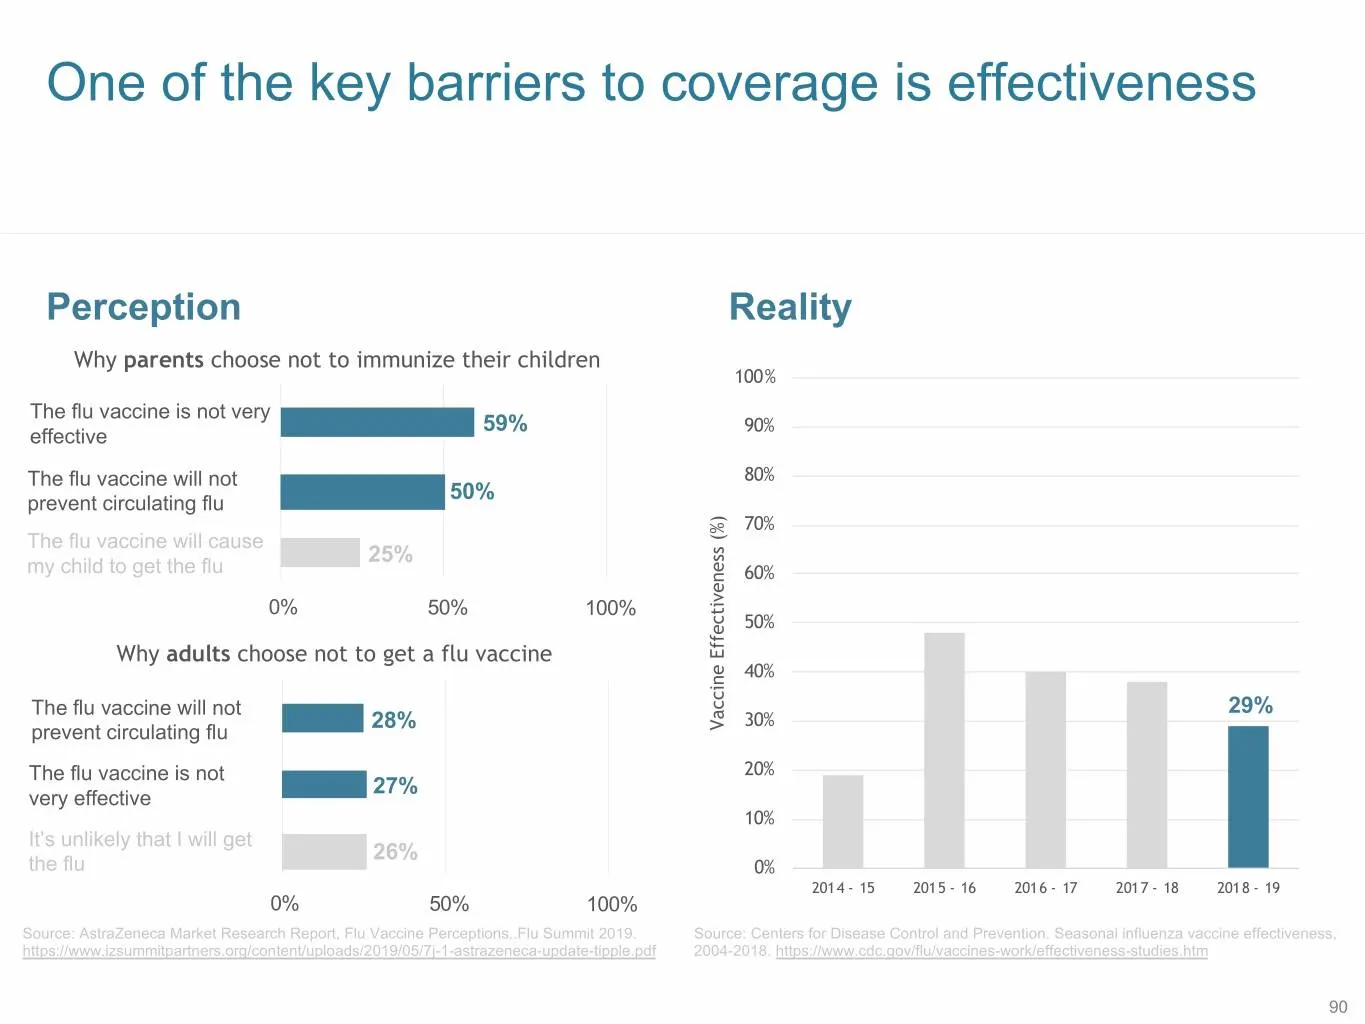
Slide 90: One of the key barriers to coverage is effectiveness
One of the key barriers to coverage is effectiveness Perception Reality Why parents choose not to immunize their children 100% The flu vaccine is not very 59% 90% effective The flu vaccine will not 80% 50% prevent circulating flu 70% The flu vaccine will cause 25% my child to get the flu 60% 0% 50%
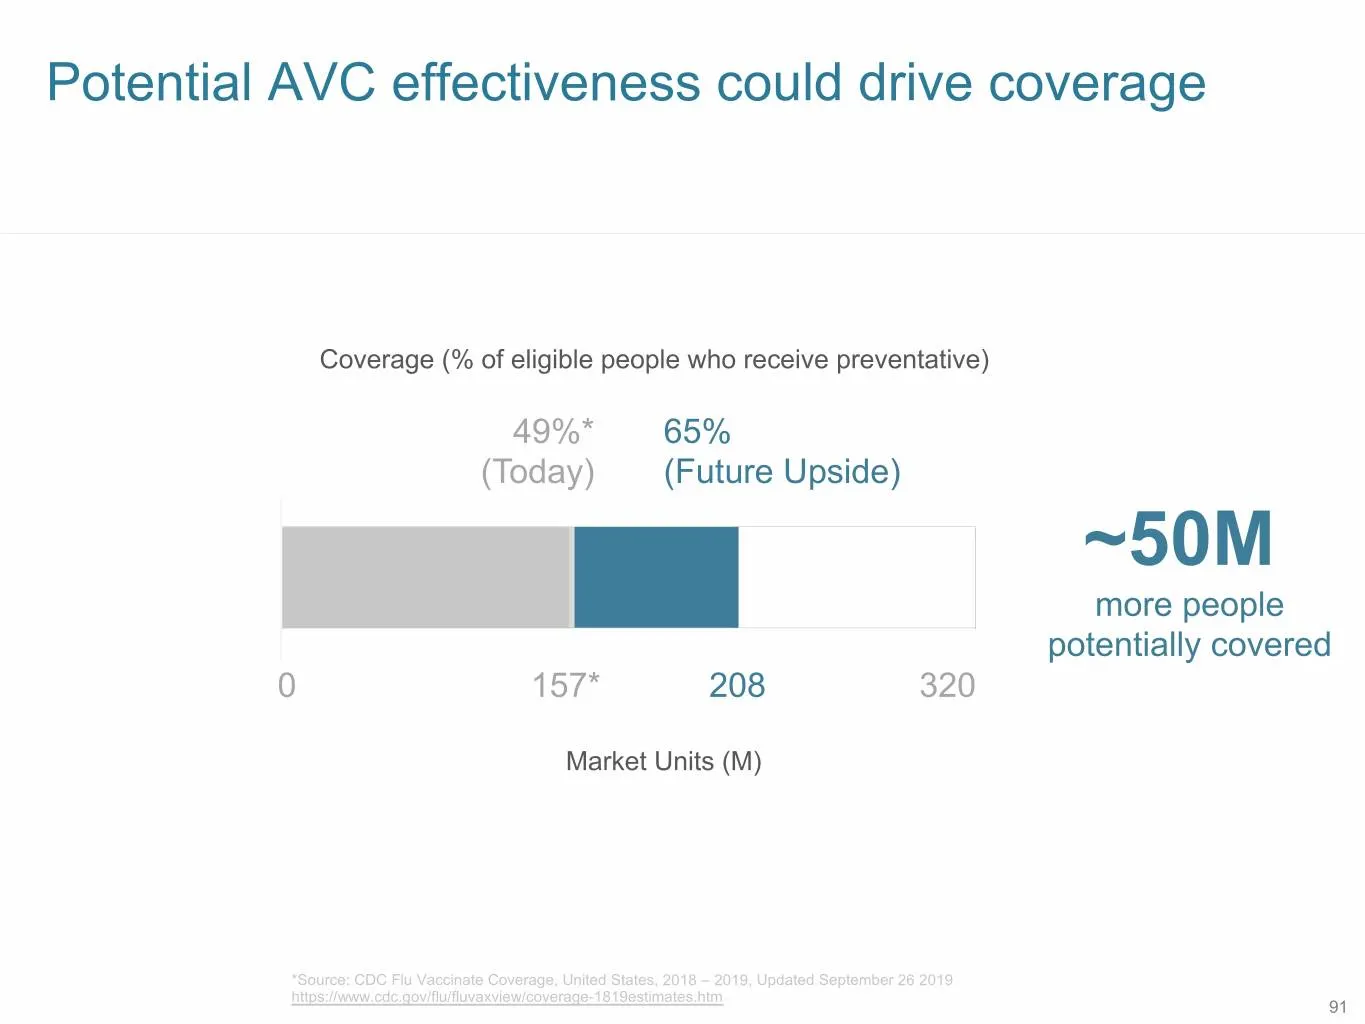
Slide 91: Potential AVC effectiveness could drive coverage
Potential AVC effectiveness could drive coverage Coverage (% of eligible people who receive preventative) 49%* 65% (Today) (Future Upside) ~50M more people potentially covered 0 157* 208 320 Market Units (M) *Source: CDC Flu Vaccinate Coverage, United States, 2018 – 2019, Updated September 26 2019 h
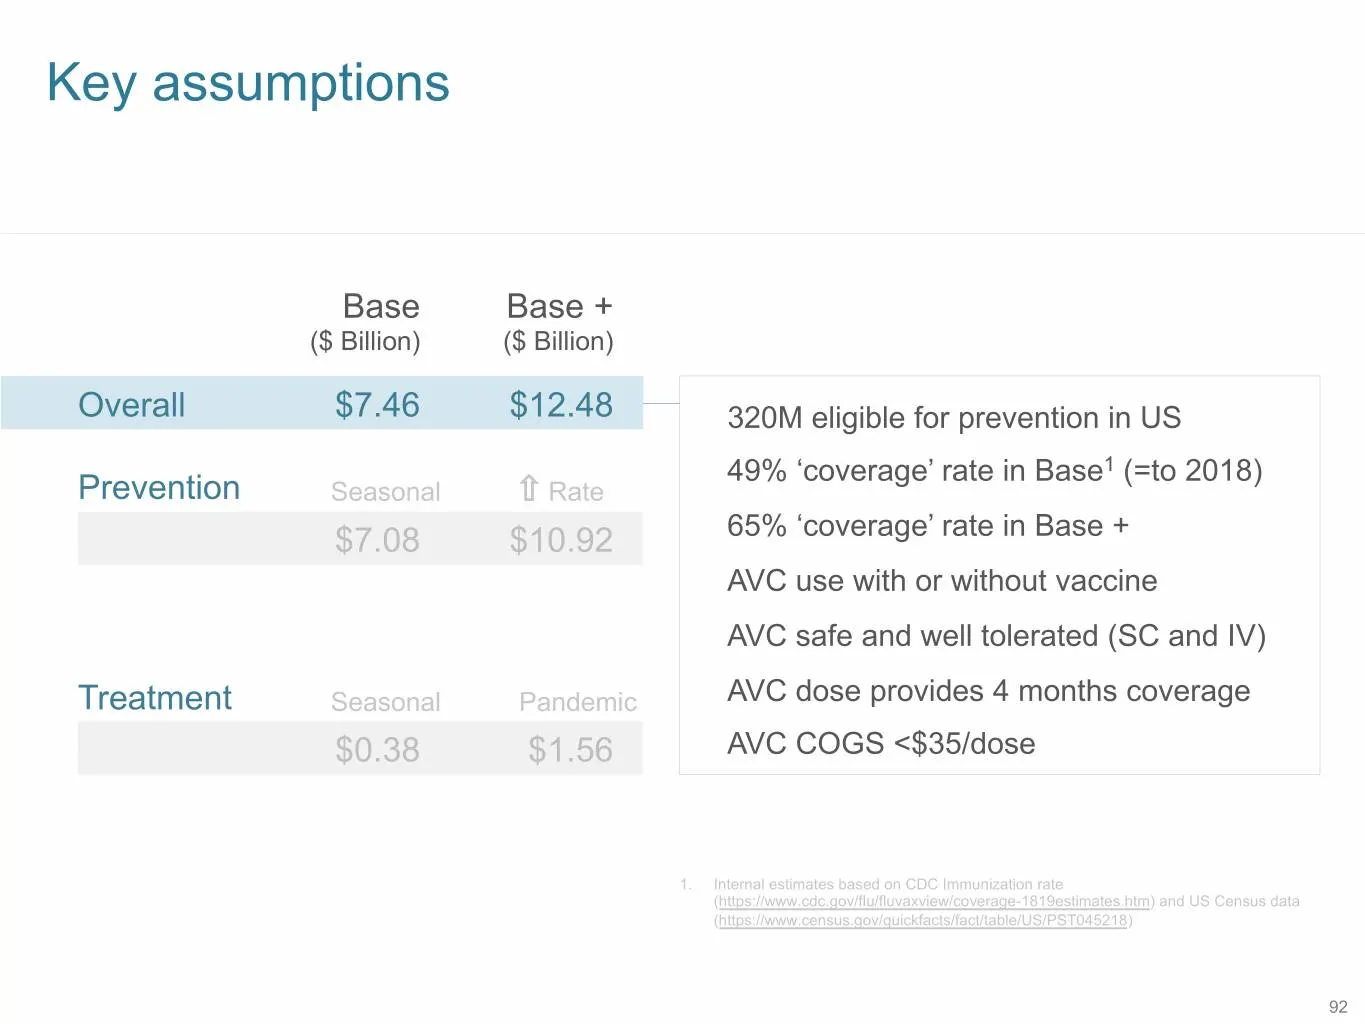
Slide 92: Key assumptions
Key assumptions Base Base + ($ Billion) ($ Billion) Overall $7.46 $12.48 320M eligible for prevention in US 49% ‘coverage’ rate in Base1 (=to 2018) Prevention Seasonal Rate $7.08 $10.92 65% ‘coverage’ rate in Base + AVC use with or without vaccine AVC safe and well tolerated (SC and IV) Treatment Se
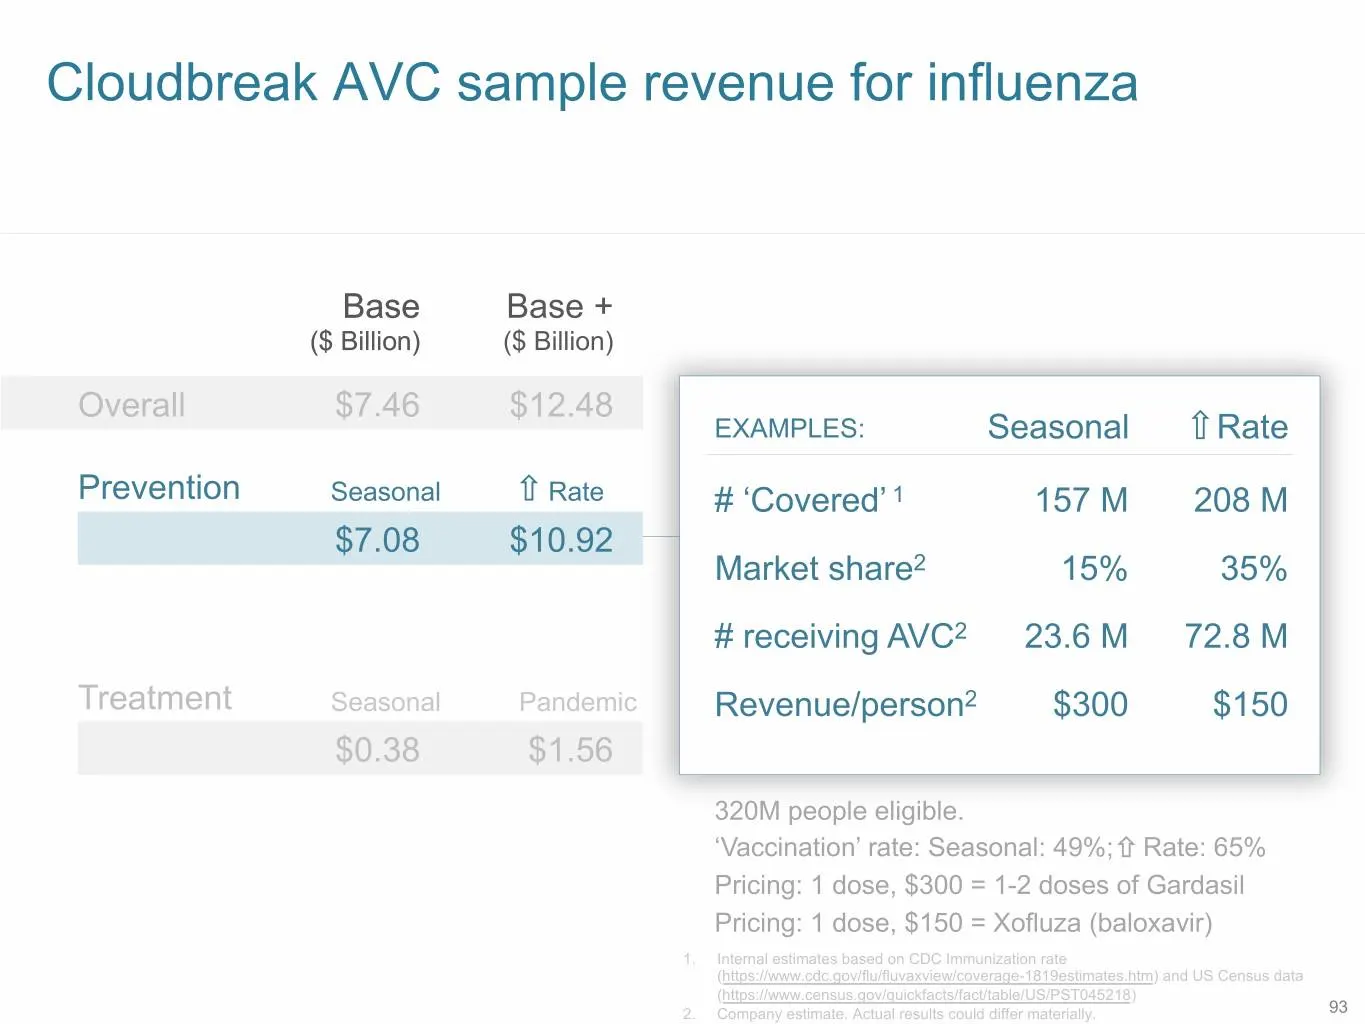
Slide 93: Cloudbreak AVC sample revenue for influenza
Cloudbreak AVC sample revenue for influenza Base Base + ($ Billion) ($ Billion) Overall $7.46 $12.48 EXAMPLES: Seasonal Rate Prevention Seasonal Rate # ‘Covered’ 1 157 M 208 M $7.08 $10.92 Market share2 15% 35% # receiving AVC2 23.6 M 72.8 M Treatment Seasonal Pandemic Revenue/person2 $300 $150 $0.3
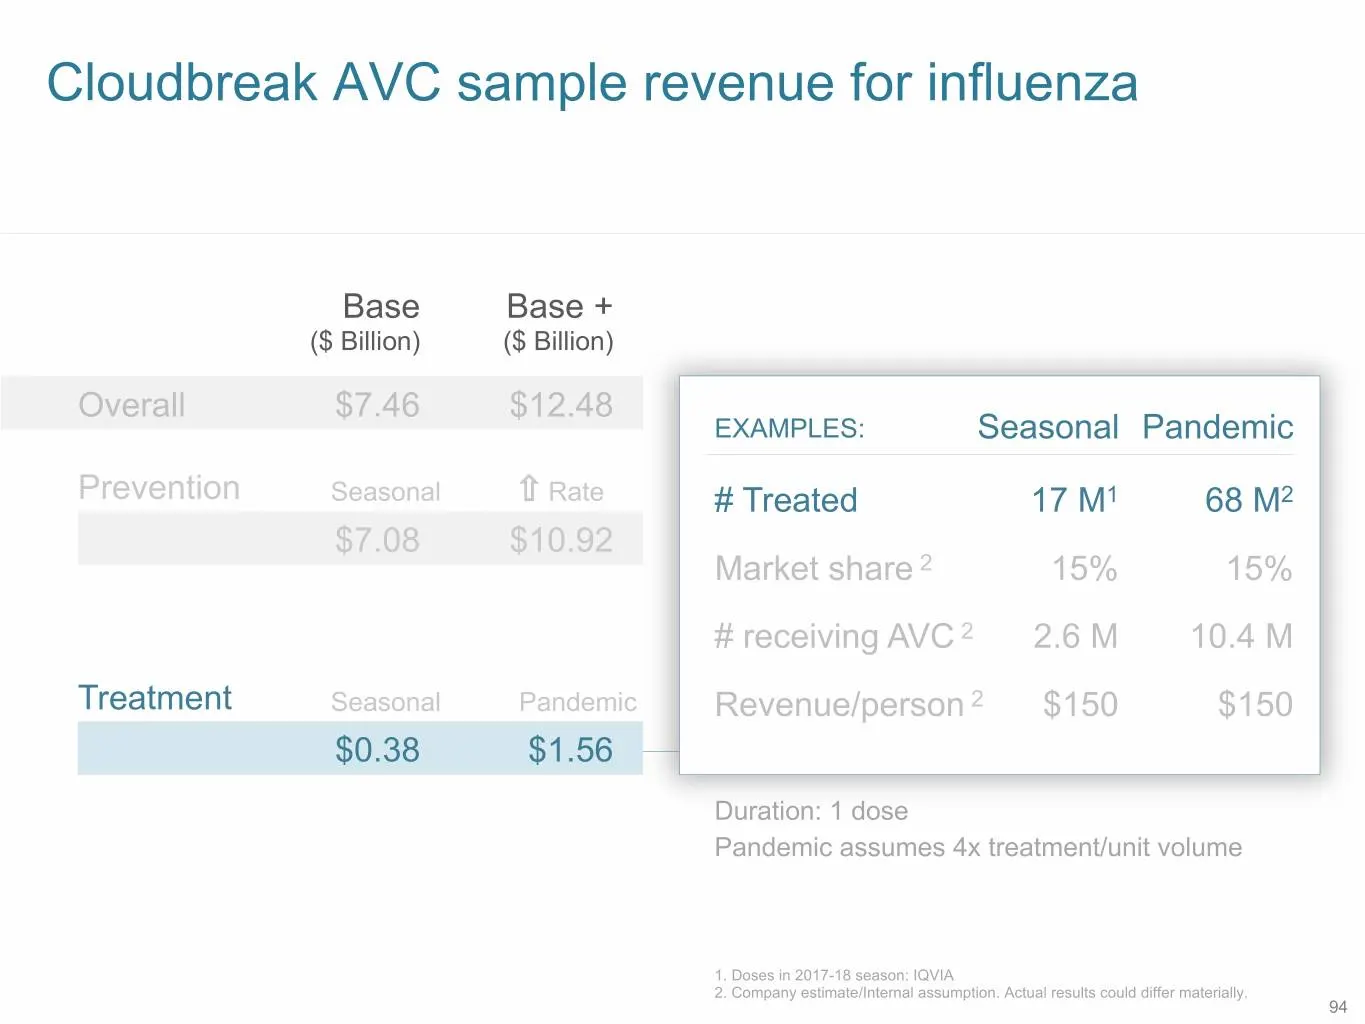
Slide 94: Cloudbreak AVC sample revenue for influenza
Cloudbreak AVC sample revenue for influenza Base Base + ($ Billion) ($ Billion) Overall $7.46 $12.48 EXAMPLES: Seasonal Pandemic Prevention Seasonal Rate # Treated 17 M1 68 M2 $7.08 $10.92 Market share 2 15% 15% # receiving AVC 2 2.6 M 10.4 M Treatment Seasonal Pandemic Revenue/person 2 $150 $150 $0

Slide 95: Agenda
SB 12 Agenda Opening - Overview Jeff Stein, PhD, CEO, Cidara Therapeutics Antifungal Treatment Unmet Neil Clancy, M.D., University of Pittsburgh Needs Unmet Antifungal Prophylaxis Needs Kieren Marr, M.D., Johns Hopkins School of Medicine Influenza Unmet Allison McGeer, M.D., University of Toronto Ne

Slide 96: New Hope for Serious Infections: Analyst – KOL Day
New Hope for Serious Infections Analyst – KOL Day November 14, 2019 © Cidara Therapeutics 2019
Source: SEC EDGAR · 8-K filed Nov 14, 2019
More decks from Cidara Therapeutics Inc
 Corporate Update (June 2025)12 slides · Jun 23, 2025
 Investor Presentation (May 2024)63 slides · May 3, 2024
 Investor Day (September 2023)58 slides · Sep 21, 2023
 Investor Day (July 2022)57 slides · Jul 7, 2022
 Technical Presentation (December 2021)24 slides · Dec 14, 2021
 Investor Day (September 2021)110 slides · Sep 21, 2021